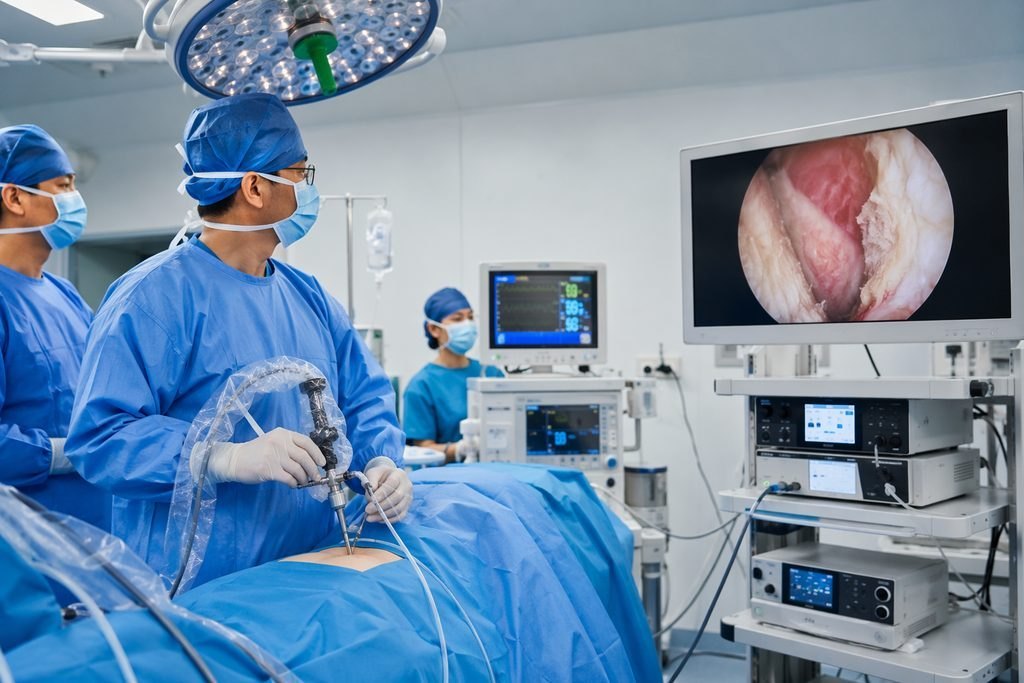
What an MDT Is Supposed to Decide for Benign Prostatic Enlargement
A multidisciplinary team discussion brings two or three relevant specialties together for a complex or cross-specialty case. For benign prostatic enlargement, that could mean urology alongside another specialty if your history involves more than the prostate alone. The purpose is not to replace your urologist. It is to pool the records, agree what the prostate problem actually is, and settle which treatment route the team can defend.
The discussion needs to answer a short list of practical questions. Which procedure is suitable given the size and shape of your prostate and your urinary symptoms? Does your previous prostate treatment change what is possible now? Are there competing conditions, such as heart, kidney or bleeding problems, that alter the risk balance? What still needs to be confirmed before anyone commits to a plan?
If those questions are not answered, the discussion has not done its job. A vague statement that surgery is possible is not a decision. You need to know which operation, why that one, what the alternatives are, and what the treating team still has to check.
Urinary Symptoms and Tests: The Records That Shape the Answer
The discussion cannot be useful without a clear picture of your urinary symptoms. How often do you urinate at night? Is the stream weak, is starting difficult, do you feel you cannot empty completely? How much does this affect sleep, work and travel? A symptom score recorded by your own clinician is more useful than a general description of discomfort.
Tests matter just as much. The team will want to see what has already been measured: prostate size and shape on imaging, flow and residual urine studies, blood tests including kidney function, urine testing, and any assessment of how well the bladder empties. If some of these are missing, the discussion should say which gaps limit the recommendation rather than guess.
This is where a records-based review earns its place. A remote review can organise what exists, flag what is missing and frame the questions for the hospital. It cannot examine you, and it does not establish final eligibility for any procedure. The treating hospital decides suitability after its own assessment.
Previous Prostate Treatment Changes the Options
If you have already had prostate treatment, that history belongs at the centre of the discussion, not in a footnote. Previous surgery, laser treatment or another intervention can change the anatomy, the amount and position of tissue that remains, and how a further procedure would be approached. The team needs the original operation notes and discharge summary, not just the name of the procedure. A patient who says "I had a laser done" gives the panel almost nothing to work with; the operative report tells them what was removed, what was left, and whether the bladder neck or urethra was altered.
Ask specifically how the earlier treatment changes the current recommendation. Does it rule out a particular approach, or simply make it more demanding and slower? Does it change what pathology from any removed tissue can show, or how reliable a future tissue sample would be? Does it affect the risk of narrowing or incontinence afterward? These are questions for the treating clinicians, and the answers depend on your individual records rather than on the name of the operation alone.
The same applies to medicines. Do not stop or change any prescribed medicine on your own. If the discussion touches on medication, the treating clinician decides what happens and when. Your job is to make sure the team knows exactly what you take, at what dose, and why, including anything bought without a prescription. A medication list that is incomplete or out of date is one of the easiest ways for a discussion to reach a conclusion that does not fit you.
There is a second reason this history matters. If a previous procedure did not relieve your symptoms, the panel has to explain why before recommending another one. Was the earlier operation incomplete, was the obstruction from a different cause, or is the bladder itself the problem? A recommendation that repeats the same logic without answering that question is not a decision, it is a guess. Ask the team to state, in writing, what the earlier treatment tells them about the next step.
Finally, keep the timeline factual. Note the date of each procedure, the hospital, the surgeon's name if you have it, and what you were told afterward. If you were told the operation "went well" but symptoms returned within months, say so plainly. That detail is exactly the kind of information a multidisciplinary discussion is meant to weigh, and it is far more useful than a general impression that things have not been right since.
HoLEP and Other Procedures: What the Discussion Should Compare
HoLEP is one option for benign prostatic enlargement. It removes obstructing prostate tissue through the urethra using a laser, and the removed tissue can be examined by pathology. That much is established. What is not established in advance is whether HoLEP is the right choice for you.
The discussion should compare the realistic options rather than present one. That means asking how each approach handles your prostate size and shape, what the expected recovery and catheter arrangements are for someone with your history, and what the alternatives are if the first choice is unsuitable. The team should also explain what it still needs to confirm before a final recommendation.
Be careful with promises. No discussion can guarantee symptom resolution, and none should tell you to stop medication or give you a fixed catheter-removal schedule before your own assessment. Those decisions belong to the treating clinicians who examine you and review your full record.
Why No Hospital Is Obliged to Provide an MDT Format
This is the part many patients miss. A multidisciplinary discussion is a service that may be arranged for a complex or cross-specialty case, with the scope and fee agreed first. It is not a standard entitlement, and no hospital is required to run your case through that format. Some will; some will handle it through a single senior urologist instead.
That means the honest answer to "will I get an MDT?" is: it depends on the hospital and on whether your case warrants it. Ask directly. Does this hospital offer a multidisciplinary review for benign prostatic enlargement? Which specialties would take part? Who leads it, and how is the conclusion communicated to you? If the hospital does not offer that format, ask what its equivalent is and who makes the final call.
A review involving two or three relevant specialties may be arranged through ChinaSpecialistCare for a complex or cross-specialty case, with the scope and fee agreed before anything proceeds. That is a coordination route, not a guarantee that a particular hospital will convene a panel. The hospital decides suitability and format.
What to Prepare and What to Ask Before You Commit
Prepare a short, factual summary: your main urinary symptoms, when they started, what makes them worse, all current medicines, and every previous prostate or urinary procedure with dates and hospital names. Add the actual test reports, not just a list of test names. If a report is in another language, ask whether a translation is needed and who should provide it.
Then write your questions down before any appointment or review. Which procedure are you recommending for me, and why? What are the alternatives? What does my previous treatment change? What still needs to be confirmed, and what happens if it cannot be? Who makes the final decision, and how will I be told? What does the written estimate include, and what remains undecided?
Keep the enquiry light at the start. A brief summary through the enquiry form, email or WhatsApp is enough to begin; you do not need to send a complete medical archive or payment details in the first message. An initial enquiry is free and does not commit you to buying a proxy consultation. If your symptoms are worsening, seek local medical care rather than waiting on an overseas enquiry.
The next step is to send that short summary and ask one clear question: for my case, what would a multidisciplinary discussion need to answer, and does this hospital provide that format? The treating hospital and its licensed clinicians decide suitability, the procedure and the plan.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.