What the clinician is trying to investigate
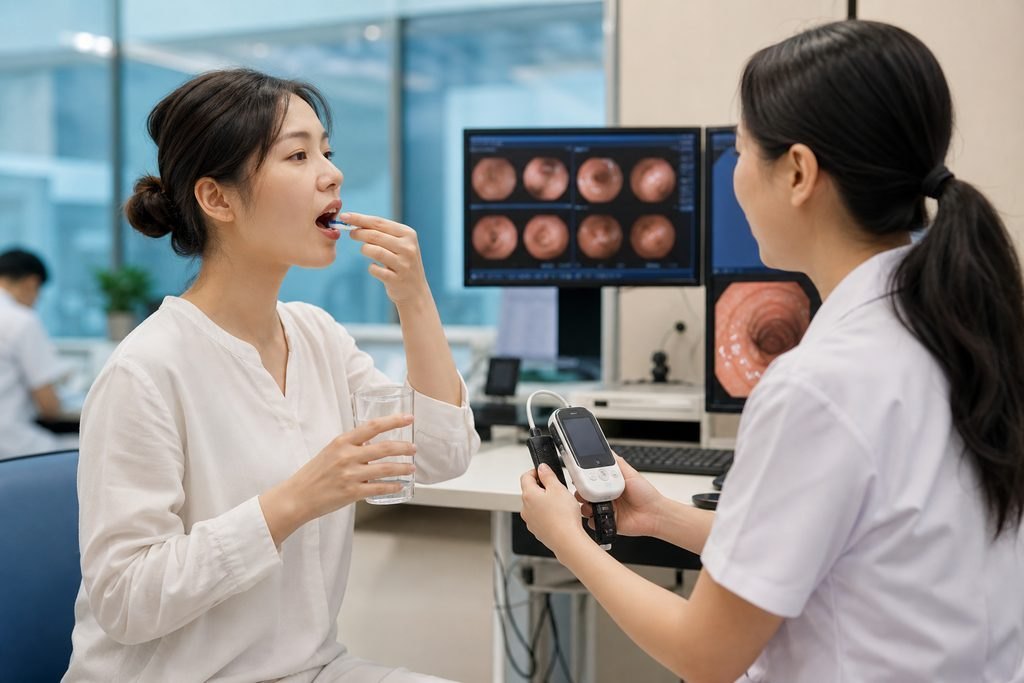
Small-bowel capsule endoscopy uses a swallowed camera to record images of the small bowel. It is not the same as upper endoscopy or colonoscopy, and it does not examine the whole digestive tract. The clinician considering this test is usually trying to answer a specific question about the small bowel after other investigations have not fully explained the symptoms or findings.
That is why your previous tests matter before suitability is discussed. The clinician needs to understand what has already been looked at, what was found, and what remains unclear. A capsule study may be proposed to look for a source of bleeding, to assess known or suspected small-bowel disease, or to follow up an abnormality seen on another study. The exact reason should come from the treating clinician, not from a general article.
When you contact a hospital in China, describe the main clinical question in one or two sentences. For example: persistent anaemia after normal upper and lower endoscopy, or suspected small-bowel Crohn's disease. This helps the team route your enquiry to the right specialist and ask for the records that are actually relevant.
Which previous tests to gather and why each one matters
The most useful preparation is a clear, organised record of what has already been done. Different tests answer different questions, and the clinician uses them together rather than in isolation.
Upper endoscopy and colonoscopy reports show whether the stomach, oesophagus, duodenum and colon have been directly examined. If these were normal, the clinician may be considering whether the small bowel is the next area to assess. If they showed something, that finding may change the plan.
Imaging such as CT or MR enterography can show the structure of the bowel and may raise or lower concern about narrowing. This is directly relevant because a narrowed segment can prevent the capsule from passing through. The clinician weighs this risk before recommending the test.
Video capsule studies done previously, if any, should be included with their reports and images where available. A prior capsule that was incomplete or retained is important information for the next decision.
Laboratory results, including blood counts and iron studies, help show the pattern and severity of any anaemia. Pathology reports from biopsies give tissue-level information that imaging and endoscopy cannot provide.
Do not send a complete archive in the first message. A short summary with the main reports is enough to start. The hospital can then tell you what else it needs.
Bowel narrowing and capsule-retention risk: what to ask
Capsule retention is a recognised risk of small-bowel capsule endoscopy. It means the capsule does not pass out of the body, usually because of a narrowing or other obstruction in the bowel. This is why the clinician asks about previous imaging, surgery, known Crohn's disease, radiation to the abdomen, or other conditions that could narrow the bowel.
The assessment of this risk is clinical. It depends on your history, your previous investigations and sometimes on additional tests the treating team may request. A foreign guideline or a general article cannot decide this for you. Ask the clinician directly: based on my records, do you consider me suitable for capsule endoscopy, and what would you do if the capsule does not pass?
You should also ask whether a patency capsule or other preparation is being considered. A patency capsule is a dissolvable test capsule used in some settings to check whether the bowel is open enough. Whether it is appropriate, available and included in your plan is a question for the treating hospital.
If you have had abdominal surgery, known strictures, or a previous capsule that was retained, say so clearly in your first message. This is not a detail to leave out.
Preparation questions before the test
Preparation is one of the areas where a general article is least useful, because the instructions that matter are the ones written for you by the team doing the test. Ask the hospital for its own written preparation sheet rather than following a protocol you found online. The questions worth asking are concrete: what should I eat in the days before, is a laxative preparation required, when do I stop eating and drinking, and does anything about my regular medicines need to change around the test day.
Ask how the capsule is swallowed and what you are expected to do while it is recording. You may wear a recorder, and you may need to return it at a set time, but the practical arrangements differ between units. Ask how long the recording period lasts, whether you can move around normally, what you should avoid while the recorder is on, and when you are allowed to eat and drink again. If you are staying in a hotel, ask whether you need to remain near the hospital during the recording period.
If you take regular medicines, ask whether any of them need to be adjusted around the test, and get that answer in writing. Do not stop or change a prescribed medicine on your own, and do not treat a general article as permission to do so. The treating clinician or pharmacist should confirm what applies to you.
Ask what happens if the capsule has not passed within the time the team expects. A good answer explains how they will check, what symptoms should prompt you to contact them, and what follow-up is arranged. This is part of the safety discussion around the test, not an administrative afterthought, and it is reasonable to ask it before you agree to the procedure.
If you are travelling from abroad, also ask how the preparation fits around your arrival date. A preparation schedule that starts before you land, or a recording day that clashes with your return flight, changes the practical plan. The hospital can tell you what window it needs; you should not assume one trip is enough until the team confirms the dates.
How results are reviewed and what follow-up may involve
The capsule records images that a clinician reviews. The review is not instant, and the time to a result depends on the hospital, the workload and the complexity of the findings. Ask the team when and how you will receive the report, and whether a follow-up appointment is included.
If the capsule shows a treatable finding, the next step may be another procedure, medication review or further imaging. If it is normal, the clinician will interpret that in the context of your original question. A normal capsule does not always mean no further assessment is needed.
Ask who will explain the results to you, in what language, and whether you can receive a written report you can share with your doctor at home. If you are travelling from abroad, ask whether the follow-up can be done remotely or whether you need to stay in China for the result discussion.
Do not assume that a capsule study will be the final answer. It is one part of a diagnostic pathway, and the treating clinician decides how it fits with the rest of your care.
Practical next steps for an overseas patient
Start with a short summary of your situation and your main question. Include the key previous test reports: endoscopy, imaging, pathology and relevant blood results. You do not need to send everything at once, and you should not send passport numbers or payment details in an initial enquiry.
Ask the hospital or coordination team these specific questions: Which records do you need to assess suitability? Who will review my previous tests? What is the plan if the capsule does not pass? How and when will I receive the result? What preparation and follow-up appointments are required?
An initial enquiry is free and does not commit you to a proxy consultation or any treatment. The hospital decides whether capsule endoscopy is suitable for you. If you have worsening symptoms, severe pain, vomiting or signs of bowel obstruction, seek local urgent care rather than waiting for an overseas enquiry.
For general information about the procedure, see the capsule endoscopy reference page. When you are ready, send a brief summary through the enquiry form and the team can explain the next practical step.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.