Why a treatment name alone tells the surgeon very little
A list such as antibiotics, nasal steroid spray, a course of oral steroids or a previous sinus operation names what was tried but not what happened. Two patients can carry the same list and have completely different sinus disease. One may have improved for months and then relapsed; another may never have responded at all. The surgeon reviewing your records needs the second half of the story: the result.
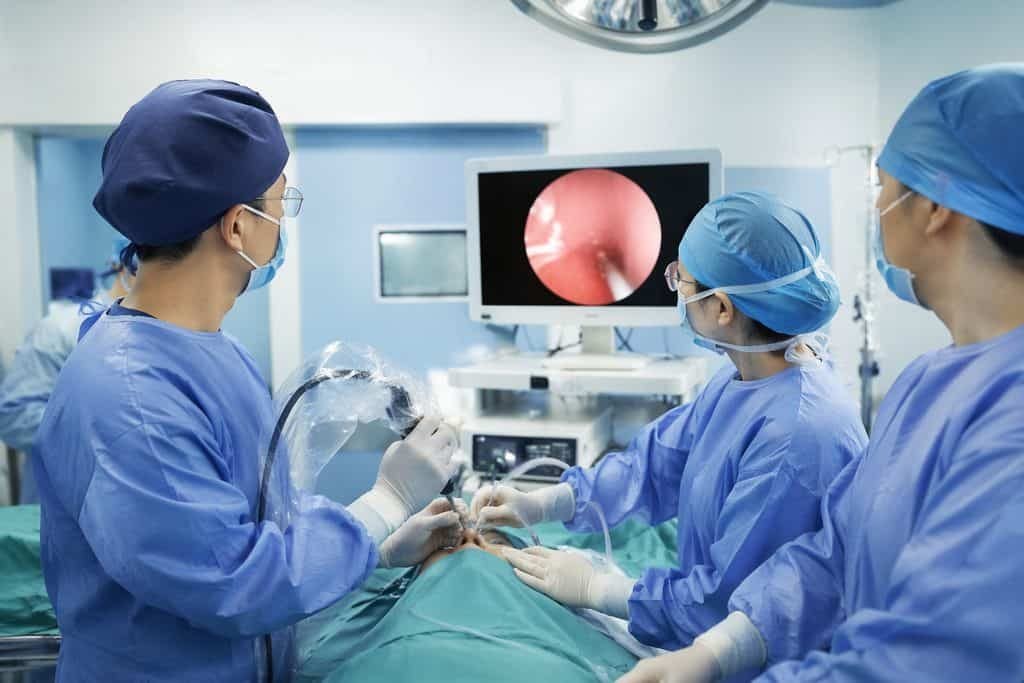
This matters because endoscopic sinus surgery treats sinus problems through the nose, and the proposed extent, alternatives and individual risks require discussion with the surgeon. The extent of surgery is a judgement about your specific anatomy, your symptom pattern and how your disease has behaved under treatment. A bare procedure name gives the surgeon almost nothing to reason with. An outcome description gives context.
So the practical rule is simple: for every previous treatment, write one or two sentences about the result. If you cannot remember, say so and note where the record might be found. A gap that is acknowledged is more useful than a confident but vague summary.
The five details that turn a name into a useful result
For each treatment, aim to capture five things. First, what the treatment was, including the exact medicine name, dose and how long it was taken, or the exact procedure performed. Second, the symptoms before treatment: blocked nose, facial pressure, loss of smell, discharge, headache, sleep disruption, or whatever applied to you. Third, the change after treatment, described in your own words rather than a score you cannot verify. Fourth, how long any improvement lasted before symptoms returned. Fifth, what the treating clinician said at the end of that course, including whether they considered it a success, a partial response or a failure.
The fifth point is often the one patients omit, and it is frequently the most informative. A clinician's conclusion reflects examination findings you may not have seen. If the conclusion was never clearly explained to you, write that down as a question rather than guessing.
Where you have documents, attach them. Where you do not, a short written summary in plain English is still useful. Do not translate medical terms yourself if you are unsure; give the original term and let the reviewing team interpret it.
Imaging and examination findings belong with the treatment history
Previous treatment results are easier to interpret alongside the imaging and examination that accompanied them. If you had a CT scan of the sinuses, note when it was done, what it was reported to show, and whether it was before or after any surgery. If you had nasal endoscopy, note what the clinician described seeing. If you had allergy testing or other investigations, include those results too.
The reason to keep these together is that a treatment result means little without the findings it was meant to change. A course of treatment that appeared to fail may look different when the surgeon can see the scan taken at the same time. Conversely, an apparent success may need re-examination if the imaging showed persistent disease.
Do not attempt to interpret the images yourself, and do not ask a non-clinician to do so. Your job is to supply the original reports and the dates. The treating surgeon decides what the images mean for the proposed operation.
What to ask the surgeon about the proposed procedure
Once the history is clear, the conversation can move to the decision itself. Ask what operation is being proposed and why that extent rather than a smaller or larger one. Ask what the alternatives are, including continued medical treatment, and what happens if you choose to wait. Ask what the individual risks are for you, given your anatomy and previous surgery, rather than general risks that apply to everyone.
If you have had previous sinus surgery, ask specifically how the earlier operation affects the plan. Scarring, altered anatomy and the completeness of the previous surgery can all change what is feasible. The surgeon should be able to explain this in terms you can follow.
Ask also what the expected course after surgery looks like in terms of clinic follow-up, and what would prompt you to seek care earlier. You do not need a fixed number of visits in advance; you need to understand what monitoring is planned and who provides it.
Planning the postoperative follow-up before you leave home
For an overseas patient, the practical question is not only what happens in the operating theatre but what happens afterwards. Ask the treating team how postoperative clinic care is arranged, how long they would want you to remain in China for review, and what instructions you would take home. Ask what the local clinician in your own country would need to know to continue your care.
Ask how you would contact the team if a problem arose after you returned home, and what records they would send with you. Ask whether any reviews are needed before you travel back, and what those reviews involve. These are questions to confirm with the named provider, because arrangements differ between hospitals and depend on your individual recovery.
It is reasonable to ask for the plan in writing. A written summary of the proposed procedure, the follow-up schedule and the warning signs to watch for is easier to share with your local doctor than a verbal explanation.
Sending a useful summary and the next step
When you make an initial enquiry, you do not need to send a complete medical archive. A short summary is enough to start: your main symptom, the treatments you have tried with their results, the key dates, and your central question. The team can then tell you what additional records would help and how to share them securely.
Write that summary as a short table or a set of numbered entries, one block per treatment, in the order the treatments happened. Keep each block to the five details described earlier: what was used, the symptoms beforehand, the change afterwards, how long any benefit lasted, and the treating clinician's conclusion. Add the date of any scan or endoscopy report that belongs with that treatment, and note whether the document is attached or still being requested.
A worked example of the level of detail that helps, using a fictional patient, shows the difference between a name and a result. Instead of writing only 'nasal steroid spray, six weeks', the entry reads: 'Nasal steroid spray, one spray each nostril twice daily for six weeks, started March. Before: blocked nose most days, facial pressure in the mornings, reduced smell. After: blockage improved for about three weeks, then returned to the previous level; smell unchanged. Clinician's conclusion: partial response, advised continuing and reviewing.' That entry tells a surgeon what the medicine achieved, how durable the benefit was and what the treating clinician thought, which a bare name cannot.
Keep the language plain and avoid scoring systems you cannot verify. If you were given a symptom questionnaire, attach the actual scores and dates rather than summarising them from memory. If you were not, describe the change in ordinary words: better, unchanged, worse, or improved then relapsed.
Label each entry clearly and put the most recent treatment first if the reviewing team asks for that order; otherwise chronological order is easiest to follow. Note any treatment you stopped early, and why, because an incomplete course has a different meaning from a completed one that failed.
Once the summary is ready, send it through the enquiry form, email or WhatsApp and ask two things: which additional documents would help the surgeon, and how the hospital prefers records to be shared. Do not send passport numbers, card details or a complete archive at this stage.
An initial enquiry is free and does not commit you to anything. A proxy consultation is optional and is not a prerequisite for every appointment or operation. The hospital decides whether endoscopic sinus surgery is suitable for you, and the surgeon confirms the proposed extent, alternatives and risks after reviewing your records.
If you have worsening symptoms, seek local medical care rather than waiting for an overseas review. Once your situation is stable, you can prepare the treatment-outcome summary described above and ask the relevant team what they need next.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.