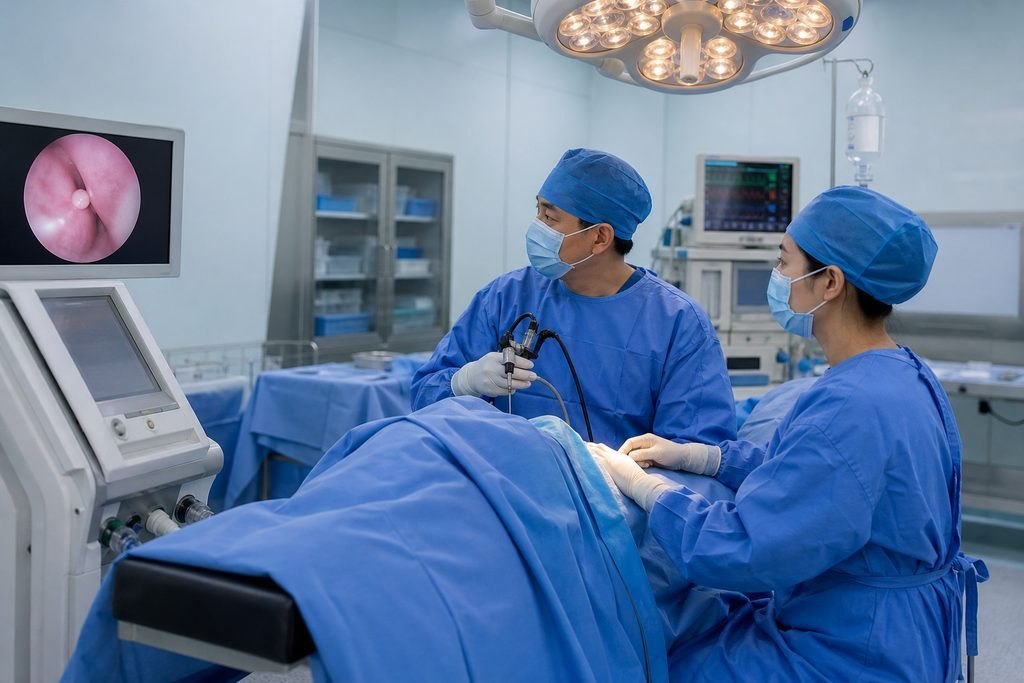
Why a HoLEP estimate is a scope document, not a final bill
HoLEP removes obstructing prostate tissue through the urethra using a laser, and the removed tissue can be examined by pathology. That description matters for cost planning because the procedure combines a surgical step, a pathology step, and a recovery period. A written estimate is a forecast built on assumptions about your health, the hospital's routine, and the expected course of treatment. When those assumptions change, the bill can change with them.
The practical question is not whether the estimate is accurate. It is whether the estimate tells you which assumptions it relies on. A useful estimate names the procedure, the ward type, the expected length of stay, the medicines included, and the tests bundled into the package. It also states what is not included. If the document only gives one total figure, you cannot tell which parts are fixed and which are open.
Ask the hospital's international office or billing department for the written estimate before you travel. Then ask them to mark each line as included, excluded, or to be confirmed. That single step turns a number into a decision you can actually review.
Items that frequently sit outside a surgical estimate
Different hospitals structure their estimates differently, so no single list applies everywhere. What follows are categories you should ask about directly, not assumptions about how any particular hospital bills.
Length of stay beyond the planned discharge date is one common gap. If your recovery is slower than expected, or if you need ongoing bladder irrigation or monitoring, the extra days may fall outside the original figure. Ask what the estimate assumes about your stay and how additional days are handled.
Medicines are another area to clarify. Some estimates include routine surgical and post-operative medicines; others list them separately. Ask which medicines are inside the estimate, which are outside, and how medicines you already take are treated.
Complications or unplanned interventions can change the scope. A return to theatre, a blood transfusion, or treatment for an infection may not be covered by the original estimate. Ask how the hospital handles these events and who discusses the cost implications with you.
Pathology examination of the removed tissue is a distinct step. Ask whether the estimate includes it, and whether any additional staining or specialist review would be a separate item.
Follow-up after discharge is often outside the surgical estimate. Ask what follow-up is proposed, where it happens, and whether those visits carry their own charges.
Pre-operative tests that were not available before you travelled may also sit outside the estimate. Ask which tests the hospital expects to repeat or add, and how those are priced.
The records that make an estimate more specific
A hospital can only estimate accurately if it understands your situation. The records you provide shape the assumptions behind the number. Ask the hospital which documents it needs to prepare a written estimate for HoLEP, and send those before you ask for a figure.
Useful records typically include your prostate and urinary test results, any imaging, a list of your current medicines, and a summary of previous prostate or urinary treatments. If you have had a biopsy or other prostate procedure, include those reports.
Ask how your existing prostate and urinary tests support the assessment. The treating clinician needs to confirm whether HoLEP is suitable for you, what the procedure is expected to address, and what follow-up is proposed afterwards. Those clinical decisions belong to the treating team, not to an estimate.
If a record is missing, ask what the hospital can do without it and what it would prefer to have. Do not delay urgent local care to complete a file for an overseas enquiry. If your symptoms are worsening, seek local medical assessment first.
Questions that turn an estimate into a plan
Bring a written list of questions to every cost conversation. The goal is not to negotiate; it is to understand the scope well enough to make a decision you can live with.
Ask what the estimate includes for the ward type, the expected length of stay, routine medicines, standard tests, and the procedure itself. Ask what is excluded, including pathology, follow-up, complications, and additional nights.
Ask how the hospital handles a change in plan, who authorises it, and how you are informed. Ask whether the estimate is fixed for a period or whether it can be revised before admission.
Ask what payment methods the hospital accepts, when payment is due, and whether a deposit is required. Ask for the hospital's written policy on refunds or credits if the plan changes. These are administrative questions the billing office can answer directly.
Ask whether an interpreter is available for billing discussions and whether that is included. If you are working with a coordination service, ask which parts of the process it handles and which remain between you and the hospital.
What to do next
Start by requesting the hospital's written estimate and its list of inclusions and exclusions. Ask the hospital to mark each item as included, excluded, or to be confirmed, and to name the person who will discuss changes with you.
Before you accept the figure, ask two questions that decide how much protection the estimate gives you. First, is the estimate valid until a stated date, or can it be revised before admission? Second, if the treating clinician recommends a change after you arrive, what happens to the price you were quoted? The answer tells you whether you are holding a fixed offer or an opening position.
Ask how the hospital documents a change. A revised written estimate, a signed consent form, or a message through the international office all leave a record; a verbal comment in a corridor does not. Confirm which of these the hospital uses and who is authorised to issue it. If the answer is vague, ask for it in writing before you travel.
Ask what happens if you decline a recommended change. You are entitled to understand the alternatives and the consequences of each option before you decide. The treating clinician can explain the clinical reasoning; the billing office can explain the cost of each path. Keep those two conversations separate so neither one pressures the other.
If a family member will accompany you, confirm whether the hospital will discuss the estimate with them and under what conditions. If you are travelling alone, ask how the hospital contacts you if a decision is needed and you are not able to respond immediately.
Keep every version of the estimate in one place, with the date you received it and the questions you asked. If a line changes, ask which assumption changed. That habit turns cost discussions into a review of facts rather than a negotiation about trust.
If you would like help organising your records and questions before you approach a hospital, you can send a brief summary through the free initial enquiry. The team checks the available diagnosis, records, and your main question, identifies missing information, and suggests the relevant next step. This is not a diagnosis or a promise of acceptance.
For more detail on the procedure itself, see the HoLEP prostate surgery reference. The hospital decides suitability, and any estimate is specific to your records and the provider's written terms.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.