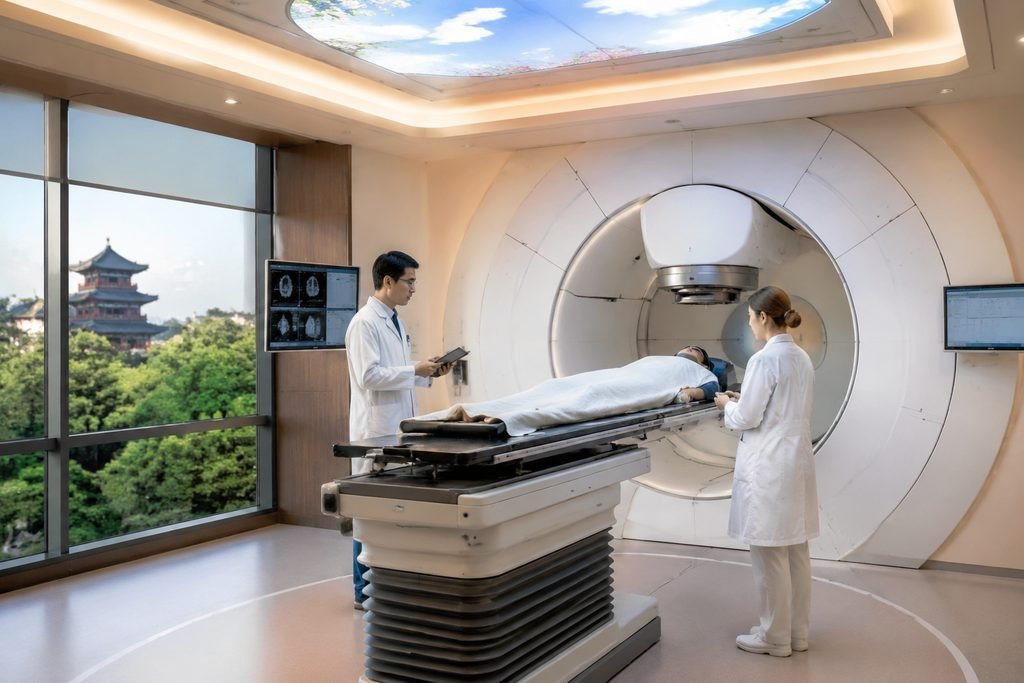
Why the named technique matters more than the city
Radiotherapy is not one procedure. It is a family of approaches that use ionising radiation to treat cancer, and the specific technique chosen for an individual patient depends on the tumour type, its location, its size, nearby healthy tissue, previous treatments and the overall treatment plan. The National Cancer Institute describes radiotherapy as treatment that uses high doses of radiation to kill cancer cells and shrink tumours, with the technique and schedule set by the individual plan.
For an overseas patient, this means the useful first question is not 'which hospital in China offers radiotherapy?' but 'which named technique is being proposed for me, and what does that name actually mean in my case?' Two patients with the same diagnosis can be offered different techniques because their anatomy, staging or prior treatment differs. A hospital may list several techniques on its website, but that listing does not tell you which one is suitable for you.
When you ask for the technique name, you are asking for a specific term the treating team can define. That name then becomes the anchor for every later question: what planning images are needed, what the delivery sessions involve, what alternatives exist, and what the team still needs to confirm before it can commit to a plan.
Consultation, planning and delivery are three different stages
Patients often use 'radiotherapy' as a single event, but the clinical process has distinct stages, and each stage answers a different question. Confusing them leads to unrealistic expectations about how quickly things can move and what a remote opinion can actually establish.
The consultation stage is where a radiation oncologist reviews your diagnosis, imaging, pathology and history, and decides whether radiotherapy is appropriate, what the treatment goal is, and which technique family is being considered. This is a clinical judgement, not an administrative booking. A records-based review can help clarify whether radiotherapy is a reasonable option and what information is missing, but it does not replace the treating team's in-person assessment.
The planning stage is where the technique becomes concrete. The team acquires the imaging it needs for treatment planning, defines the target volume and the organs at risk, and designs the radiation fields or arcs. This is where the named technique stops being a label and becomes a specific plan for your body. Planning requires your actual imaging and clinical data, not just a diagnosis name.
The delivery stage is where the plan is carried out over a schedule set by the treating team. The number of sessions, the interval between them and the total duration are clinical decisions based on the plan, not fixed packages you can compare like hotel nights. If you are planning travel, ask the treating team what the proposed schedule looks like for your case and what could change it.
Questions that change the next step
Not every question is equally useful. Some questions produce a clear next action; others produce a polite non-answer. The following questions are designed to surface information that actually affects your decision.
Ask: 'What is the exact name of the technique you are proposing for me, and what does it involve?' A specific answer lets you research the term and compare it with what other centres have said. A vague answer such as 'advanced radiotherapy' tells you the team has not yet formed a view on your case.
Ask: 'What planning imaging and records do you need from me before you can confirm the technique?' This distinguishes a provisional suggestion from a plan the team can stand behind. If the team needs updated imaging, a pathology report or a specialist review, you can arrange that before travelling.
Ask: 'What alternatives are you considering, and why is this technique preferred?' Radiotherapy decisions often involve trade-offs between target coverage and sparing healthy tissue. Understanding the alternatives helps you judge whether the recommendation is standard for your situation or a preference of that particular team.
Ask: 'What still needs to be confirmed in person before treatment can start?' This is the honest boundary question. A remote review can suggest a direction; the treating team confirms suitability after examining you and reviewing the full dataset.
Ask: 'If I travel, what is the sequence of appointments, and what would change it?' This is a planning question, not a clinical one, and the answer depends on the hospital's own scheduling. Ask the named provider rather than assuming a standard timeline.
A labelled planning example: how the same question changes the answer
Consider two hypothetical overseas patients, both with a diagnosis that can be treated with radiotherapy, both asking about care in China. This is an illustration of how the named technique changes the planning conversation, not medical advice or a real case.
Patient A has a small, well-defined tumour in a location where nearby healthy tissue is a concern. The team might name a technique that emphasises precise targeting and steep dose fall-off. The planning questions then focus on the imaging needed to define the target, the immobilisation used during delivery, and how the team verifies position at each session. The patient's travel planning depends on how many planning appointments are needed before delivery starts.
Patient B has a tumour near a moving organ, or has had previous radiotherapy to the same area. The team might name a different technique that accounts for motion or limits cumulative dose. The planning questions then focus on how motion is managed, what prior treatment records are needed, and whether the team can safely deliver more radiation. The same word, 'radiotherapy', leads to a different set of practical questions.
The lesson is not that one technique is better. It is that the technique name determines which follow-up questions are relevant. Without the name, you cannot tell whether the team has actually engaged with your case or is offering a generic description.
What a records-based opinion can and cannot establish
If you are not yet ready to travel, a records-based review can be a useful intermediate step. It can clarify whether radiotherapy is a plausible option, which technique family might be relevant, and what information is missing from your file. It can also help you decide whether travelling to China for treatment is worth pursuing.
What it cannot do is confirm final suitability, guarantee hospital acceptance or replace the treating team's in-person assessment. A remote reviewer works from documents, not from examining you. Imaging quality, pathology slides and prior treatment records all affect what can be concluded. If your records are incomplete, the honest answer may be that a useful opinion requires more information, not that a decision can be made on what is available.
This distinction matters for planning. If you treat a remote opinion as a confirmed treatment plan, you may travel before the treating team has actually accepted your case. If you treat it as a direction-setting step, you can use it to decide what to do next without overcommitting.
Practical preparation before you commit to travel
Once you have a named technique and a sense of what the treating team needs, the practical preparation becomes clearer. The goal is to arrive with the information the team needs to move from planning to delivery, and to understand what remains uncertain.
Ask the hospital what records it wants in advance and in what format. Imaging is often requested as DICOM files rather than printed films, and pathology may need to be reviewed locally. Confirm these details with the named provider rather than assuming a universal standard.
Ask how the team will communicate with you before and during your visit, and whether interpretation is available for clinical discussions. Consent conversations and treatment explanations need to be understood, not just translated in summary.
Ask what the proposed schedule looks like for your case and what could change it. Radiotherapy schedules are clinical decisions, and the treating team is the only source that can tell you what is realistic for you.
Finally, keep the decision boundary clear. The hospital decides suitability. An initial enquiry is free and does not require buying a proxy consultation. If you want to understand the technique being proposed and how planning and delivery are organised, the relevant reference page is Precision Radiotherapy.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.