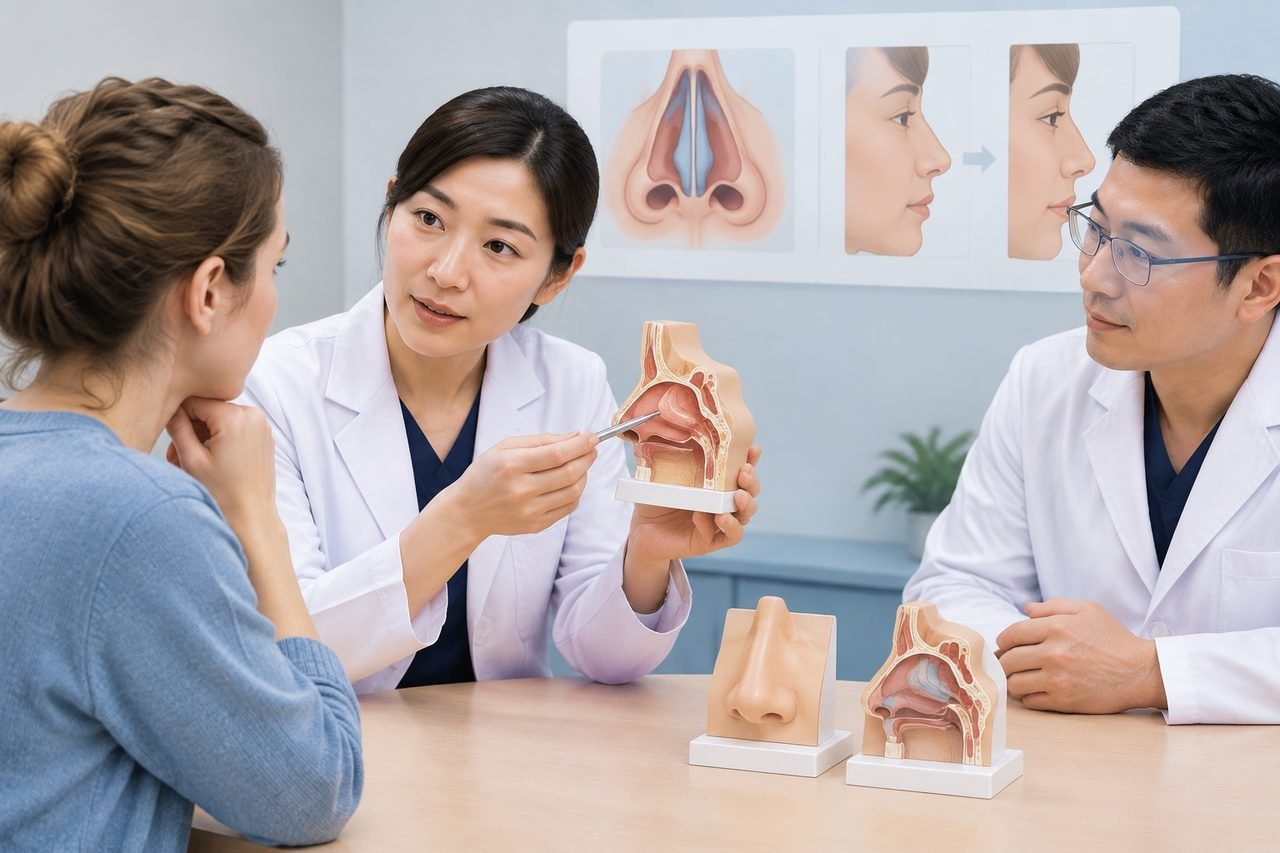
The two names describe different operations
A septoplasty addresses the nasal septum, the partition that divides the left and right nasal passages. The operation is intended to correct a deviated or otherwise problematic septum when it is contributing to obstruction or other symptoms. It is not primarily a cosmetic operation, although the surgeon may need to make some incisions inside the nose to reach the septum.
A septorhinoplasty combines septal work with reshaping of the external nose. The added 'rhino' element means the bony and cartilaginous framework of the nose may be altered, which changes appearance as well as, potentially, airflow. Because the goals are broader, the consent discussion, the imaging or photographic records, and the questions about what can realistically be achieved are also broader.
This distinction matters before you travel. A patient who expects a straight bridge and a patient who expects easier breathing are describing different outcomes. The operation name on a quotation or appointment letter should match the goal you actually have.
- Septoplasty: internal partition, breathing-focused goals.
- Septorhinoplasty: internal partition plus external nasal shape.
- Ask which structures the surgeon plans to modify and which will be left alone.
Why the surgeon may recommend one over the other
The recommendation should follow from the assessment, not from the name of the operation. An ENT surgeon will typically take a history of the breathing difficulty, examine the nose, and consider whether the septum, the nasal valves, the turbinates, the sinuses or allergy-related swelling are contributing. If the external shape is also a concern, the discussion shifts toward whether a septorhinoplasty is appropriate and whether it should be done at the same time.
Not every blocked nose needs surgery. Medical treatment, allergy management or other measures may be tried first, and the treating clinician decides whether an operation is suitable for you. A deviated septum found on examination does not by itself prove that surgery will relieve your symptoms.
If the proposal includes turbinate reduction, sinus surgery or cosmetic changes, those are separate elements. Ask whether they are part of the same operation, staged separately, or not planned at all. The answer changes the consent form, the recovery expectations and the follow-up schedule.
- What symptoms is the operation intended to improve?
- Which findings on examination support this plan?
- Are turbinates, sinuses or the external shape included, and why?
- What non-surgical options were considered?
Records that help an ENT team assess you
A useful pre-travel file is not a complete medical archive. It is a focused set of documents that lets a specialist understand your symptoms and prior treatment. Start with a short summary of when the breathing problem began, which side is affected, whether it is constant or seasonal, and what treatments you have already tried.
Include any previous nasal or sinus surgery notes, allergy testing, imaging reports and a list of current medicines. If you have photographs showing the external nose from several angles, they can help a surgeon understand your concerns, but they do not replace an in-person examination. A records-based opinion can discuss possibilities and questions; it cannot confirm final surgical suitability or hospital acceptance.
For an overseas enquiry, a brief summary is enough to begin. More detailed records can be shared after first contact, once the team knows what is relevant. Do not send passport numbers or payment details in an initial enquiry.
- Symptom history and which side is affected.
- Previous surgery, trauma or allergy records.
- Current medicines and relevant test results.
- Photographs if external shape is a concern.
Questions that change the next step
The answers to a few practical questions determine whether you plan a consultation, request a records-based opinion, or wait. Ask what the proposed operation is called in the surgeon's own notes, what it is intended to achieve, and what it will not achieve. Ask about the anaesthetic, the expected hospital stay, and what the follow-up schedule looks like.
Ask who will perform the operation and what their experience is with the specific procedure proposed. Ask what happens if the septum is more deviated than expected, or if the external shape needs a different approach once you are under anaesthesia. These are normal consent conversations, not signs of a problem.
If you are considering care in China, ask how communication will work before, during and after admission. Interpretation and hospital navigation can be arranged separately, but clinical decisions remain with the treating team.
- What is the exact procedure name in the surgical plan?
- What are the intended benefits and the known risks?
- What alternatives exist, including doing nothing?
- Who performs the operation, and where?
- What follow-up is required, and can it be done locally?
Planning example: two patients, two different questions
Planning example A: a patient whose main concern is a blocked left nostril, with no interest in changing appearance. The useful question is whether a septoplasty alone is proposed, and whether the surgeon expects the external shape to change as a side effect of reaching the septum. The consent discussion should focus on breathing, not on cosmetic outcomes. If the written plan names a septorhinoplasty, this patient should ask why the external framework is being addressed when appearance was not the goal.
Planning example B: a patient who wants both easier breathing and a straighter bridge. The useful question is whether a septorhinoplasty is proposed, which parts of the external nose the surgeon plans to alter, and how functional and appearance goals will be balanced if they pull in different directions. Photographs from several angles and a written statement of priorities help the surgeon understand what matters most. This patient should also ask what happens if the septum turns out to be less deviated than the external shape suggests, or the reverse.
Planning example C: a patient who has already had one nasal operation and now reports persistent blockage. The useful question is what the previous operation actually addressed, which records from that surgery are available, and whether the current proposal is a revision of the septum, the external framework, or both. Revision planning depends on what tissue remains and what was done before, so the operative note matters here more than in a first operation.
Planning example D: a patient whose blockage is seasonal and who has never tried medical treatment. The useful question is whether surgery is being proposed as a first step or after other measures have been tried. The treating clinician decides whether an operation is suitable; a records-based discussion can clarify what has and has not been attempted, but it cannot settle that question remotely.
These are planning examples, not medical advice, and they are not patient stories. The treating surgeon decides what is appropriate after examination. The point is that the same phrase, 'nose surgery', can describe two different operations with different consent discussions, and that the questions worth asking change with the goal.
One practical habit ties these examples together: write down your single main goal before the consultation, then check whether the proposed procedure name and the surgeon's description of what will change both point at that goal. If they do not match, that mismatch is the thing to resolve before consent, not after.
What to confirm before committing to travel
Before booking travel, confirm the appointment is with the relevant ENT or facial plastic surgery team, not a general clinic. Confirm what the hospital requires in terms of records, and whether a remote opinion is possible before you fly. Ask what the hospital's own written estimate includes and excludes, and what payment is made to the hospital versus any coordination service.
Ask how post-operative review will work if you return home. Some patients arrange a local ENT review; others stay longer. The treating team should explain what warning signs require urgent attention and how to reach them. Do not assume that a follow-up plan from one hospital applies to another.
Finally, confirm the operation name in writing. If the plan says septoplasty but your goal includes changing the external shape, clarify before consent. If the plan says septorhinoplasty but you only wanted breathing improvement, clarify that too.
- Written procedure name and intended goals.
- Hospital estimate scope and payment route.
- Post-operative review arrangements.
- Who to contact for urgent concerns.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.