Why the first question is not "do I need surgery?"
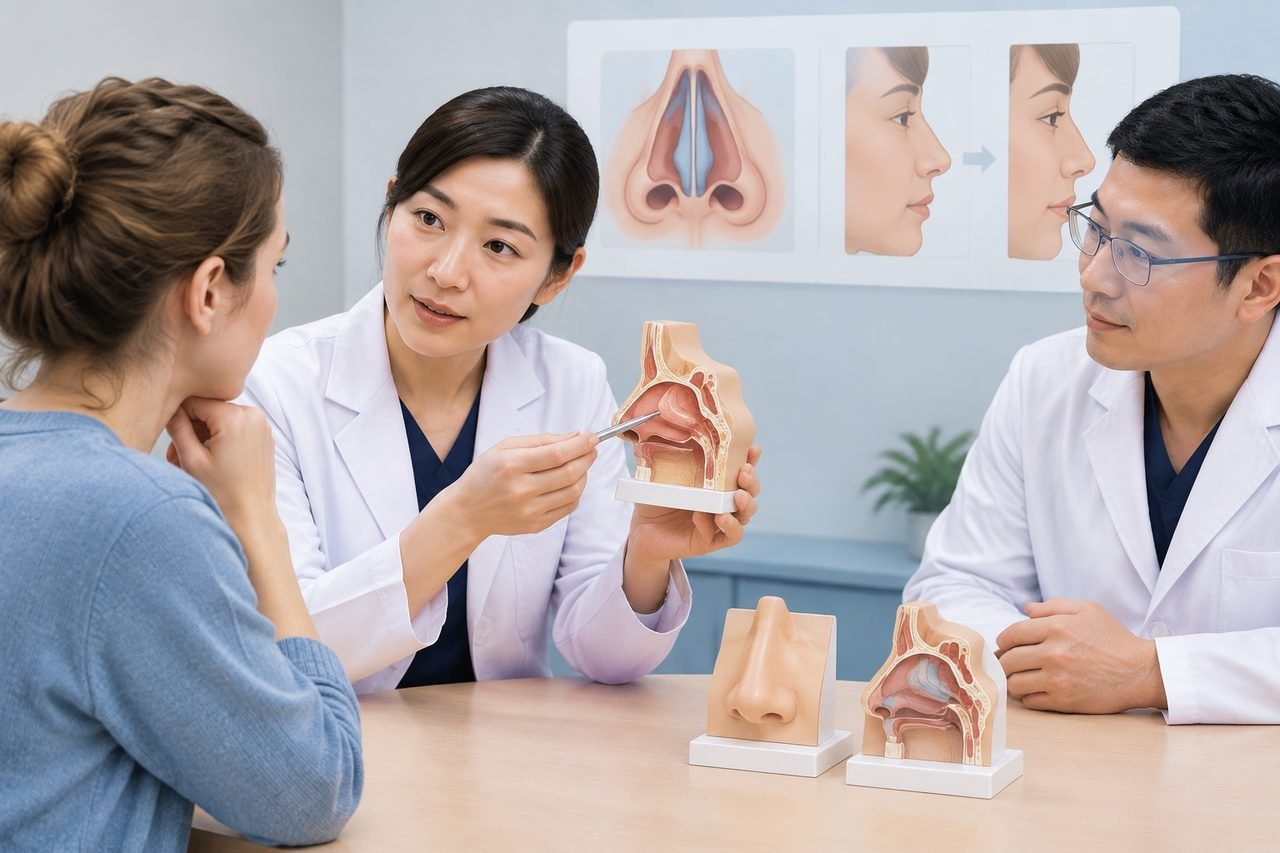
Patients often arrive at an ENT review already asking whether an operation is the answer. A more useful starting point is: what has actually been established about my nose and sinuses, and what has not? Endoscopic sinus surgery is performed through the nose to address sinus problems, but the proposed extent, the alternatives and the individual risks all require discussion with the surgeon. That discussion only makes sense once the diagnosis and the treatment history are clear.
This matters for overseas patients because the review is often compressed into a short visit. If you spend that visit asking for a surgical opinion, you may leave without knowing whether your symptoms are explained by the findings, whether a medicine-based plan has been properly tried, or whether the surgeon sees a clear indication at all. A surgical opinion is one output of an ENT review, not the definition of it.
- Ask what the current diagnosis is based on, and which findings support it.
- Ask which treatments have already been tried, for how long, and with what response.
- Ask what the surgeon would recommend if surgery were not available.
The records that make an ENT review useful
A review is only as good as the information in front of the clinician. For sinus concerns, the most useful records usually include prior imaging and its reports, any endoscopy notes, allergy or asthma assessments if relevant, a list of medicines and nasal treatments already used with dates and responses, and any previous sinus or nasal surgery records. If you have had several courses of treatment, a simple written timeline is more helpful than a folder of unlabelled prescriptions.
A planning example: a patient brings a scan report from two years ago, no endoscopy note, and a vague memory of "antibiotics that didn't work." The clinician cannot tell whether the treatment was adequate, whether the imaging is still current, or whether the symptoms have changed. The review may then focus on filling those gaps rather than on the surgical question. This is a planning illustration, not a real case.
If records are missing, that is a question to raise early with the coordinating team: which documents can be obtained, which need to be repeated, and which the hospital will accept in translation. Do not assume that a complete archive is required before any clinical assessment can begin, and do not assume that partial records are sufficient for a surgical plan.
- Imaging reports and, where possible, the images themselves.
- Endoscopy or examination notes, if any exist.
- A dated list of medicines, sprays, rinses and their effects.
- Previous surgery or procedure reports.
- Relevant allergy, asthma or immune assessments.
Questions that change the next step
Some questions are administrative; others genuinely change what happens next. The following are worth writing down before the appointment, because the answer to each one redirects the plan.
"What does my existing diagnosis explain, and what does it not explain?" If the findings account for the symptoms, the discussion moves to treatment options. If they do not, further assessment may be needed before any operation is considered.
"Which non-surgical options remain, and why?" If a medical plan has not been properly tried, the surgeon may recommend that first. If it has been tried and failed, that changes the weight given to surgery.
"What is the intended benefit, and how would we know it worked?" This turns a vague hope into something you can assess afterwards.
"What are the uncertainties in my case?" A surgeon who can name the uncertainties is giving you more useful information than one who offers certainty.
"What would you do if this were your own nose?" This is not a trick question; it often surfaces the reasoning behind a recommendation.
How to weigh a surgical recommendation without rushing
If surgery is recommended, the useful next step is not to accept or refuse immediately, but to understand the proposal. Ask what would be done, why that extent rather than a smaller or larger one, what the alternatives are, and what the individual risks are for you. These are exactly the points that require discussion with the surgeon, and they are reasonable to take away and consider.
For patients travelling to China, it also helps to separate clinical questions from logistical ones. Clinical questions belong to the ENT team. Logistical questions — appointment timing, interpretation, how records are shared, what happens after the visit — can be raised with the coordinating team. Keeping the two separate prevents logistics from crowding out the clinical discussion.
A practical boundary: if your symptoms are worsening, or you have fever, facial swelling, visual changes or severe pain, seek local medical care rather than waiting for an overseas enquiry to progress. An overseas planning process should not delay assessment of an acute problem.
- Write your three most important questions on one page and hand them to the clinician.
- Ask for the reasoning, not just the recommendation.
- Ask what would change the plan later.
- Keep a copy of whatever is written down at the visit.
What an initial enquiry can and cannot do
An initial enquiry is free and non-clinical. It is a way to describe your situation briefly, ask what records would be useful, and find out what the next practical step might be. It is not a diagnosis, and it does not establish whether surgery is appropriate or whether a hospital will accept you. Those decisions belong to the treating clinicians.
A proxy consultation, where a doctor takes your records to a specialist while you remain at home, is optional and not a prerequisite for an appointment. Some patients find it useful for clarifying whether travelling is worthwhile; others prefer to arrange a direct specialist appointment. Either way, the hospital decides suitability, and no coordination service can promise acceptance or an outcome.
If you are still at the stage of deciding whether to pursue an ENT review in China at all, the most useful thing you can do now is assemble a clear summary of your symptoms, treatments and records, and note the specific questions you want answered. That preparation is what makes any review, in any country, more productive.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.