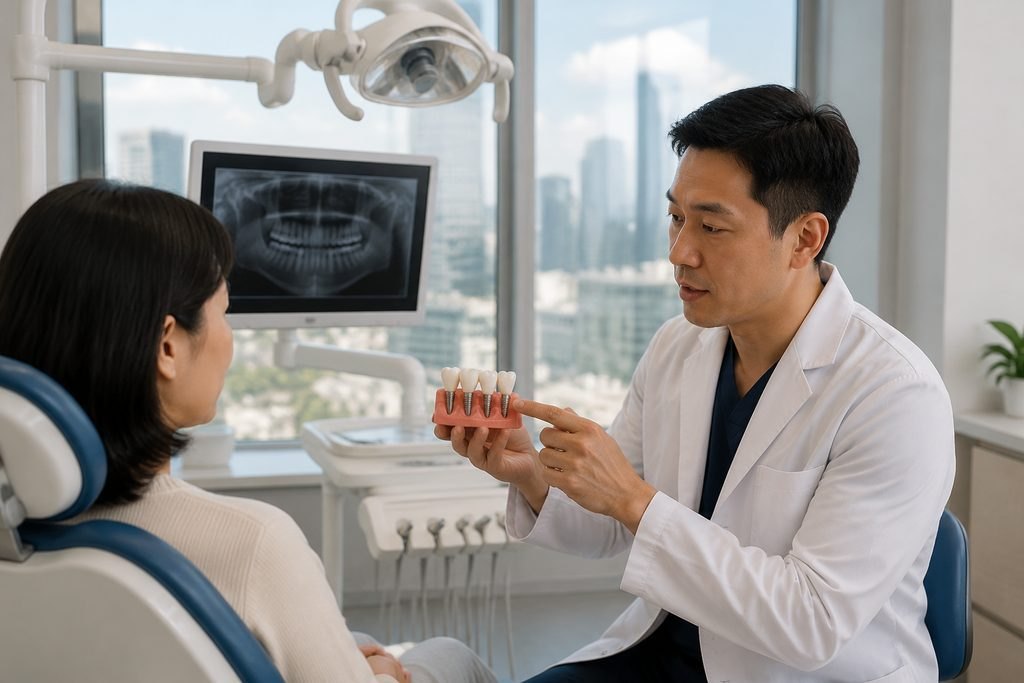
Start with the exact record that is missing, not a general archive
The practical question is not whether you have 'enough' records. It is which part of the All-on-4 pathway the missing document supports. Full-arch implant treatment has at least two distinct phases: implant placement and the restorative phase that provides the replacement teeth. A record that helps one phase may be irrelevant to the other.
If a panoramic X-ray is missing, the treating dentist may lack a broad view of the jaw and existing teeth. If a CBCT scan is missing, the team may lack the three-dimensional detail some implant planning requires. Those are different gaps. Ask the treating team which specific image it needs and what each missing image prevents it from confirming, rather than assuming one type of scan substitutes for another.
Clinical notes matter for a different reason. They may record previous extractions, gum treatment, failed implants, infections or medications that affect healing. A treatment plan from another clinic shows what was proposed, not necessarily what was completed. A laboratory or prosthesis record shows what the current teeth or denture are made from and when they were fitted.
Ask the previous clinic for a named list rather than a vague request for 'my file'. Useful items may include: recent radiographs in original digital format, any CBCT scan with the viewing software or DICOM files, clinical notes covering the last few years, a list of current medicines, and details of previous implant or gum surgery. If you never received a written plan, say so plainly. That gap is itself information the new team needs.
Who to ask, and what to say when the clinic is slow or unresponsive
The first request goes to the clinic that holds the record. That may be a general dentist, a specialist practice, a hospital dental department or the laboratory that made a prosthesis. Each holds different pieces. A single request to the wrong office can waste weeks.
Write a short message that names the document, the approximate date and the purpose. For example: 'Please send the CBCT scan taken in March 2024 in DICOM format, plus the clinical notes from the implant consultation.' Ask whether there is a records-release form or a fee. Ask how the file will be sent and whether the original image format can be preserved. A compressed screenshot may be unreadable for planning purposes.
If the clinic does not reply, ask again in writing and keep the correspondence. If you are outside China and the records are in China, a relative or a local contact may be able to collect a copy in person, subject to that clinic's own identity and authorization rules. Do not assume any particular release process; ask the holder what it requires.
If records genuinely cannot be obtained, do not invent a history to fill the gap. Tell the new clinical team what is unavailable and why. They can then decide whether to proceed on a provisional basis, request specific new imaging, or ask you to attend in person before giving an opinion. That decision belongs to the treating dentist, not to a coordination service.
How a missing record changes the next step in China
A missing record can change the next step in three ways. First, it may limit the scope of a remote opinion. A dentist reviewing photographs and an old panoramic image can discuss general options, but may not be able to confirm bone suitability, implant position or whether a graft is needed. Second, it may mean new imaging is required in China before a final plan. Third, it may affect sequencing: the team may need to complete the restorative assessment before confirming the surgical stage.
This is why a preliminary reply is not the same as a confirmed plan. A reply may say that All-on-4 is 'possible in principle' while noting that the final decision depends on a CBCT and a clinical examination. That wording is not evasive. It reflects the difference between a records-based impression and a treatment decision made after direct assessment.
Ask the team to state, in writing, which records they have reviewed, which are still missing, and what each gap prevents them from confirming. That turns a vague 'we need more information' into a specific action list. It also helps you avoid paying for duplicate imaging or repeating a test that was already done elsewhere.
Do not treat a remote review as final eligibility or hospital acceptance. A records-based opinion can guide preparation and highlight questions, but the treating hospital confirms suitability after its own assessment.
Questions to ask about the provisional and final restoration
All-on-4 is not only a surgical procedure. The replacement teeth are part of the treatment, and the records that support the restorative phase are often overlooked. Ask the team how it plans the provisional restoration and the final restoration, and what records it needs for each stage.
A provisional restoration is typically a temporary set of teeth used while healing and implant integration are assessed. A final restoration is the longer-term prosthesis. The design, material and timing depend on the clinical situation, and the treating team decides when each stage is appropriate. Do not assume that a temporary prosthesis is the same as the final one, or that the final teeth are fitted at the same appointment as the implants.
Ask specifically: Does the plan cover the upper arch, the lower arch, or both? Are they staged separately? How many visits does the team propose, and what happens at each one? What records are still needed before the provisional and final stages can be planned? If the previous clinic made a denture or bridge, bring its details, because the new team may need to know what you have been wearing and for how long.
If the answer is that the number of visits depends on healing and the restorative assessment, that is a clinical reality, not a lack of planning. Ask what the team will confirm at each visit and what would change the sequence.
What to send in a first enquiry, and what to leave out
A first enquiry does not need a complete medical archive. It needs enough to identify the question and route it to the right clinical team. A short summary is usually more useful than a large unlabelled file dump.
A practical first message can include: your main concern, whether you are asking about the upper arch, lower arch or both, what records you already have, what is missing, and your general question about next steps. Attach only the key documents you already hold. Do not send passport numbers, card details or a full lifetime of records at this stage.
If you are working with a coordination service, its role is to help organise records, clarify questions and request a specialist appointment. It does not decide suitability, prescribe treatment or promise that a hospital will accept the case. Those decisions belong to the treating clinicians.
ChinaSpecialistCare can help international patients organise dental records, arrange interpretation and request a specialist appointment for All-on-4 assessment. The hospital reviews the records and decides whether it can assess you remotely or needs an in-person examination. An initial enquiry is free and does not require buying a proxy consultation.
Maintenance, limits and the next practical step
Dental implants support replacement teeth, and the restorative phase is a separate part of treatment from placement. Ongoing maintenance matters for the long-term condition of the implants and the surrounding tissues. Ask the treating team what maintenance it recommends, how often it wants to review you, and what can be done locally between visits.
Be cautious about any plan that promises immediate permanent teeth, guarantees that four implants will suit every jaw, or claims that all treatment can be completed in one trip. Those are clinical and scheduling decisions, not marketing promises. The treating dentist must confirm suitability, staging and the number of visits after reviewing your records and, where needed, examining you directly.
If you have current pain, swelling, a loose prosthesis or difficulty eating, seek local dental assessment rather than waiting for an overseas enquiry. Urgent symptoms take priority over travel planning.
The next step is to list what is missing, request those specific records from the holder, and send a short summary with your main question. The hospital will then tell you what it can confirm from the records and what still requires an in-person assessment. You can start with a free initial enquiry.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.