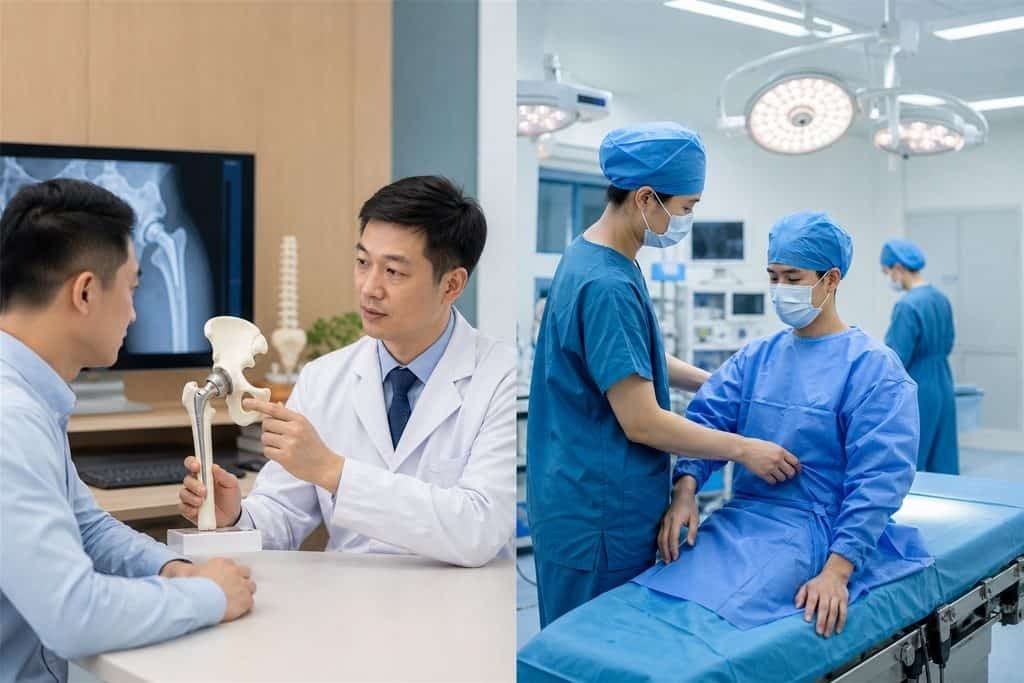
Why a new scan can change the proposed plan
Hip replacement can be performed through different surgical approaches, and the anterior approach reaches the hip from the front. Suitability for any approach depends on the individual patient's anatomy, examination findings and imaging, so it is assessed case by case rather than assumed from a diagnosis alone.
When you receive new imaging, a new examination report or an updated clinical summary, the surgeon may revise the plan. The revision might concern the approach itself, the type or extent of the implant, the anticipated rehabilitation pathway, or the timing of surgery. Sometimes the plan stays the same but the reasoning behind it becomes clearer. Either way, the practical question for you is not whether the plan changed, but which specific decisions changed and what they now depend on.
This matters because an overseas patient often makes travel, accommodation and work arrangements based on an earlier plan. If the approach or implant scope shifts, those arrangements may need to be revisited. It is reasonable to ask for an updated written summary before you commit to dates or travel.
Reconfirm whether the anterior approach is still proposed
The first thing to clarify is whether the anterior approach is still the intended route. Ask the surgeon directly: does the new information change your recommendation about the surgical approach, and if so, why? A clear answer should refer to your specific findings, not to general statements that one approach is better than another.
If the approach is unchanged, ask what the new information confirms. If it has changed, ask what the alternative approach would involve and what the trade-offs are for your situation. You do not need to become an expert in surgical technique; you need to understand what is being proposed for you and what the surgeon expects it to achieve.
It also helps to ask whether the decision is final or provisional. Some plans are confirmed only after the surgical team reviews everything together, and some details are settled on the day of surgery. Knowing which parts are settled and which remain open prevents misunderstandings later.
Clarify the implant plan as a separate decision
The surgical approach and the implant choice are separate decisions. A change in one does not automatically mean a change in the other, and a stable approach does not guarantee that the implant plan is fixed. Ask which components are proposed, what materials or design features are involved, and whether the new findings affect that choice.
If the implant plan has changed, ask what the new plan is intended to address. If it has not changed, ask whether the earlier implant plan still applies and whether anything about it remains undecided. It is also reasonable to ask what would happen if a particular component were not available at the time of surgery, and how that would be communicated to you.
For an overseas patient, the implant plan often affects the written estimate. Ask the hospital or coordinating team to confirm, in writing, what the current quote includes, what it excludes, and what remains undecided. Do not assume that a previous estimate still applies after a plan change.
Ask how rehabilitation and home follow-up would work
Rehabilitation planning is part of the surgical plan, not an afterthought. Ask how the proposed approach and implant plan affect the expected rehabilitation pathway, what restrictions or precautions apply, and who will supervise the early stages. The answers depend on your individual assessment, so treat them as questions for the treating team rather than assumptions.
If you are travelling from another country, ask how follow-up would be arranged once you return home. Which records would be sent to your local clinician, and what would the receiving physiotherapist or doctor need to know? The receiving clinician makes their own assessment, so the goal is to give them a clear picture of what was done and what was recommended.
It is also worth asking what would prompt a review before you travel home, and how you would contact the surgical team if a concern arose after discharge. These are practical questions that affect how you plan the trip, not clinical decisions you need to make yourself.
What to send and what to ask for in writing
When a plan changes, the records that matter most are the ones that prompted the change. That means the new imaging report, the new examination findings, and any updated clinical summary. Send these to the treating team or coordinating contact so the surgeon is reviewing the same information you are. If a report has not yet been issued, say so rather than sending an older version and hoping it is treated as current.
Ask for an updated written summary that states the proposed approach, the implant plan, the rehabilitation outline, and any points still to be confirmed. A written summary is easier to check than a conversation recalled from memory, and it gives your local clinician something concrete to work from. If the reply arrives as a short message rather than a document, ask whether a fuller written version can be provided.
If something in the summary is unclear, ask a specific question rather than a general one. For example, ask whether the anterior approach is still proposed, or whether the implant plan has changed, rather than asking whether everything is fine. Specific questions tend to produce specific answers, and they make it easier for the surgeon to answer without guessing what you are worried about.
It also helps to say what you have already arranged. If you have booked flights, requested leave from work, or told your local physiotherapist to expect you, mention it. The surgical team cannot plan around commitments it does not know about, and a change that looks minor on paper can affect a travel date.
Keep a simple record of what you sent and when. If two people are corresponding on your behalf, one list of documents and questions prevents the same item being sent twice or a question being answered for an earlier version of the file. This is administrative housekeeping, not a clinical judgement, and it saves time when a decision is time-sensitive.
Finally, decide in advance which answers you need before you can act. Some points, such as the proposed approach, affect whether you travel at all. Others, such as the final implant component, may reasonably be settled closer to surgery. Sorting your questions into these two groups stops a minor open item from holding up a decision that is otherwise ready to make.
- The new imaging report or scan findings
- The updated examination or clinical summary
- Any previous written plan or estimate, so changes can be compared
- Your main question in one or two sentences
What a reply confirms, and what it does not
A written reply from the surgical team can confirm the current proposed approach, the implant plan as it stands, and the rehabilitation outline. It can also confirm which points remain open. That is useful, but it is not the same as final surgical clearance or a guarantee of hospital acceptance.
Suitability for surgery, the final implant decision and the rehabilitation plan are determined by the treating hospital and licensed clinicians after they assess you. A records-based review before travel can clarify the plan and identify missing information, but it does not replace an in-person assessment. If a step cannot be completed before you travel, ask what would need to be confirmed on arrival and how that would affect the schedule.
If the plan cannot be confirmed remotely, the fallback is usually to plan for an in-person assessment before any surgery is scheduled. Ask the hospital how that would work and what it would mean for your travel dates.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.