Start with the question the clinical team must answer
A bile duct stricture means the duct that carries bile from the liver toward the intestine is narrowed. The practical decision is rarely 'which treatment do I pick from an article'. It is whether bile flow is currently blocked enough to need drainage, and what further assessment is required before anyone can judge the underlying cause and the appropriate next step. Those two questions are connected but not identical, and a clinical team needs your records to address them.
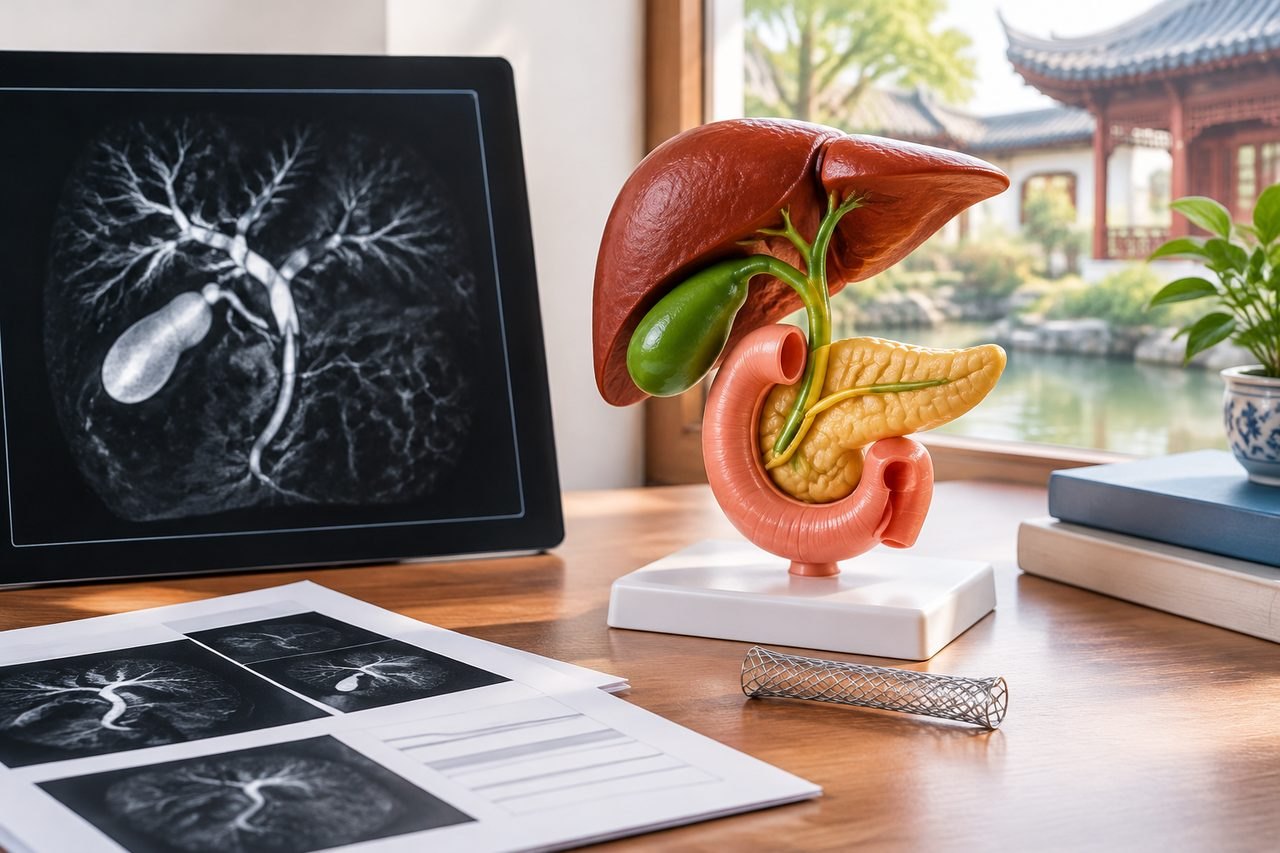
When a duct is blocked, a stent can help drainage. The approach and follow-up depend on assessment. That is the whole clinical anchor here, and it is deliberately limited. It does not tell you whether you need a stent, whether an existing stent should be exchanged, or what the stricture is caused by. Those are decisions for the treating clinicians after they review your imaging, laboratory results and procedure reports.
So the first message to any China clinical team should be a question, not a request for a specific operation. Something like: 'I have a documented bile duct stricture. I want to understand whether drainage is needed now and what further assessment you would recommend. Here are my MRCP and ERCP reports and my stent history.' That framing gives the clinician something to assess rather than a procedure to schedule.
What MRCP and ERCP reports actually tell the team
MRCP and ERCP are different examinations and their reports answer different questions. MRCP is a magnetic resonance imaging study of the biliary and pancreatic ducts. It shows the ducts without instrumenting them. ERCP is an endoscopic procedure in which a camera and instruments are passed through the upper digestive tract into the bile duct; it can both image and treat, for example by placing a stent. A report from each carries different information, and a clinician reviewing your case will want to know which was done, when, and what it showed.
For the stricture itself, the useful details are the location, the length, how narrow it appears, whether the upstream ducts are dilated, and whether the report describes any mass, stone, inflammation or previous intervention nearby. For drainage, the useful details are whether bile flow was obstructed at the time, what was done about it, and whether the report describes a successful or incomplete drainage attempt. These are the specifics a clinician uses to judge urgency and plan further assessment.
If you only have a summary letter and not the full report, say so. A one-line conclusion such as 'stricture seen' is far less useful than the radiologist's or endoscopist's description. Ask the original hospital for the full report and, where available, the images or a disc. You do not need to send a complete archive in a first message, but you should be able to say what exists and what does not.
Existing stents: placement, timing and what to ask
If you already have a biliary stent, the single most important thing to clarify is what kind it is and when it was placed. Stents are not all the same. Some are plastic and some are metal; some are intended to be removed or exchanged and some are intended to remain. A report that says 'stent inserted' without saying which type, where, and on what date leaves the receiving team unable to judge whether the current situation is expected, whether the stent may be blocked, or whether any change is needed.
This is also where a misunderstanding can arise. A stent that was placed months ago is not automatically still working, and a stent that was described as temporary is not automatically due for removal on a fixed date. The exchange interval depends on the stent type, the reason it was placed, the underlying diagnosis and the treating team's assessment. Do not treat any article, including this one, as a schedule. Ask the team that placed it, and ask the China team what they would need to know to advise you.
A practical way to frame the question is: 'I have a biliary stent placed on [date] at [hospital]. The report describes it as [type, if known]. I want to know whether it is still functioning and whether further assessment or a change is needed.' If you do not know the type, say that plainly. The clinician can often identify it from the procedure report or imaging, but only if you send them.
Drainage now versus further assessment first
These are not competing options; they answer different questions. Drainage addresses the immediate problem of bile not flowing properly. Further assessment addresses why the duct is narrowed and what the longer-term plan should be. In some situations drainage is needed urgently and assessment follows. In others, the team may judge that assessment can proceed first. You cannot decide this from a description of your diagnosis alone, and neither can a coordinator.
What you can do is make sure the clinical team has what it needs to make that judgement. That means the reports described above, current blood tests if available, and a clear statement of your symptoms. Symptoms matter because they change urgency. Fever, worsening pain, jaundice that is deepening, confusion or vomiting are not things to manage by planning an overseas appointment. They require local urgent assessment. If you are stable and your question is about elective assessment in China, that is a different situation and can be planned.
When you contact a China team, ask directly: 'Based on these records, do you consider drainage necessary now, or can assessment proceed first? What additional information would change that view?' That question is answerable. 'Which treatment should I choose?' is not, until the assessment is done.
What further assessment may involve, and what to confirm
Further assessment of a bile duct stricture can include repeat imaging, blood tests, and sometimes an endoscopic procedure to obtain tissue or to look at the duct directly. The specific tests depend on what has already been done and what the team suspects. Because the underlying causes of stricture differ, the assessment pathway differs too. This is why a generic list of tests is not useful, and why you should ask the receiving clinician what they would recommend in your case rather than assembling a test list yourself.
There is also a practical point about who orders what. In many systems, a specialist must order a diagnostic test; you cannot simply book it as a standalone item. If you are planning care in China, ask the hospital or the coordinating team how a proposed test would be arranged, whether it requires a specialist appointment first, and what the expected sequence is. Do not assume that a test you have read about is available on request, or that it will be scheduled in a particular order.
Finally, distinguish assessment from clearance. A records-based review can give a clinician a view on your situation and on what should happen next. It does not by itself establish that a procedure is appropriate, that the hospital will accept you, or that a particular plan will be followed. Those are decisions for the treating team after they have seen you and your records. Treat any preliminary reply as a starting point for discussion, not as a final plan.
Preparing your records and the next step
The most useful thing you can do before contacting any China clinical team is to organise what you already have. Gather the full MRCP report, the full ERCP report if one was done, any procedure notes about stent placement, recent blood tests, and a short written summary of your symptoms and their timeline. If you have imaging discs, note that they exist. You do not need to send everything in a first message; a brief summary is enough to start, and the team can tell you what else is needed.
When you are ready, you can send a short summary through the enquiry form, email or WhatsApp. ChinaSpecialistCare's team can check the available diagnosis and records, identify what is missing, and suggest the relevant next step. That initial review is free and is not a diagnosis or a promise of acceptance. If a records-based specialist opinion is useful before you travel, that can be discussed separately; it is optional and not a prerequisite for every appointment. You can also ask about specialist matching and appointment coordination if you decide to proceed.
The one question to keep at the centre of every message is the one this article started with: is drainage needed now, and what further assessment does the team recommend? Everything else follows from the answer to that.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.