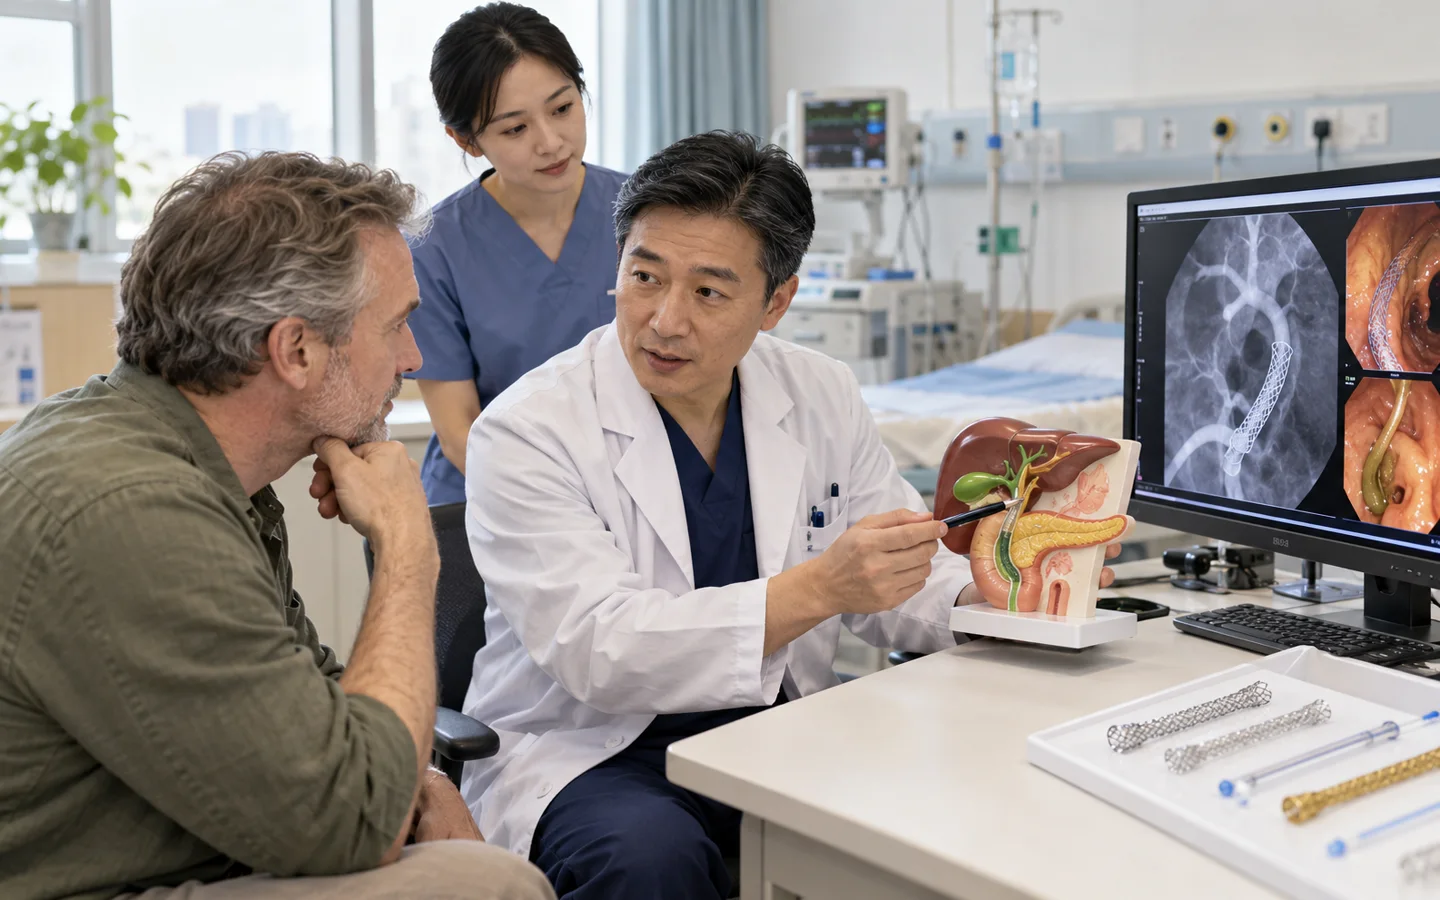
A biliary stent bypasses or opens a narrowed bile duct
A small tube is placed across a stricture so bile can flow into the intestine or an external drainage system. Stents may relieve jaundice, infection or itching and support later surgery or cancer treatment.
Benign stones or scar, postoperative injury and malignant obstruction require different materials and schedules. A stent is a management step, not necessarily treatment of the underlying cause.
Ask whether it is temporary or long term, when it must be exchanged or removed and what symptoms suggest blockage or infection.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about bile duct stenting.
- Obstructive jaundice from a stone, benign stricture or tumor.
- Acute cholangitis requiring drainage after stabilization.
- A postoperative bile-duct leak or narrowing.
- A patient needing decompression before surgery or systemic therapy.
What the specialist team must confirm
The team reviews liver tests, bilirubin trend, ultrasound CT or MRCP, infection and blood cultures, anatomy, previous surgery or ERCP, tissue diagnosis when needed, anticoagulation and whether endoscopic, percutaneous or surgical drainage is safest.
Key points for this treatment

From obstruction mapping to durable drainage
The team selects a route and stent that support the wider treatment plan without closing future surgical or diagnostic options.
Patency and infection symptoms matter after placement
Bilirubin, fever, pain and liver tests show whether drainage is working. Antibiotics are used when infection is present rather than as a substitute for drainage.
Temporary stents must be tracked actively. Cancer cases coordinate stent function with chemotherapy, radiotherapy or surgical planning.
Risks, limits and realistic expectations
Risks include pancreatitis, bleeding, infection, perforation, stent migration or blockage, recurrent jaundice and inability to cross the narrowing. Repeat procedures may be necessary.
Fever with chills, worsening jaundice, severe abdominal pain, confusion, low blood pressure or persistent vomiting requires emergency local assessment.