What the operation is meant to achieve, and what it cannot promise
Bladder removal, also called radical cystectomy, is one treatment approach for bladder cancer. It is not the only approach, and not every bladder cancer requires it. The operation removes the bladder; in many cases the surgical team also addresses nearby lymph nodes and, depending on the cancer and the patient, other organs. The goal is cancer control, and the operation is planned around staging and the individual case.
What it cannot do is equally important. It cannot restore a normal bladder, and it cannot guarantee that cancer will not return. It does not by itself answer whether you will need further treatment after surgery, such as chemotherapy, immunotherapy or radiotherapy. Those decisions depend on pathology results and the treating team's assessment.
This is why the first useful question is not 'can I have this operation in China?' but 'what is this operation intended to achieve in my case, and what will it not achieve?' Ask the surgical team to state the treatment goal in plain terms: curative intent, control of symptoms, or something else. Ask what would make them reconsider the plan. If the answer is vague, that is a signal to request a records-based review before committing to travel.
How staging shapes the decision before any surgery
Staging describes how far the cancer has spread. It is the main factor that determines whether bladder removal is appropriate, what else may need to be removed, and whether surgery should come before or after other treatment. Staging is not a single test. It usually combines imaging, examination under anaesthesia, and pathology from a biopsy or from a transurethral resection.
For an overseas patient, the practical problem is that staging may be incomplete or based on tests done elsewhere. The receiving hospital will want to understand what has already been done and whether it accepts those results or needs to repeat parts of the assessment. Do not assume that existing scans and biopsy reports will be accepted as they are. Ask the hospital directly: which records do you need, in what form, and which tests would you repeat here?
A records-based opinion can clarify whether the available information is enough to discuss surgery, but it does not establish final eligibility or hospital acceptance. Those are confirmed only after the treating team has reviewed the case, and sometimes only after further tests in China. Treat any preliminary opinion as a step in the process, not a booking.
Urinary reconstruction: the decision that changes daily life
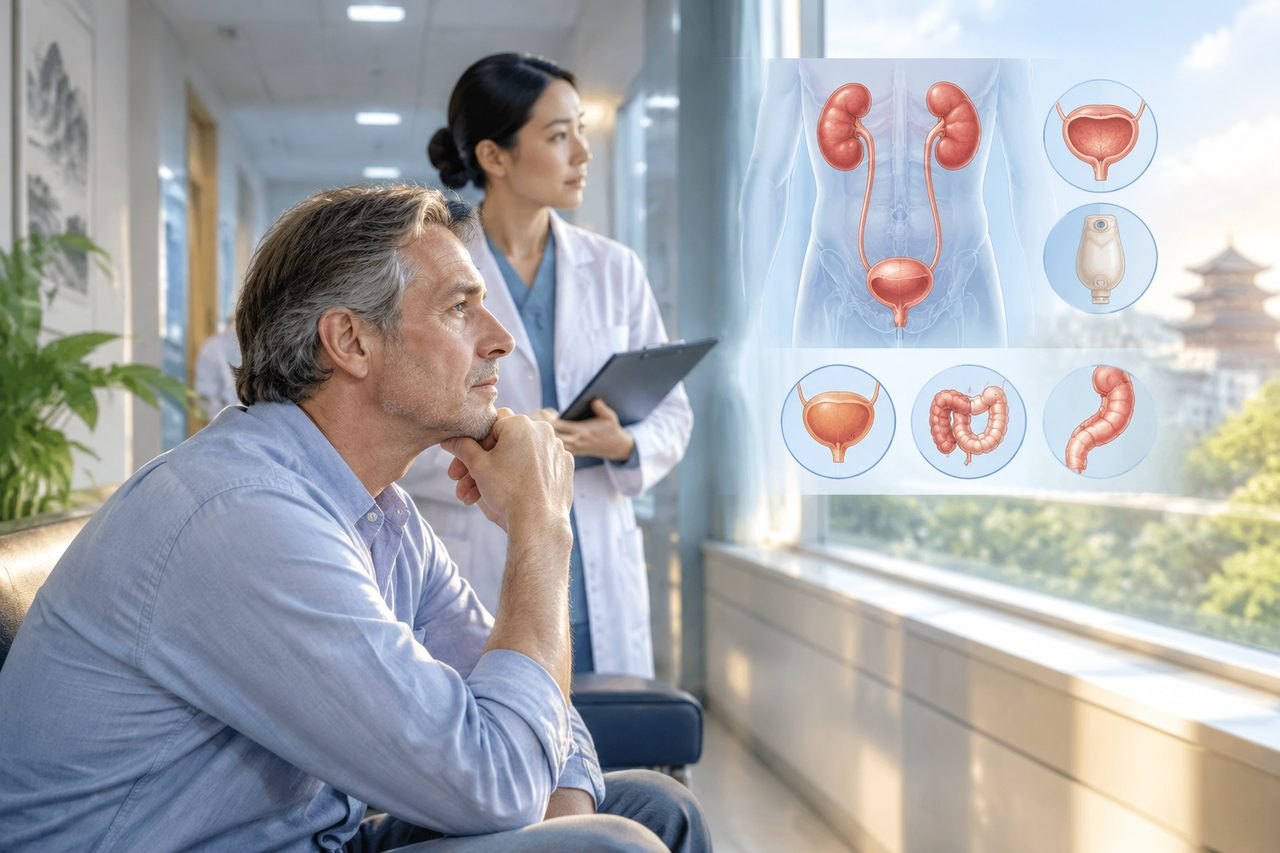
When the bladder is removed, urine must leave the body by another route. The main options include a urostomy with an external bag, a continent pouch that is emptied with a catheter, and a neobladder constructed from bowel that connects to the urethra. Each has different implications for surgery, recovery, body image, daily routine and follow-up.
The choice is not simply a preference. It depends on the cancer stage and location, whether the urethra can be preserved, previous surgery or radiotherapy, kidney function, bowel health, manual dexterity, and the patient's willingness to manage a particular routine. A neobladder does not suit everyone, and it does not guarantee normal urination or continence. A stoma is not a failure of surgical ambition; for some patients it is the safer or more reliable option.
Ask the surgical team to explain which reconstructions they consider suitable for you and why. Ask what each option means for your daily life, what training or support you would receive, and what could go wrong. Ask who would manage stoma or catheter care after discharge, and whether that support is available in your home country. These are practical questions, not clinical decisions you should make alone.
Aftercare and follow-up: what must be arranged before discharge
Bladder removal is major surgery. After the operation, care focuses on healing, kidney and bowel function, prevention of complications, and learning to manage the new urinary route. The length of stay and the pace of recovery vary between patients and are not fixed in advance. Ask the hospital what its discharge planning involves and what it expects you to be able to do before you leave.
Follow-up after bladder removal is not optional. It typically includes regular review, imaging and blood tests, and monitoring for recurrence or complications. For an overseas patient, the key question is how that follow-up will work across countries. Will the Chinese hospital provide a written follow-up plan? Can it communicate with your local doctor? What should your local team monitor, and when should you contact them?
Do not assume that follow-up can be managed remotely without a local clinician. Ask the hospital what it will provide in writing, in what language, and whether it will respond to questions from your home doctor. If the answers are unclear, resolve them before travel rather than after discharge.
What to prepare and what to ask the treating team
Preparation for an overseas patient is mostly about records and questions. The hospital needs enough information to assess staging and surgical suitability. You do not need to send a complete medical archive at first contact. A short summary of the diagnosis, the main question, and the key reports is enough to start.
Useful records to discuss with the receiving team include pathology reports from biopsy or resection, imaging reports and images if available, operation notes from previous surgery, discharge summaries, current medication lists, and relevant blood test results. Ask the hospital which of these it needs, in what format, and whether translations are required. Do not assume a particular document is mandatory; confirm it.
Prepare a short list of questions for the surgical consultation. Ask what the operation is intended to achieve, what will be removed, which reconstruction is proposed and why, what the alternatives are, what complications are relevant to you, what follow-up is planned, and what support is available after discharge. Ask what would make the team change the plan. Write the answers down.
Cost is a separate conversation. Hospital fees, our coordination fees and travel costs are distinct. Ask the hospital for a written estimate that states what is included, what is excluded, and what remains undecided until after assessment. Do not rely on a verbal figure or on another patient's experience.
- Pathology reports from biopsy or previous surgery.
- Imaging reports and, where possible, the images themselves.
- Operation notes and discharge summaries from earlier treatment.
- Current medication list and relevant blood test results.
- A written list of your questions, with space to record answers.
Where China fits, and what remains uncertain
China has tertiary hospitals with urology and cancer services, and some international patients seek care there. Whether a particular hospital is suitable for your case depends on its experience with your stage and reconstruction, its language support, and its willingness to accept your records. These are questions to confirm with the named hospital, not assumptions to make from a website.
It is also worth being clear about what an enquiry can and cannot do. A free initial case review checks the available diagnosis, records and your main question, identifies missing information and suggests a relevant next step. It is not a diagnosis and not a promise of acceptance. A proxy consultation, where a doctor takes your records to a hospital specialist while you remain at home, is optional and not a prerequisite for every appointment or operation.
If your symptoms are worsening, or if you have bleeding, pain, fever or difficulty passing urine, seek local medical care first. Do not delay urgent assessment for an overseas enquiry. For non-urgent planning, start with a short summary through the enquiry form, email or WhatsApp, and share fuller records only after first contact.
The next practical step is to ask the treating hospital, in writing, what it needs to assess your case and what it can and cannot confirm before you travel. That answer, not a general guide, is what should shape your decision.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.