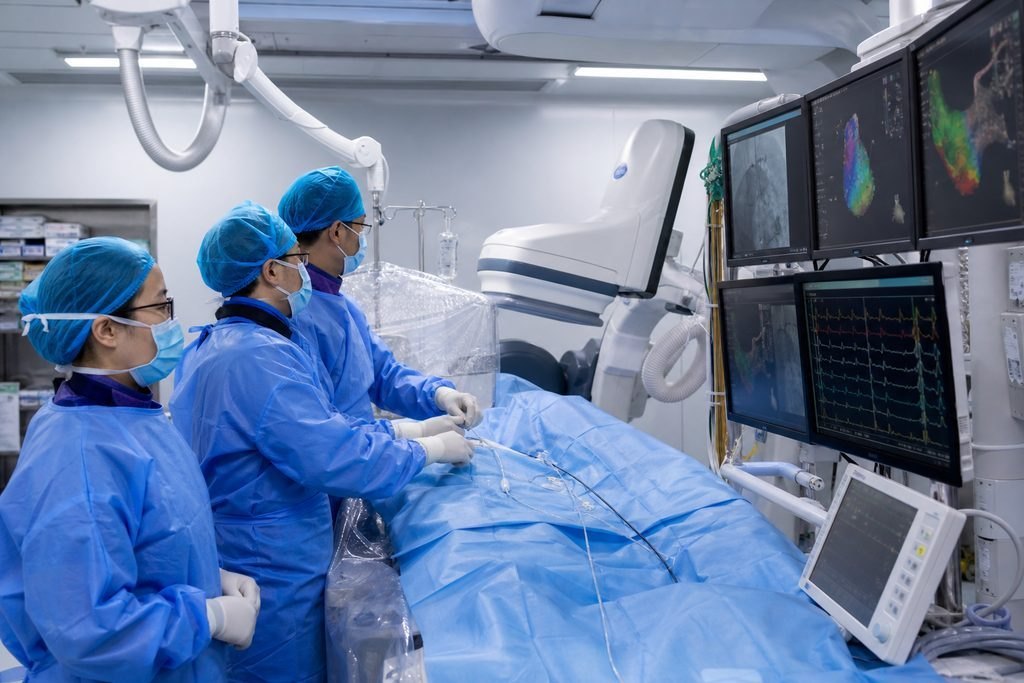
Why an ablation estimate is not a single fixed price
Catheter ablation treats selected abnormal heart rhythms by targeting the tissue responsible, and the approach depends on the rhythm problem. That clinical variability is the main reason a written estimate is a scope document rather than a guaranteed total. The hospital cannot know in advance exactly how much mapping, how many catheters, or how long a case will take until the electrophysiology team sees the actual rhythm behaviour.
For an overseas patient, the practical question is not whether the first number is high or low. It is which services that number covers, which services sit outside it, and what happens if the treating team needs something the estimate did not anticipate. Those three answers determine your real financial exposure far more than the headline figure.
Ask the named hospital, not a general enquiry line, for a written breakdown. A useful reply separates the professional fee, the facility or theatre charge, devices and consumables, imaging and monitoring, ward or intensive-care nights, medicines, and any follow-up consultation. If the hospital cannot itemise to that level, ask it to state in writing which categories are included and which are not.
Items that commonly sit outside an initial figure
The exact exclusions depend on the hospital and the individual case, so treat the following as questions to put to the provider rather than a fixed list. Pre-procedure work is a frequent boundary: blood tests, echocardiography, Holter or event monitoring, transoesophageal imaging, and anaesthetic assessment may be quoted separately from the ablation itself.
During the procedure, additional mapping or an extra catheter, a longer than expected theatre session, or conversion from one ablation technique to another can change the resource used. Post-procedure care is another boundary: an intensive-care or monitored bed, an extended ward stay, and repeat imaging are not always bundled into a single procedure price.
Follow-up is easy to leave out of the comparison. A review consultation, a repeat Holter or rhythm monitor, and any change to anticoagulation or rhythm medication may each be billed as separate clinical services. Ask the hospital how post-procedure reviews are scheduled, whether they can be done remotely or with your local cardiologist, and what the hospital charges for each.
Complications are the hardest item to price in advance. If a bleed, fluid collection, or vascular problem requires additional treatment, that care is billed according to what is actually done. Ask the hospital how it handles costs arising from an unforeseen event and whether any part of that is covered by the original estimate.
The rhythm records the electrophysiology team needs
Ablation planning starts with the rhythm itself, so the records that matter most are the ones that show it. Ask the electrophysiology team which specific recordings it wants: a 12-lead ECG during symptoms, a Holter or ambulatory monitor report, an event recorder or patch monitor download, and any prior electrophysiology study report. If you have a wearable or smartwatch tracing that captured an episode, ask whether it is useful as supporting information.
Send the original reports or device exports where possible, not only a summary letter. Include the date, the recording duration, and any interpretation already issued. If your rhythm has not been documented, say so clearly, because that changes what the team may recommend before any procedure is planned.
Also ask what the team needs to know about your current medicines, especially anticoagulants and rhythm-control drugs. Do not stop or change any medicine on your own; that decision belongs to the prescribing clinician. The purpose of sending this information is to let the treating team assess suitability, not to obtain a decision by email.
Separating hospital charges from coordination and travel costs
Hospital consultations, tests, treatment, medicines, and rooms are paid to the hospital or the relevant provider. Coordination services are separate from those third-party charges, and travel costs such as flights, accommodation, and local transport are separate again. When you compare figures, make sure you are comparing the same category, because a coordination fee and a hospital estimate are not interchangeable.
Ask each provider for its own written quote and do not assume one hospital's inclusions match another's. If you use a coordination service, ask what it does and does not cover, and confirm that hospital charges remain payable directly to the hospital. An initial enquiry is free and does not require buying a proxy consultation; a proxy consultation is optional and is not a prerequisite for every appointment or procedure.
For the ablation itself, the hospital decides suitability after reviewing your records. A records-based review can clarify the likely scope and the questions to ask, but it does not establish final acceptance, a guaranteed date, or a fixed total. Treat any pre-travel figure as provisional until the treating team has assessed you.
What to confirm before you commit
Before you accept an estimate, ask the named hospital to confirm in writing which of the following are included and which are billed separately: pre-procedure tests, the ablation procedure and theatre time, mapping and catheters, anaesthesia, ward or intensive-care nights, medicines, complications, and follow-up reviews. Ask how each additional item is authorised and who is contacted if the plan changes during the procedure.
Ask which rhythm records the electrophysiology team needs and how post-procedure reviews would be coordinated, including whether any can be done remotely. Confirm what the written quote covers, what it excludes, and how the hospital handles a change in clinical plan. If any answer is vague, ask for it in writing before you travel.
If you have worsening or acute symptoms such as severe breathlessness, chest pain, fainting, or a sustained fast rhythm, seek local urgent care rather than delaying for an overseas enquiry. An overseas planning process is not a route for emergency treatment.
A practical next step is to send a brief summary of your rhythm problem, your main question, and the records you already hold. The team can then tell you what is missing and which hospital or specialist route fits. You can start with the free initial case review, and you do not need to purchase a proxy consultation to ask a question.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.