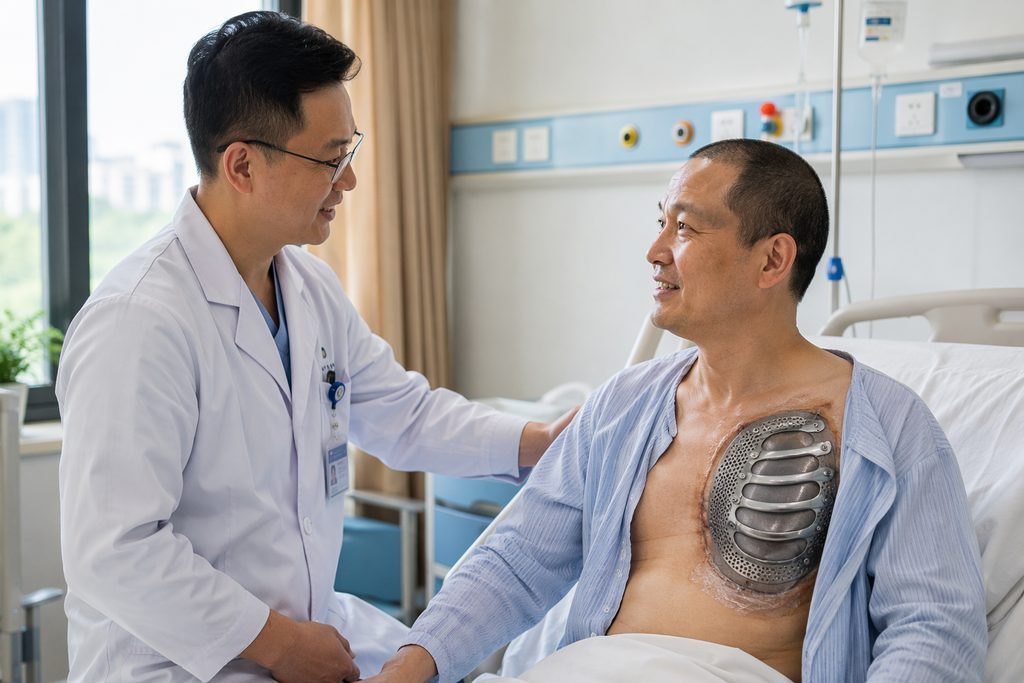
Why a short question list works better than a long one
A first in-person discussion about chest wall reconstruction covers a lot of ground: imaging, prior operations, pathology, general health and what the patient hopes to achieve. If you arrive with twenty questions, the conversation can drift into general explanation and leave the decisions you actually need unresolved. A short list of five to seven questions, ordered by importance, keeps the appointment focused on choices rather than background.
The practical test is whether each question changes what you do next. 'What is chest wall reconstruction?' does not change your next step. 'Is reconstruction appropriate for my situation, and what would the treating team need to confirm before deciding?' does. 'What are the risks?' is too broad to answer usefully in a first meeting; 'What risks should I understand before I decide, and who will explain them to me?' is answerable and points to a named person.
Write the list before you travel and keep it to one page. Put the two or three questions that would stop you proceeding at the top. If time runs short, those are the ones you must have answered. Everything else can be followed up in writing after the appointment, which is often a better route for detailed explanations anyway.
It also helps to decide in advance what you will not ask in this meeting. Questions about cost, scheduling and administrative steps are legitimate, but they can crowd out the clinical discussion if mixed together. Note them separately so you can raise them with the right person at the right time.
What to bring so the discussion can be specific
A chest wall reconstruction discussion is only as specific as the records in front of the clinician. Bring a clear index of what you have, not a folder of unsorted papers. The index should list each document by type, date and where it was produced, so the treating team can see what exists and what is missing without working through everything page by page.
Useful categories to list, if they exist in your case, include imaging reports and the images themselves where available, operation notes from previous surgery, pathology reports, discharge summaries, current medication lists and any recent general health assessments. This is not a universal mandatory list. It is a way of showing what you hold so the receiving team can tell you what they need. Ask them directly which of these they want to see and in what form.
Bring the records in a format the hospital can use. Ask in advance whether they prefer printed copies, a USB drive, a secure upload link or a combination. Do not assume one format suits every hospital. If you are sending records ahead of the visit, keep a copy with you so the in-person discussion does not depend on whether the file arrived.
Language matters here. If your records are not in Chinese, ask whether the hospital needs translated summaries and who is responsible for arranging them. Do not assume translation is provided or that it is your responsibility. Confirm it in writing before the appointment so neither side is surprised on the day.
Turning vague concerns into answerable questions
Most patients arrive with concerns rather than questions. 'I am worried about the operation' is honest but hard to answer. The work before the appointment is converting each concern into something a clinician can respond to, and then deciding who is best placed to answer it.
For example, a concern about whether surgery is the right path becomes: 'Based on the records I have brought, is reconstruction something your team would consider, and what further information would you need before deciding?' A concern about the plan becomes: 'If your team considers reconstruction appropriate, what would the written plan cover, and what would still be undecided at that point?' A concern about follow-up becomes: 'Who would be responsible for explaining the plan to me, and how would I raise questions afterwards?'
Notice that none of these questions asks the clinician to guarantee an outcome. They ask for a view, a scope and a named responsibility. That is what a first discussion can realistically provide. Questions that seek certainty about results, recovery or timing are better raised once the treating team has confirmed whether they will take the case, because until then any answer is provisional.
It also helps to separate questions for the surgeon from questions for other staff. Administrative questions about appointments, records and written estimates belong with the coordinating team. Clinical questions about suitability and risk belong with the treating clinician. Mixing them wastes the clinician's time and can leave the administrative points unresolved.
Confirming what the written plan and estimate cover
Before you commit to anything, ask for the scope in writing. A verbal summary in a busy clinic is easy to misremember, and the details matter. The request is simple: 'Please confirm in writing what the plan includes, what it excludes and what remains undecided.' This is a reasonable question at any stage and does not imply distrust.
For chest wall reconstruction, the written scope should let you see which parts of the proposed care are confirmed and which depend on further assessment. Ask the provider to state clearly what is included, what is not, and what has not yet been decided. If a component is undecided, ask who will decide it and when. Do not assume a particular charge is or is not part of a package; ask the named provider about its actual quote and what that quote covers.
Keep coordination fees and hospital medical fees separate in your own notes. They are different payments to different parties, and combining them in one figure makes it hard to see what you are being asked to pay for. If you are working with a coordination service, ask for its fees in writing and ask the hospital for its own estimate separately.
If you receive a preliminary reply before the in-person visit, treat it as a starting point rather than a final position. A records-based view can change once the clinician examines you and sees the original imaging. Ask what could change the plan and what would trigger a revised estimate. That question is more useful than asking for a single fixed number too early.
Naming who is responsible for each next step
A first discussion often ends with several open threads: additional records to send, a decision the team needs to make, an appointment to arrange, a written estimate to issue. If no one is named for each thread, they can stall quietly. Before you leave, ask who is responsible for each item and how you will know when it is done.
A simple way to do this is to read your list back at the end of the appointment and ask the clinician or coordinator to confirm the owner and the expected next contact for each open item. Write down the names and roles as they are given. If a name is not available, ask for the role instead, such as the coordinating office or the surgical secretary.
Ask how you should follow up and in what language. If you will be corresponding in English, confirm that the person handling your case can respond in English, or ask what interpretation arrangement is available. Do not assume this is settled; it is a practical point that affects whether your follow-up questions get answered.
Finally, ask what would make the team decide not to proceed. This is not a negative question. It tells you which findings or circumstances the team considers decisive, and it gives you a clearer sense of what the discussion is really about. A clinician who can explain their limits is easier to work with than one who only describes what they can do.
A practical next step after the appointment
After the in-person discussion, send a short written summary of what you understood and ask the team to correct anything you have recorded incorrectly. This creates a shared record and reduces the chance of a misunderstanding carrying into the next stage. Keep it factual: what was discussed, what was confirmed, what remains open and who owns each item.
If you are still at the enquiry stage, you can start with a brief summary of your situation rather than a complete medical archive. An initial enquiry is free and does not require buying a proxy consultation. The hospital decides whether reconstruction is suitable for your case, and a records-based review does not establish that decision on its own.
If you would like help organising records, preparing a question list or requesting a specialist appointment, ChinaSpecialistCare can support that as a non-clinical coordination service. We do not diagnose, decide suitability or promise that a hospital will accept a case. You can begin with a short summary through the enquiry form, email or WhatsApp, and share fuller records once the relevant next step is clear.
The goal of the first discussion is not to settle everything. It is to leave with a clear view of whether this team considers reconstruction appropriate, what the written plan covers, what remains undecided and who is responsible for the next step. If you can answer those four points after the appointment, the meeting has done its job.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.