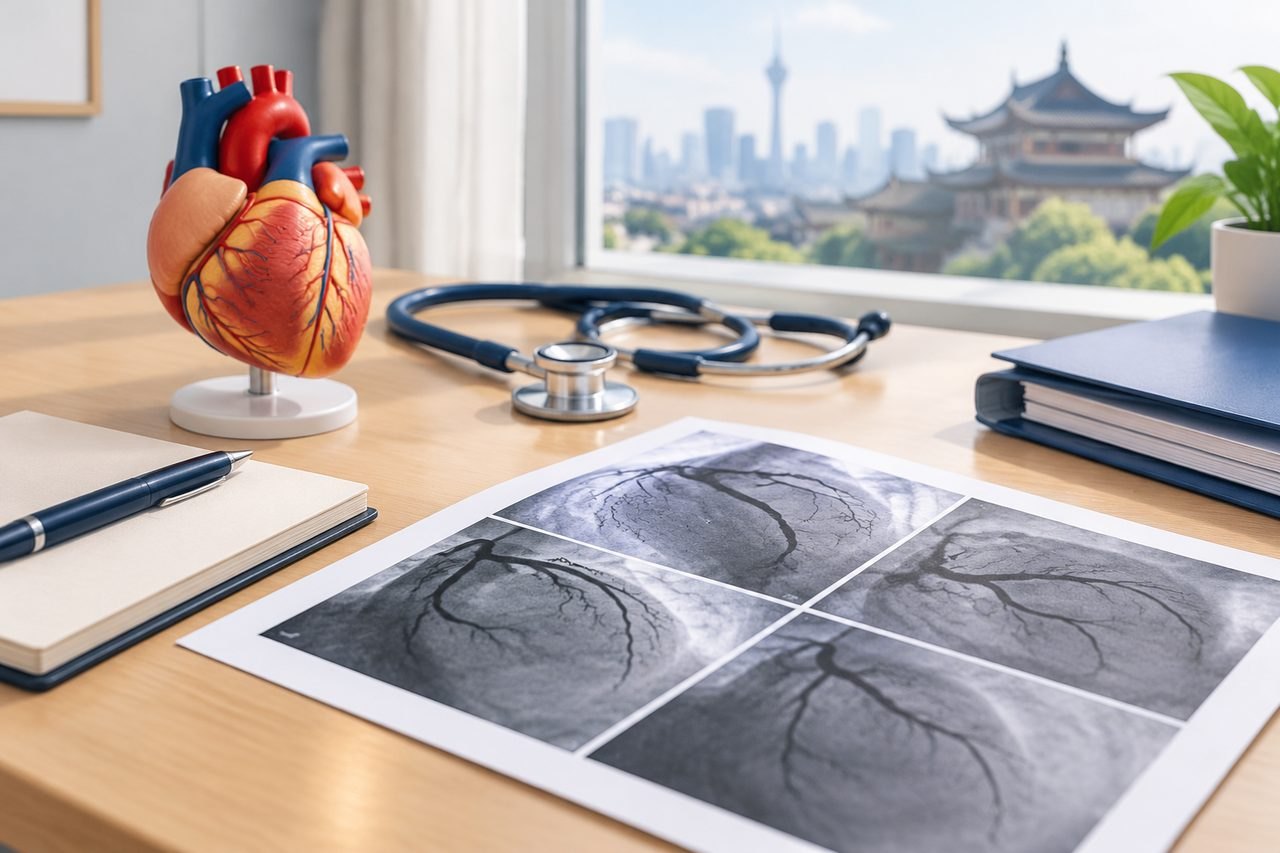
What a China cardiology review can and cannot answer
A records-based cardiology review in China is a clinical opinion, not a procedure booking. The specialist can examine your angiography images, symptom pattern and prior interventions, then explain what the anatomy suggests and which treatment categories are worth discussing. That opinion may differ from your current plan, and it may also confirm it.
What it cannot do is guarantee that a specific procedure will be performed, that a particular device is available, or that the hospital will accept you for treatment. Hospital acceptance is a separate decision made after the treating team reviews your records and, in many cases, examines you in person. A remote opinion is a starting point for that conversation, not a substitute for it.
The practical value depends on what you send. A written angiography report alone often leaves the specialist guessing about lesion severity, vessel size, calcification and whether a prior stent is patent. The images themselves — usually on a CD or DVD in DICOM format — carry the detail that changes the recommendation.
Why the angiography images matter more than the report
A coronary angiography report typically summarises findings in a few lines: which vessels are narrowed, by roughly what percentage, and whether stents were placed. That summary is useful for orientation but loses information a cardiologist needs when deciding between catheter-based treatment and bypass surgery.
The images show the actual anatomy. They reveal whether a narrowing is focal or diffuse, whether it sits at a branch point, how much calcium is present, and how the contrast flows through the vessel. These details influence whether a stent can be placed safely, whether a bypass graft would have a suitable target, and whether medical therapy alone is a reasonable option.
If you had a prior bypass, the review also needs the operative note and any subsequent angiography. Graft anatomy is different from native coronary anatomy, and a specialist assessing new symptoms needs to know which grafts were used and where they were attached.
Before sending anything, ask the hospital that performed the angiography how to obtain the image files. Many centres release them on request; some charge a small media fee. Send the images in their original format rather than photographs of a screen, which usually lose the resolution needed for assessment.
Matching symptoms to the affected territory
Symptoms are not a reliable map of which coronary artery is narrowed. Chest pain, breathlessness, jaw or arm discomfort and atypical presentations can all occur with disease in different vessels, and some people with significant narrowing report few symptoms at all. This is why the specialist needs both the image findings and a clear symptom history.
A useful symptom record covers what the discomfort feels like, where it starts and whether it spreads, what brings it on, how long it lasts, and what relieves it. Note whether the pattern has changed recently — new symptoms at rest, symptoms that wake you, or a lower level of exertion that now triggers discomfort are all clinically relevant.
Bring your current medication list with doses, including antiplatelet drugs, statins, beta-blockers, nitrates and any diabetes or blood pressure medicines. The treating cardiologist needs to know what you are already taking before discussing changes. Do not stop or adjust any medication on your own before a clinician advises you.
If your symptoms are worsening, occurring at rest, or accompanied by sweating, nausea or fainting, seek local emergency care rather than waiting for an overseas enquiry. A remote review is not appropriate for unstable symptoms.
Prior stents, prior bypass and what the options conversation covers
If you already have stents, the key questions are whether they remain open, whether new narrowings have developed in the same or different vessels, and whether the original stented segment is the source of current symptoms. Restenosis inside a stent and progression of disease elsewhere are different problems with different management.
If you have had bypass surgery, the review needs to consider graft function alongside native vessel disease. Coronary bypass surgery creates routes around narrowed coronary arteries to improve blood supply to heart muscle. Whether a further catheter-based procedure or a repeat operation is appropriate depends on the graft anatomy, the target vessels and your overall clinical picture.
The specialist may discuss medical therapy optimisation, catheter-based treatment such as angioplasty with or without stenting, or surgical revascularisation. Each has its own suitability criteria, and the choice is not simply a matter of preference. Ask the treating team to explain why a particular option is or is not recommended in your case, and what the alternatives are.
A multidisciplinary review may be useful when the case is complex — for example, when prior bypass, multiple stents and diabetes are all present. This is a records-based discussion between specialties, and the scope and fee are agreed before it proceeds.
Preparing records for a China review without over-sending
Start with a short summary: your main question, the date of your most recent angiography, whether you have had stents or bypass, and your current symptoms. This helps the coordination team identify what is missing before you send a large file.
The core records for this review are the angiography image files, the written angiography report, any prior operative notes for bypass or stent placement, a current medication list, and recent blood tests including kidney function and cholesterol. If you have had an echocardiogram or stress test, include those reports as well.
You do not need to send your entire medical history at the first contact. Passport numbers, payment details and complete archives are not required to begin. After the initial enquiry, the team will explain how to share records securely.
If a record is missing, say so rather than leaving it out silently. The specialist can often proceed with what is available while noting the limitation, or may ask for a specific additional document. Do not arrange new tests on your own before the treating clinician advises what is needed.
What to confirm before committing to travel or treatment
Before travelling, ask the hospital or coordinating team to confirm in writing what the review covers, who will see the records, and whether an in-person consultation is expected. A confirmed appointment is different from a provisional clinical stage, and you should know which one you have.
Ask how the hospital's estimate is structured: what is included, what is excluded, and what remains undecided until after examination. Hospital fees, coordination fees and travel costs are separate, and the hospital's written quote is the authoritative document for its charges.
Ask what the treating team needs from you before a decision can be made — additional imaging, blood tests, a cardiology examination in person, or a multidisciplinary discussion. If the answer is unclear, ask again until you have a specific list.
Finally, ask what the follow-up plan would be after any procedure, including who would review you and how communication would work if you return home. The treating hospital decides suitability and treatment; the coordination team can help arrange appointments and interpretation but does not make clinical decisions.
A free initial enquiry is the appropriate first step. You do not need to purchase a proxy consultation to ask whether your records are suitable for review. Send a brief summary of your angiography date, prior interventions and current symptoms, and the team will explain the relevant next step.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.