
CABG creates new routes around narrowed coronary arteries
A surgeon connects healthy blood vessels beyond significant coronary blockages so oxygen-rich blood can reach heart muscle. One or several grafts may be needed.
The decision is not based on the number of blockages alone. Their location and complexity, diabetes, symptoms, pumping function, previous stents and the expected durability of surgery versus PCI all matter.
When both surgery and PCI are technically possible, ask for a shared review of anatomy, operative risk, medication needs and long-term durability.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about coronary bypass surgery.
- Left main or complex multivessel coronary disease.
- Persistent angina despite appropriate medical treatment.
- Coronary disease with diabetes or reduced heart function where surgery may offer an advantage.
- Failed or unsuitable catheter-based treatment after multidisciplinary review.
What the specialist team must confirm
The team reviews coronary angiography, echocardiography, symptoms, previous PCI, kidney and lung function, frailty, stroke and bleeding risk, conduit availability and medicines including antiplatelet or anticoagulant therapy.
Key points for this treatment
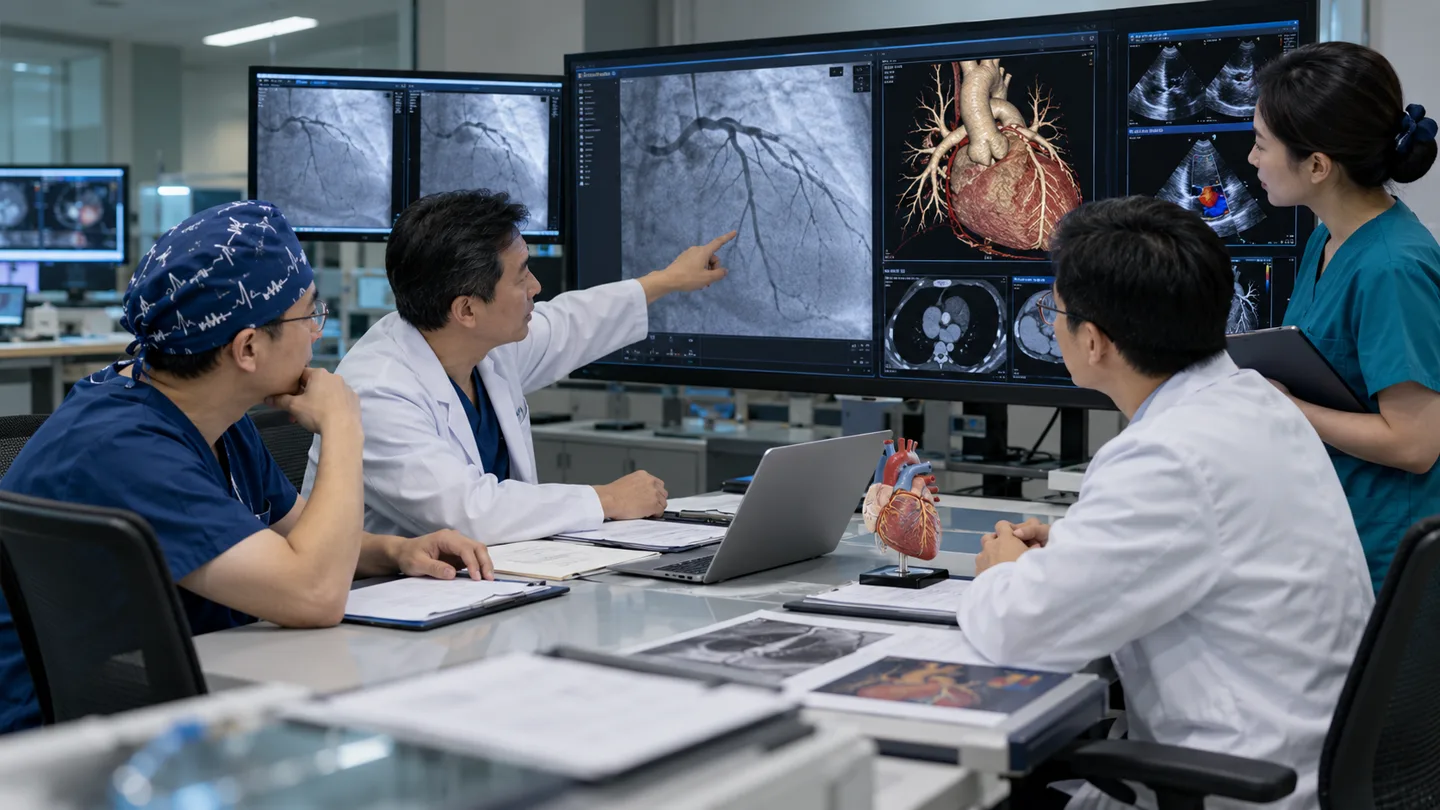
From angiography to graft strategy
The heart team first confirms that the expected benefit of revascularization is greater than the operative and recovery burden.
Recovery protects the chest and the grafts
Early care focuses on breathing, rhythm, pain control, wound care and safe mobilisation. The pace depends on complications and preoperative fitness.
Long-term benefit still requires antiplatelet and other prescribed medicines, cholesterol and blood-pressure management, smoking cessation and cardiac rehabilitation.

Risks, limits and realistic expectations
CABG is major surgery. Risks include bleeding, infection, stroke, heart attack, rhythm disturbance, kidney or lung complications, graft failure and death. Surgery treats obstructed blood flow but does not remove the underlying atherosclerotic disease.
Ongoing chest pain, severe breathlessness, fainting or suspected heart attack needs emergency local care; do not wait for overseas review.