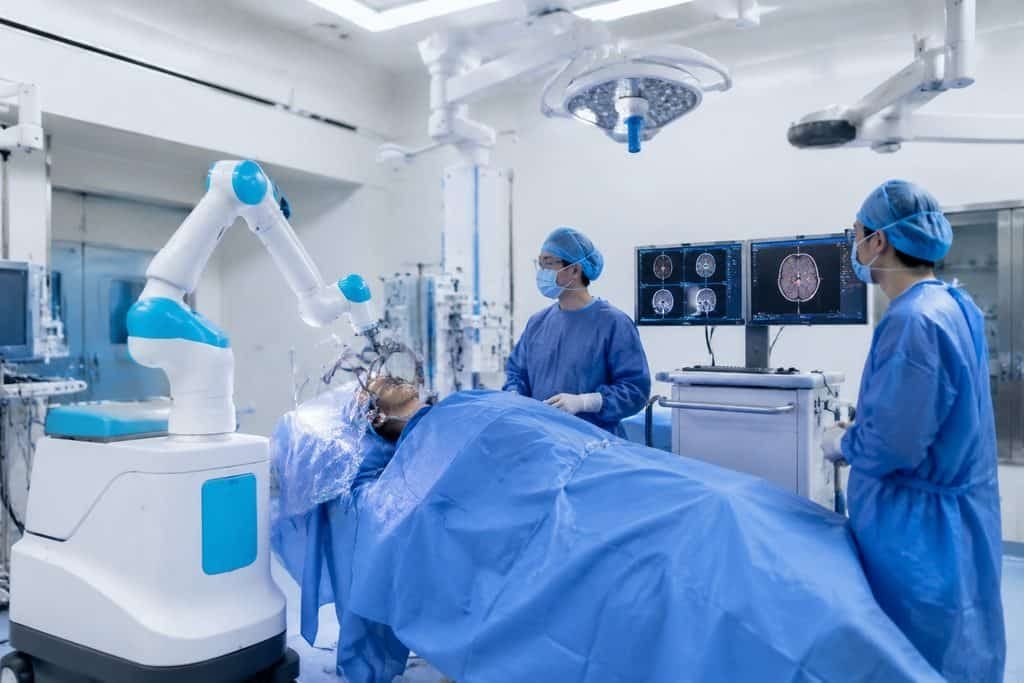
What records can answer before anyone travels
A records-based review can clarify what is already known and what is missing. It can identify whether the diagnosis of epilepsy is well supported, which antiseizure medicines have been tried and at what doses, whether seizures have been classified, and whether EEG, MRI and other investigations are available in a usable format. It can also flag inconsistencies, such as a medicine list that does not match the seizure diary, or an EEG report without the original traces.
This kind of review is a starting point, not a final answer. It does not confirm drug resistance, because that judgement depends on how medicines were taken, whether doses were adequate, and whether seizures continued despite appropriate treatment. It also cannot decide whether surgery is suitable. Those conclusions belong to the treating clinicians after they have the relevant information and, in many cases, after they have seen the patient.
For an overseas enquiry, the practical value is narrowing the question. Instead of asking a hospital to accept a patient for epilepsy surgery, the first request can ask whether the records are sufficient for an initial opinion, what is missing, and what would need to be done in person. That keeps the enquiry honest and avoids implying that a remote review can replace clinical assessment.
Questions that usually need the patient in the room
Some questions depend on direct observation, examination or supervised testing. Whether a seizure type is focal or generalised can change the treatment path, and that distinction is not always clear from a written report. A clinician may need to see the events, review video recordings, or arrange EEG monitoring that captures seizures. Examination can also reveal neurological findings that influence the assessment.
Medication history is another area where records alone can mislead. A patient may report having tried several medicines, but the key details are the exact drug, the dose, how long it was taken, whether it was taken consistently, and why it was stopped. Those details are often clarified in conversation, with the patient or a family member who witnessed the seizures and the treatment. A remote reviewer can list the questions, but the treating team needs to confirm the answers.
Cognitive and memory concerns, mood, and the impact of seizures on daily life also need careful discussion. These factors can affect whether a person is considered for an epilepsy surgery assessment and what support is needed. They are difficult to assess from a file alone. The same applies to consent and expectations: a patient needs to understand what an assessment involves, what it may show, and what it does not guarantee.
Why drug resistance is not a label a file can carry
Drug-resistant epilepsy is not simply a matter of counting medicines. The relevant question is whether seizures continue despite appropriate trials of antiseizure medicines. That requires knowing whether the diagnosis is correct, whether the medicines were appropriate for the seizure type, whether doses were adequate, and whether the patient was able to take them as prescribed. A records review can organise this information, but the treating clinician must interpret it.
This matters for overseas planning because a patient may arrive believing they are a candidate for surgery, when the actual next step is to confirm the diagnosis or adjust treatment. The reverse can also happen: a patient may have been told nothing more can be done, when a structured assessment could identify other options. Neither situation can be resolved by a remote opinion alone. The honest position is that the assessment determines the answer.
Epilepsy surgery can be considered for selected people whose seizures are not controlled by medicines, and assessment examines potential benefits and risks. That is the frame. It does not mean surgery will follow an assessment, and it does not mean a remote review can establish eligibility. The treating team decides whether assessment is appropriate and what it involves.
What a multidisciplinary evaluation adds, and what it cannot promise
A multidisciplinary evaluation brings together the specialties needed to interpret the different parts of the case, such as neurology, neuroradiology, neurophysiology, neuropsychology and neurosurgery. The value is that the same information is considered from several angles, and disagreements or gaps are identified. For a complex case, this can be more useful than a single opinion.
What it cannot do is guarantee an outcome. It cannot promise that surgery will be offered, that seizures will stop, or that medicines can be reduced or stopped. Those are clinical decisions that depend on the individual findings and on the treating team's judgement. A multidisciplinary review can also conclude that more information is needed, or that a different treatment route is more appropriate.
For an overseas patient, the practical question is how such a review is arranged and what it requires. Does it need the patient present? Are video EEG or other tests required first? Who coordinates the different appointments? These are questions for the hospital, not assumptions to make in advance. The answers can vary by institution and by case.
How to prepare records so the in-person visit is useful
The goal of preparation is not to send everything, but to send what the treating team needs to decide the next step. A clear summary of the seizure history, a current medicine list with doses and dates, and the original EEG and MRI reports with images where possible are more useful than a large unorganised file. If video recordings of seizures exist, ask whether the hospital wants them and in what format.
It also helps to write down the specific questions the patient wants answered. Examples include: Is the diagnosis confirmed? Have appropriate medicines been tried? Is an epilepsy surgery assessment appropriate? What tests would be needed, and do they require an inpatient stay? What are the alternatives if surgery is not suitable? These questions make the consultation more efficient and reduce the risk of leaving with unresolved uncertainty.
Language and interpretation arrangements should be confirmed before the visit. Medical discussions about seizures, medicines and possible surgery need accurate communication. Ask the hospital or coordinating service what interpretation is available and whether it is provided by clinical staff or a separate service. Do not assume that English is available at every step.
- Seizure diary with dates, descriptions and possible triggers
- Current and previous antiseizure medicines with doses and dates
- Original EEG reports and traces, not only summaries
- MRI or CT reports and images in a usable digital format
- Video recordings of seizures, if available and requested
- A written list of the patient's main questions
What to confirm with the hospital before travelling
Before making travel plans, confirm what the hospital can actually offer at the first visit. Ask whether the initial appointment is a consultation, a review of records, or the start of an inpatient assessment. Ask what tests are likely to be arranged, whether they require admission, and how long the patient should plan to stay in the area. These are practical questions, and the answers depend on the individual case and the hospital's arrangements.
It is also reasonable to ask who will review the case and how the different specialties communicate. For a complex epilepsy case, the patient should know whether a multidisciplinary discussion is part of the process and whether it happens before or after the in-person visit. If the hospital cannot answer these questions in advance, that is useful information for planning.
Finally, keep the enquiry focused. An initial enquiry can be a brief summary of the diagnosis, the main question, and the records available. It does not require buying a proxy consultation, and it does not commit the patient to treatment. The hospital decides suitability. If the records are incomplete, the next step may simply be to obtain the missing reports or to ask the treating team what they need.
ChinaSpecialistCare can help with non-clinical coordination, such as requesting a specialist appointment or arranging interpretation, when that is relevant. Clinical decisions, including whether an epilepsy surgery assessment is appropriate, remain with the treating hospital and licensed clinicians.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.