Start with the duct question, not the procedure name
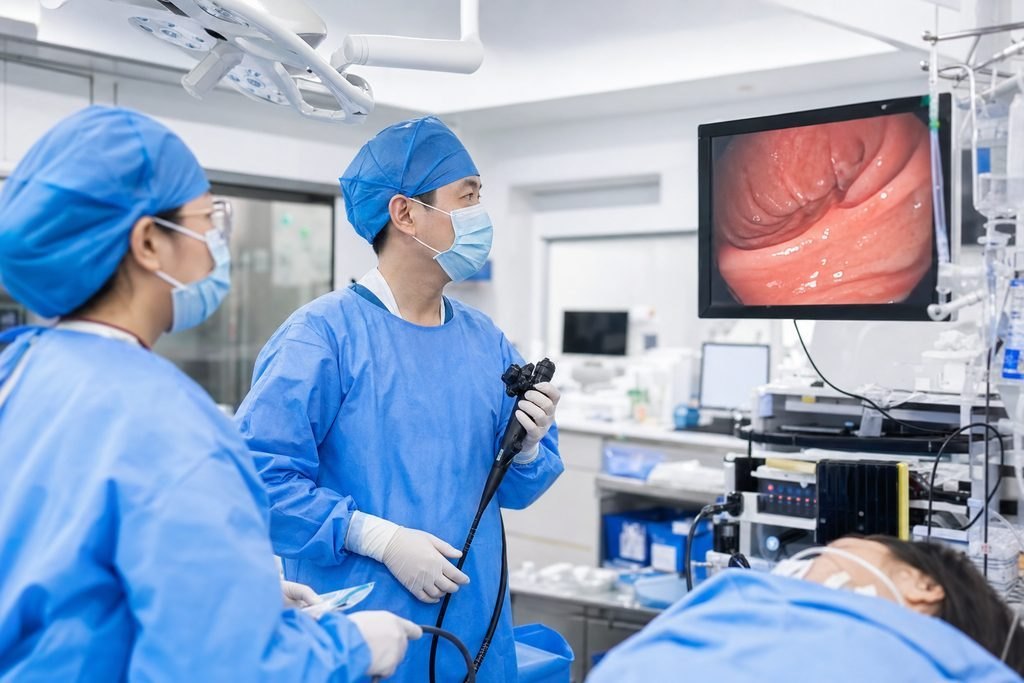
ERCP combines endoscopy and X-rays to examine and treat bile or pancreatic duct problems. That single sentence already tells you why the first conversation should begin with the duct, not with the acronym. The specialist needs to understand what is wrong with the duct, what the imaging shows and what the intended goal is before anyone can discuss whether ERCP is the right route for you.
Many overseas patients arrive at a first appointment having been told only that they need ERCP. That is not enough to have a useful discussion. Ask the clinician to explain, in plain terms, what the duct problem is, where it is located and what the proposed ERCP is meant to achieve. If the answer is vague, that is your signal to ask for clarification rather than to assume the plan is settled.
Bring the actual imaging reports, not just a summary. If you have had an ultrasound, CT, MRI or MRCP, the written report and the images themselves help the specialist understand the anatomy. Ask whether the hospital wants the original images on disc or whether a secure upload is acceptable. This is a practical question to confirm with the specific hospital, because document-handling arrangements differ between providers.
Ask whether the proposed ERCP is diagnostic, therapeutic or both
ERCP can be used to look at the ducts, to treat a problem, or to do both in the same session. The distinction matters for your preparation and for what you should expect afterwards. A purely diagnostic ERCP raises a different set of questions from one that is planned to remove a stone or place a stent.
Ask directly: is this ERCP intended to treat something, or mainly to get more information? If treatment is planned, what exactly is the target? Stone removal, stent placement, dilation of a narrowing and tissue sampling are different interventions with different implications. You do not need to memorise the technical names. You need to understand which one is being proposed for you and why.
If the clinician mentions more than one possible intervention, ask which is the primary plan and which is the fallback. A fallback is not a failure of planning; it is a normal part of procedural medicine. Knowing it exists helps you ask better follow-up questions and avoids surprise if the session ends differently from what you imagined.
Clarify whether later procedures are expected
Some ERCP plans involve a single session. Others involve a planned sequence, for example an initial stent placement followed by a later procedure to remove or exchange it. This is one of the most useful things to clarify at the first in-person discussion, because it affects how you think about your time in China and what you need to arrange at home.
Ask whether a follow-up ERCP is expected, and if so, what it would involve. Do not ask for a fixed date or a guaranteed interval; those depend on the clinical situation and the treating team's judgement. Instead, ask what the general plan looks like and what would determine the timing. If the answer is that follow-up depends on how you respond, that is a legitimate clinical answer, and you can ask what signs or results would trigger the next step.
If you are travelling from another country, tell the clinician early. The treating team needs to know that you may not be able to return at short notice. This does not change the medical plan, but it may change how the team explains the follow-up schedule and what they recommend you arrange before you leave. The hospital decides what is clinically appropriate; your job is to make your circumstances clear.
Prepare a short written question list
A first specialist appointment can move quickly, especially with interpretation. A written list keeps you focused and ensures you do not leave without asking the questions that matter most to you. Keep it short. Five to eight questions is a workable number for a productive discussion, and it is better to leave with clear answers to a few questions than vague answers to many.
Write your questions in your own language and have them translated if needed. Give a copy to the interpreter or clinician at the start. This is more reliable than trying to remember everything in the moment. It also signals that you are prepared and that you want a clear explanation, not a rushed decision.
Your list might include: What is the duct problem? Is ERCP the recommended approach, and what are the alternatives? Does the plan involve stone treatment, stenting or another intervention? Is a follow-up procedure expected? What records or imaging does the hospital still need? What should I arrange before I leave China? These are decision questions, not requests for a diagnosis. The clinician will answer within the limits of what your records show.
If you are unsure how to phrase a question, start with what you already know. For example: I have been told there is a blockage in my bile duct. I want to understand whether ERCP is the right way to treat it, and what would happen if we did not do it. That kind of opening gives the specialist something concrete to respond to and makes it easier for you to follow the answer.
It also helps to ask what the specialist would want to know if the situation were reversed. What information would change the recommendation? What would make the team pause or choose a different approach? These questions surface the clinical reasoning without asking for a guarantee. They also give you a sense of how much uncertainty is built into the plan, which is useful when you are deciding how to organise your time and travel.
Finally, ask how you will receive the answers. Will the hospital provide a written summary? Can the interpreter explain the plan again after the appointment? If you are travelling with a companion, decide in advance who will take notes. A short written record of what was discussed is more useful than trying to reconstruct the conversation later, especially if you need to share it with a clinician at home.
Understand what the first discussion can and cannot settle
A first in-person discussion is a clinical assessment, not a final commitment. The specialist can review your history, examine you if appropriate and explain the likely options. What the discussion cannot do is guarantee that ERCP will proceed, that a particular intervention will be used or that the outcome will follow a specific course. Those decisions depend on the findings at the time and the treating team's judgement.
This is not a reason to avoid the appointment. It is a reason to ask better questions. Instead of asking for a guarantee, ask what the plan is, what could change it and what you should watch for afterwards. Ask who to contact if you have a concern after the procedure. Ask what written information the hospital provides about follow-up and when you should seek urgent care.
If you have been told by another provider that ERCP is definitely needed, you can still ask the China specialist to explain the reasoning. A second opinion is a normal part of medical decision-making. The specialist may agree, disagree or want more information. All three are useful outcomes because they clarify your next step.
Practical preparation and your next step
Before the appointment, gather your relevant records: imaging reports and images, blood test results, endoscopy reports if you have had one, a list of your current medicines and any allergy information. Do not send a complete medical archive in your first message. A brief summary is enough to start, and the hospital or coordination team can tell you what else is needed.
If you need help with interpretation, appointment registration or organising your records for a specialist review, ChinaSpecialistCare can discuss those coordination arrangements. The free initial case review checks the available diagnosis, records and your main question, identifies missing information and suggests a relevant next step. It is not a diagnosis or a promise of acceptance. A proxy consultation is optional and not a prerequisite for an appointment.
Your next step is simple: write your five to eight questions, gather the imaging reports and a current medicine list, and send a brief summary through the enquiry form. The hospital decides suitability after reviewing your records. You do not need to buy a proxy consultation to start the conversation.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.