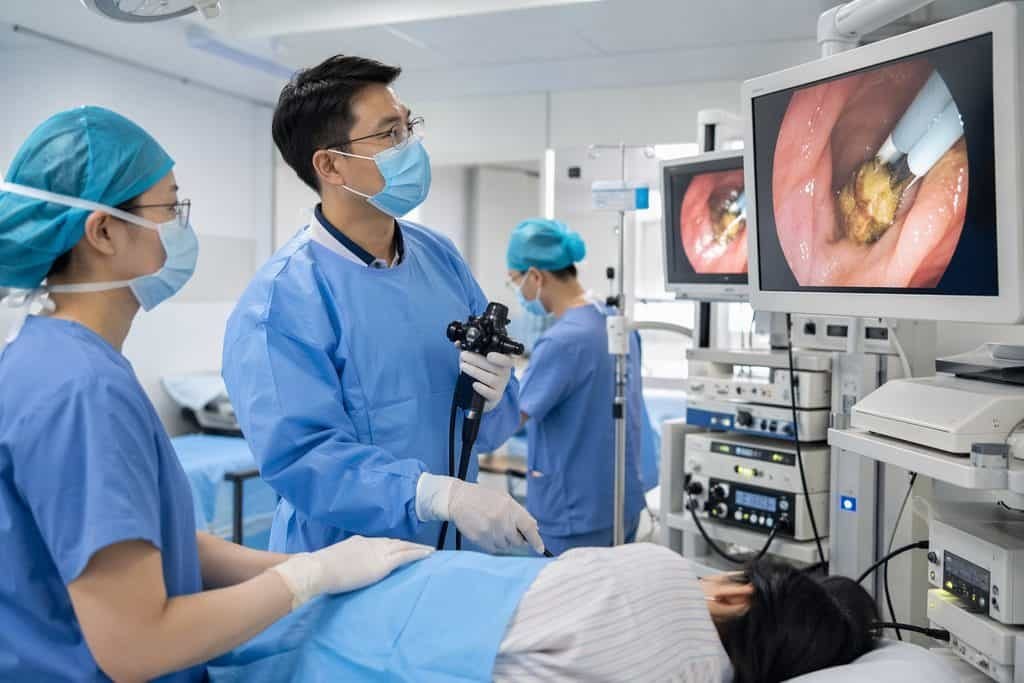
Why a Verbal Explanation Is Not Enough After ERCP
ERCP combines endoscopy and X-rays to examine and treat bile or pancreatic duct problems. That means one procedure can produce several different outcomes: a duct may be imaged and found clear, a stone may be removed, a narrowing may be stented, or the team may decide that a further procedure is needed. Each of those outcomes implies a different follow-up question, and the details matter most after you have left the hospital and are trying to explain your situation to another clinician.
A verbal summary given during recovery, when you may still be sedated or uncomfortable, is easy to misremember. A written plan gives you something to reread at home, to share with your local doctor, and to check against what actually happens next. It also reduces the risk that a follow-up appointment or stent review is missed simply because no one wrote down what was expected.
This guide is about how to obtain and record that plan. It is not a statement that ERCP is the right treatment for you, that a particular hospital will accept your case, or that follow-up can be arranged in one trip. Those are clinical and administrative decisions for the treating team.
What the Written Plan Should Cover
The most useful written plan is specific to your procedure, not a generic discharge sheet. Before you leave, ask the team to record the findings and the intended next steps in plain language you can act on.
Start with what the ERCP actually did. Ask whether the procedure involved stone treatment, stent placement, dilation, tissue sampling, or another intervention, and whether the duct problem was fully addressed or only partly managed. If a stent was placed, ask what type it is and what the plan is for it. Do not assume that every stent is removed on the same schedule or that removal is always needed; the treating clinician decides that based on your duct and your procedure.
Then ask about expected later procedures. Some patients need a repeat ERCP to remove or exchange a stent, to treat a remaining stone, or to reassess a narrowing. Others need no further endoscopic procedure and are followed with blood tests, imaging, or a clinic visit. The plan should say which of these applies to you, or state clearly that the next step depends on how you recover.
Finally, ask what warning signs should prompt you to seek care sooner rather than waiting for a scheduled review. The team should tell you which symptoms are expected after ERCP and which are not, and where to go if they occur. Write down the answer in the words the clinician uses.
- What the ERCP found in the bile or pancreatic duct.
- What was done during the procedure, including any stent.
- Whether a repeat ERCP or another procedure is expected, and why.
- Which symptoms should prompt urgent contact rather than waiting.
- Which clinician or department owns the follow-up decision.
Records, Images and Reports You Should Ask For
A follow-up plan is only useful if it travels with the underlying records. Ask what documentation you will receive and in what language. Typical items include the ERCP procedure report, the endoscopy and fluoroscopy images, any pathology result from tissue samples, and a discharge summary that states the diagnosis and the plan.
Ask specifically whether the images are provided as a disc, a download link, or a printed set, and whether the report is in English or Chinese. If you will need the records reviewed elsewhere, ask whether an English-language summary can be prepared and whether there is a fee for copies. These are administrative questions for the hospital, and the answers vary by institution, so confirm them rather than assuming.
Keep your own copy of everything. If you are travelling home, carry the images and reports with you rather than checking them into luggage, and keep a digital backup. When you hand records to a new clinician, keep a list of what you gave and when.
If some records are not ready before you leave, ask how and when they will be sent, and who will send them. Get a named contact and a written note of what is still outstanding.
Who Is Responsible for Each Part of Follow-Up
Follow-up after ERCP often involves more than one person: the endoscopist who performed the procedure, the ward or clinic team that discharges you, and your own doctor at home. The written plan should make clear who is responsible for what, so that a question does not fall between them.
Ask which clinician or department will review the stent or the duct problem, and how that review is triggered. Is it a scheduled appointment, a call from the hospital, or something you must arrange yourself? If you are returning home, ask whether the hospital can communicate with your local doctor and in what form.
Ask who you should contact with a non-urgent question after discharge, and through which channel. A phone number, an email address, or a clinic contact is more useful than a general hospital switchboard. If the answer is that you should contact your local doctor first, write that down too.
If you are considering follow-up in China, ask whether the same team will provide it and what would be required to arrange it. Do not assume that a follow-up appointment is guaranteed or that it can be fitted into a short trip. Confirm the practical arrangements with the hospital before you rely on them.
Questions to Ask Before Sedation, Not After
Some of the most important follow-up questions are easier to ask before the procedure, while you are alert and the team is planning. Consent discussions are a good moment to raise them.
Ask whether the proposed ERCP is intended mainly to diagnose or mainly to treat, and whether stone treatment, stenting, or another intervention is anticipated. Ask whether later procedures are likely and, if so, what would determine the timing. Ask what the alternatives are if ERCP is not performed or does not resolve the problem.
Ask what the team needs from you before the procedure, such as current medication information or previous imaging, and what you should expect afterwards. If you take medicines that affect bleeding or sedation, tell the team and follow their instructions; do not change any medicine on your own.
Ask how the plan will be documented and who will give you the written version. If you need an interpreter, ask whether one can be present for the consent discussion and the discharge explanation, because a written plan is only useful if you understand it.
Turning the Plan Into a Practical Handover
Once you have the written plan, make it usable. Summarise it in one page: the date of the ERCP, what was found, what was done, whether a stent is in place, what procedure or review is expected next, and who to contact. Attach the procedure report and discharge summary behind it.
Give a copy to your local doctor and keep one with you. If a follow-up procedure is expected, ask the hospital to confirm the appointment or the process for arranging it in writing, and note any preparation instructions the team gives you. Do not invent a schedule or assume a date that was not confirmed.
If you are planning further care in China, an initial enquiry can start with a short summary of your situation and your main question. ChinaSpecialistCare's team can check the available diagnosis and records, identify what is missing, and suggest a relevant next step; this is not a diagnosis or a promise of acceptance. Hospital consultations, tests, treatment, medicines and rooms are paid to the hospital or relevant provider, and coordination fees are separate. The hospital decides suitability and the clinical plan.
A useful next step is to ask the treating team for the written follow-up plan before discharge, then send a brief summary of your ERCP records and your specific follow-up question through the enquiry form, email, or WhatsApp. Keep the initial message short; more detailed records can be shared after first contact.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.