Why the intended goal changes the ERCP decision
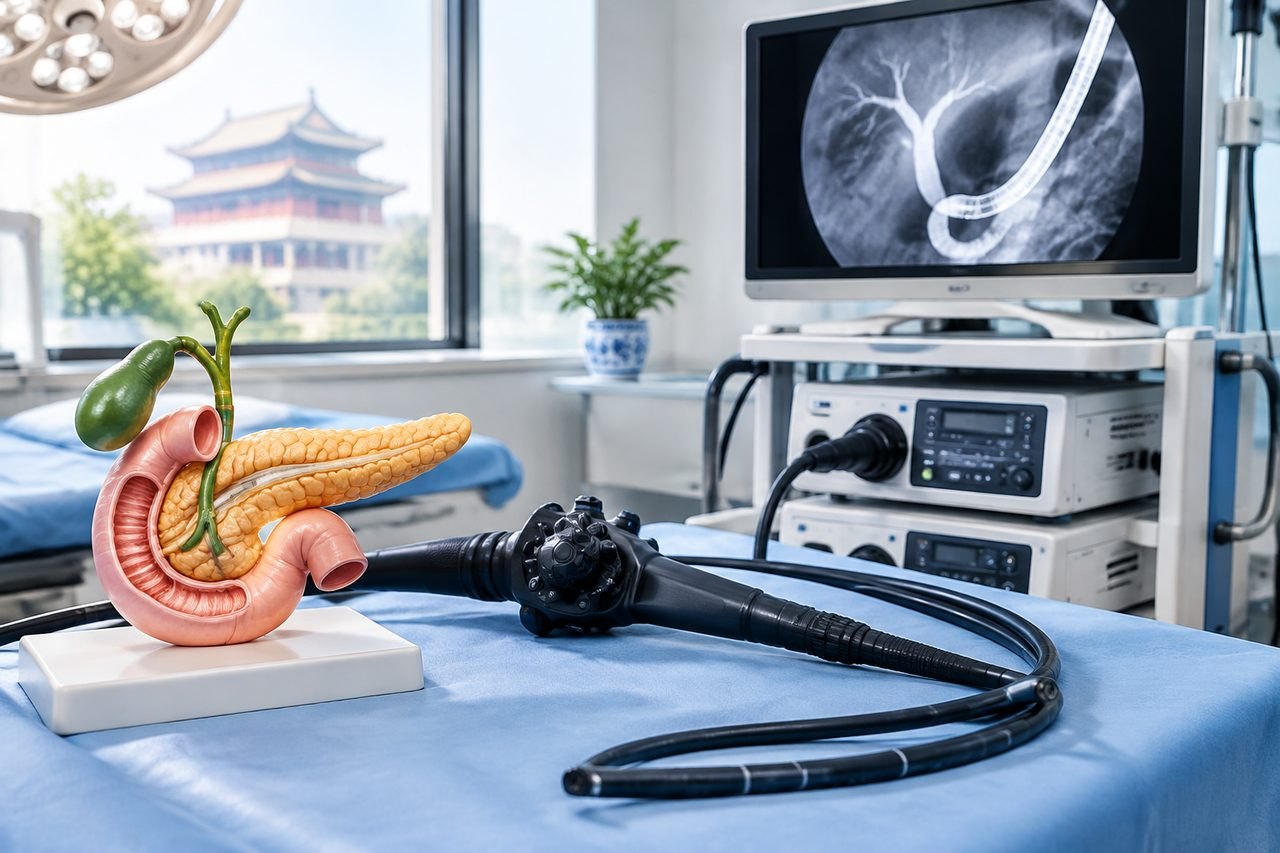
Patients often ask whether ERCP is available in China. A more useful question is what the procedure is meant to achieve in your case. ERCP combines an endoscope with X-ray imaging to examine and treat bile or pancreatic duct problems. That definition covers a wide range of possible intentions. The same procedure name can be proposed to look for a cause of symptoms, to relieve a known obstruction, to place or exchange a stent, to remove a stone, or to manage a leak or stricture.
The intended goal determines what the clinician needs to see before the procedure, what alternatives should be discussed, and what follow-up is planned. If the goal is diagnostic, the team should explain why other imaging or tests have not answered the question. If the goal is therapeutic, the team should explain what specific problem is being treated and what success would look like. If the goal is both, the consent discussion should cover both possibilities.
This matters for overseas patients because the decision to travel is often made before the clinical goal is clearly stated. A hospital may accept a case for ERCP, but acceptance does not by itself confirm that the procedure is the right next step for your condition. The treating clinician decides suitability after reviewing your records and examining you where needed.
Diagnostic ERCP versus therapeutic ERCP
Diagnostic ERCP is used when the team needs detailed information about the bile or pancreatic ducts that other tests have not provided. Therapeutic ERCP is used when a duct problem has already been identified and the plan is to treat it through the endoscope. In practice, many procedures have both a diagnostic and a therapeutic element, but the balance should be clear before you consent.
Ask the clinician to state the primary goal in one sentence. For example: to remove a bile duct stone that is causing obstruction; to place a stent across a narrowing; to investigate a suspected duct injury; or to treat a pancreatic duct leak. If the answer is vague, ask what finding would change the plan during the procedure and what would happen if the intended goal cannot be achieved.
A diagnostic-only ERCP may be proposed when non-invasive imaging is inconclusive. In that situation, ask whether another test could provide the same information with fewer risks. A therapeutic ERCP may be proposed when a problem is already known. In that situation, ask what the expected benefit is, what the alternatives are, and what recovery and follow-up the treating team advises for your individual case.
What the treating team needs to confirm suitability
ERCP is not a routine screening test. It carries risks, and the decision to perform it depends on your history, imaging, laboratory results and current symptoms. Before a clinician in China can judge whether ERCP is appropriate, they need a clear picture of the problem and the reason it is being considered.
Relevant records may include recent imaging reports such as ultrasound, CT or MRI/MRCP, blood test results, endoscopy reports, operative notes from previous biliary or pancreatic surgery, and a list of current medicines with doses. If you have had a previous ERCP, the report and any stent details are important. If you have a known allergy, bleeding disorder or significant heart or lung condition, that information belongs in the summary.
You do not need to send a complete archive at the first contact. A short summary with the main diagnosis or question, key imaging findings and the specific decision you are facing is enough to start. The team can then tell you what additional documents or clarifications are needed. Missing records do not mean a clinician must guess; they mean the review has limits, and those limits should be explained to you.
Questions that change the next step
The answers to a few focused questions will tell you whether to proceed with planning, seek more information, or reconsider the procedure. Ask the treating team directly and ask for the answers in writing where possible.
First, what is the intended goal of ERCP in my case, and how will you know if it has been achieved? Second, what alternatives have been considered, and why is ERCP preferred over them? Third, what are the main risks for me personally, given my history? Fourth, what follow-up is planned after the procedure, including whether a stent is involved and who will manage it? Fifth, what would happen if the procedure is not done now?
These questions are not a test of the clinician. They are the normal content of a consent discussion. If the goal is unclear, or if the alternatives have not been explained, that is a reason to pause and ask for clarification before committing to travel. The hospital decides suitability; your role is to make sure you understand what is being proposed and why.
Planning example: two patients, same procedure name
Consider two overseas patients both told they may need ERCP. The first has a known bile duct stone causing obstruction and jaundice. The intended goal is therapeutic: remove the stone and restore bile flow. The records needed are imaging confirming the stone, blood tests showing the effect on the liver, and a medication and allergy history. The consent discussion should cover the risk of pancreatitis, bleeding, infection and the possibility that the stone cannot be removed in one session.
The second patient has unexplained upper abdominal pain and inconclusive imaging. The intended goal is diagnostic: determine whether a duct problem is present. The records needed include the imaging already done, the reason it was inconclusive, and the symptoms being investigated. The consent discussion should cover why ERCP is preferred over further non-invasive imaging, and what the team will do if the findings are normal.
Same procedure name, different decisions. For the first patient, the main planning question is whether the treating team can achieve the therapeutic goal and what follow-up is needed. For the second, the main question is whether ERCP is the right diagnostic step at all. Clarifying which situation you are in prevents you from preparing for the wrong journey.
Practical preparation and boundaries
Once the intended goal is clear, practical preparation follows. Ask the hospital what documents it requires for an overseas patient, how records should be sent, and whether an interpreter is available for the consent discussion. Confirm who will explain the findings after the procedure and how follow-up will be arranged if you return home. These are questions to confirm with the named provider, not assumptions to make in advance.
ERCP is not the same as endoscopic ultrasound, and it is not a routine screening test. If you are currently unwell with fever, severe pain, jaundice or worsening symptoms, seek local urgent care rather than delaying for overseas planning. A records-based review can help clarify whether ERCP is worth considering, but it does not establish final eligibility or hospital acceptance. The treating clinician must confirm suitability after assessing your individual situation.
For general information about ERCP and how it is planned, see the ChinaSpecialistCare ERCP reference page. An initial enquiry is free and can start with a short summary of your diagnosis, key records and the specific question you need answered. You do not need to buy a proxy consultation to ask whether your case is suitable for review.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.