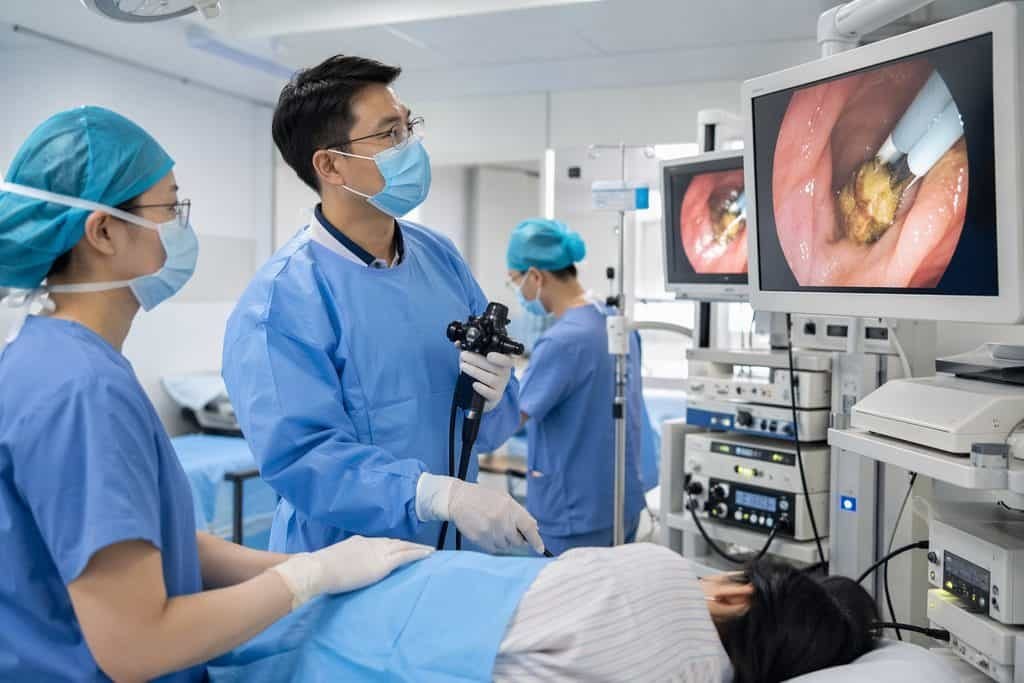
What ERCP is designed to examine and treat
Endoscopic retrograde cholangiopancreatography, or ERCP, combines a flexible endoscope with X-ray imaging to examine the bile ducts and pancreatic ducts. The procedure is not simply a camera test. It is an interventional endoscopic procedure that can both visualise and treat selected problems within those duct systems.
The practical meaning for a patient is that ERCP sits in a specific clinical space. It is used when a treating clinician suspects or has confirmed a duct-related problem that may be amenable to endoscopic treatment. That is different from a general gastrointestinal investigation, and it is different from a purely diagnostic scan. The question is not whether ERCP is a powerful procedure in the abstract, but whether the specific problem in your bile or pancreatic ducts is one that ERCP can actually address.
This distinction matters when you are considering care in China. A hospital may be able to perform ERCP, but that does not automatically mean ERCP is the right treatment for your condition. The treating team must first establish what is wrong, where it is, and whether an endoscopic approach is appropriate. That assessment belongs to licensed clinicians who can review your actual imaging and clinical history.
What ERCP cannot resolve
ERCP cannot resolve every cause of abdominal pain, jaundice, abnormal liver blood tests or pancreatitis. Those symptoms and findings have many possible sources, and only some of them involve the bile or pancreatic ducts in a way that ERCP can treat. If the underlying problem lies outside the duct system, or if it is not accessible endoscopically, ERCP will not be the answer.
ERCP also cannot substitute for a full diagnostic workup. It is not a routine screening test, and it is not equivalent to endoscopic ultrasound, which uses a different technique to examine nearby structures. A patient who arrives expecting ERCP to clarify a vague set of symptoms may be disappointed if the actual problem is not a duct issue that ERCP can reach.
There is also a boundary around what any single procedure can achieve. Even when ERCP is appropriate, it may address one part of a larger condition while other aspects require separate medical or surgical management. The treating team should explain what the procedure is intended to accomplish and what it is not expected to change. If that explanation is unclear, ask for it in writing before you commit to travel or treatment.
The intervention matters: stone treatment, stenting or something else
ERCP is an umbrella term for a family of interventions. The specific thing being done during the procedure changes what it can achieve and what follow-up it requires. Before planning care, you need to know which of these applies to you.
Stone treatment is one common purpose. If a stone is blocking a bile duct, ERCP may allow the clinician to remove it or relieve the obstruction. Stenting is another. A stent can be placed to keep a duct open when there is a narrowing, a leak or another obstruction that cannot be immediately corrected. Other interventions may involve taking tissue samples, dilating a narrowed duct, or treating a specific duct-related complication.
These are not interchangeable. A patient who needs stone removal has a different treatment plan from a patient who needs a stent, and a patient who needs a stent may need a plan for what happens to that stent later. Ask directly: what is the intended intervention, and what is it meant to achieve? If the answer is vague, that is a signal to seek clarification before making arrangements.
It also matters whether later procedures are expected. Some ERCP interventions are planned as part of a sequence, with a follow-up procedure to remove or exchange a stent, or to reassess the duct after an initial treatment. If that is the case, you need to understand the sequence before you travel, because it affects how long you may need to stay and what follow-up you will need.
Individual differences that change the plan
Two patients can both be told they need ERCP and still have very different plans. The duct anatomy, the location and nature of the problem, previous surgery, previous ERCP procedures, and other medical conditions all influence what is possible and what is safe. A clinician cannot determine suitability from a diagnosis label alone.
This is why a records-based review is useful before committing to travel. The treating team needs to see the actual imaging, the procedure reports if any, the laboratory results and the clinical history. A short summary is enough to start an enquiry, but a clinical decision requires the relevant records. The hospital decides suitability after reviewing them.
There is also a limit to what any review can establish remotely. A records-based opinion can help clarify whether ERCP is a reasonable direction and what information is missing, but it does not replace the in-person assessment that a treating clinician will perform. Final decisions about the procedure, its timing and its scope belong to the hospital and the licensed clinicians responsible for your care.
If you have been told that ERCP is not suitable for you, or that a different approach is recommended, that is also important information. It may mean that the problem is not accessible endoscopically, that another treatment is more appropriate, or that further assessment is needed first. Ask what the alternative is and why it is preferred.
What to confirm before planning care in China
Before you make any arrangements, you need clear answers to a small set of practical questions. These are not clinical decisions you make yourself; they are questions you put to the treating team so that you understand the plan.
First, what is the intended intervention? Is this stone treatment, stenting, tissue sampling, dilation, or something else? Second, is this a single procedure or part of a sequence? If follow-up procedures are expected, what are they and when would they occur? Third, what records does the hospital need to assess suitability, and how should they be shared? Fourth, what does the hospital's written estimate include, and what remains to be confirmed? Fifth, what are the arrangements for consent, sedation and post-procedure supervision, and what instructions will you receive?
These questions matter because the answers change your planning. A single stone removal and a staged stent programme are different commitments. A hospital that can perform ERCP is not automatically a hospital that has reviewed your case and accepted you. And an initial enquiry is not a commitment to treatment; it is a way to find out whether the direction is reasonable and what the next step should be.
You do not need to send a complete medical archive at first contact. A brief summary of the diagnosis, the main question and the available records is enough to begin. The team can then explain what else is needed for a proper clinical review.
A practical next step
If you are considering ERCP in China, start by clarifying the clinical question with your current treating team. Ask what the proposed procedure is intended to treat, whether it is diagnostic or therapeutic, and whether follow-up procedures are expected. Having those answers makes any overseas enquiry more useful.
You can then share a brief summary with ChinaSpecialistCare. The initial case review is free and non-clinical. It checks the available diagnosis, records and your main question, identifies missing information and suggests the relevant next step. It is not a diagnosis, not a promise of acceptance, and not a substitute for the treating hospital's own assessment. If a records-based specialist opinion is appropriate, that can be discussed separately, but it is not required to make an initial enquiry.
The hospital decides suitability. Your job is to arrive at that decision with clear questions and the records the clinicians need.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.