Why the design matters more than the brand
Patients often arrive with a question about implant brand or price. The more consequential question is the design: how the proposed prosthesis is supported, how it attaches, and what it is made of. Two clinics can quote the same number of implants and still propose very different treatments.
The Cambridge University Hospitals patient information on dental implants in restorative dentistry makes a useful distinction: implant placement and the restorative phase are separate parts of treatment, and ongoing maintenance matters afterwards. That separation is the key to reading any full-arch plan. The surgery places the anchors; the restorative phase builds the teeth that sit on them. A proposal should describe both, and should say what happens between them.
This is why a single figure such as 'all-on-four' does not fully describe a plan. It names a common approach to supporting a full arch, but the number of implants, the material of the framework, the type of teeth and the number of visits are separate decisions. Ask for the design in writing, not just the procedure name.
Fixed or removable: the question that changes everything
A full-arch restoration can be designed as a fixed prosthesis, which the patient does not take out, or as an implant-supported removable overdenture, which clips onto or rests on the implants and is removed for cleaning. Both are legitimate. They differ in cost, cleaning routine, repair, comfort and how much bone support they need.
If the plan says 'implants' without saying which of these it is, you cannot yet compare it with another quote. Ask directly: will I be able to remove this myself? If yes, how does it attach, and who adjusts it if it becomes loose? If no, how will it be cleaned, and what happens if a screw or component needs repair?
The answer also affects your expectations about the day of surgery. A fixed provisional prosthesis and a removable one are not the same experience in the first weeks. Ask what you will leave with, and what you are expected to eat and how to clean it during that period. The treating team should give you those instructions; they are not something to infer from a brochure.
- Will the final teeth be fixed or removable?
- If removable, how do they attach and who maintains them?
- If fixed, how is cleaning carried out at home?
- What will I leave with on the day of surgery?
How many implants, and why that number
The number of implants supporting an arch is a clinical judgement based on bone volume, bone quality, the opposing bite, the planned prosthesis and the patient's health. Four, six or more implants can all be reasonable in different mouths. The number should come with a reason, not just a package label.
Ask the clinician to explain why that number was chosen for your case and what the alternative would involve. If fewer implants are proposed, ask what the trade-offs are in load distribution and in the design of the prosthesis. If more are proposed, ask what problem the additional implants are intended to solve. You are not expected to make the clinical decision, but you should understand the reasoning well enough to consent to it.
A related question is whether every implant is planned for the same visit. Some designs place all implants at once; others stage placement. The plan should state the intended sequence and what would cause it to change. If a site needs grafting or extraction first, that changes the timeline and possibly the number of trips.
Stages, provisional teeth and the word 'immediate'
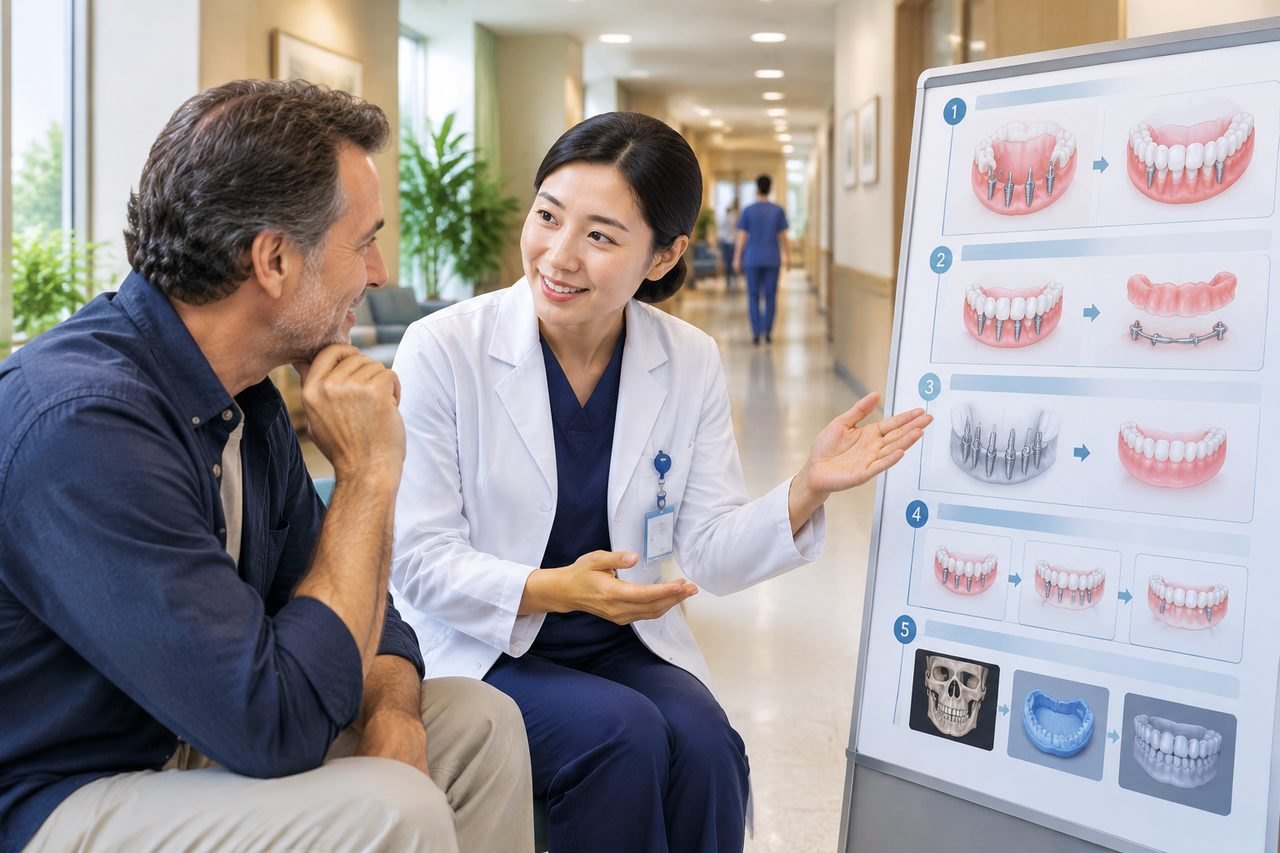
Full-arch treatment is usually described in stages: assessment, any extractions or grafting, implant placement, a provisional phase, and the definitive prosthesis. The provisional phase exists because the implants need to integrate with bone before they carry a final load, and because the bite and appearance often need adjusting once the patient has worn the provisional teeth.
This is where 'immediate' causes confusion. A clinic may offer immediate loading, meaning a provisional prosthesis is attached soon after placement in suitable cases. That is not the same as immediate permanent teeth. Suitability depends on the clinician's assessment of stability and other factors, and it is confirmed individually. Ask what is proposed for you and what the fallback is if immediate loading is not appropriate on the day.
Ask how many treatment stages are planned, which stages require you to be in China, and which can be done with your local dentist. Do not assume a single trip. The number of visits depends on healing, the design, laboratory work and the clinician's judgement, and it should be stated in the plan rather than guessed.
- How many stages are planned, and what happens at each?
- Is immediate loading proposed for my case, and what is the alternative?
- Which stages require travel to China?
- What laboratory work is involved, and who does it?
Records the design should be based on
A full-arch design cannot be responsibly proposed from a photograph and a phone call. It needs imaging of the jaws and bone, an assessment of the bite, and information about the soft tissues and any remaining teeth. Ask which records were used for your proposal and which are still missing.
Useful records typically include a recent panoramic or CBCT scan, intraoral or study-model information, clinical photographs, and details of previous dental work, extractions or grafting. Medical history matters too: conditions and medicines that affect healing or bleeding should be disclosed to the treating team. Do not stop or change any prescribed medicine on your own; that decision belongs to the prescribing clinician.
If you are seeking a records-based opinion before travelling, send the imaging and a short summary of your main question. A remote review can clarify the proposed design and identify missing information, but it does not replace an in-person examination and does not establish final suitability or hospital acceptance. Those are confirmed by the treating clinicians after they see you.
- Recent imaging of the upper and lower jaws
- Bite and occlusal records
- Clinical photographs and any study models
- History of extractions, grafting or previous implants
- Relevant medical history and current medicines
Planning example: two proposals, same arch
Consider a hypothetical patient with an edentulous upper arch and a quote describing 'full-arch implants'. Proposal A specifies four implants, a fixed screw-retained provisional on the day of surgery where stability allows, and a definitive fixed prosthesis after integration. Proposal B specifies six implants, a removable overdenture as the interim restoration, and a definitive fixed prosthesis later. Both are internally coherent. They are not interchangeable.
The questions that separate them are the same ones above: fixed or removable at each stage, how many implants and why, how many trips, what records the design used, and what maintenance is expected. A third proposal might stage grafting first, which changes the sequence entirely. The point of the example is not to recommend a design but to show that the label 'full-arch implants' hides the decisions you are actually being asked to approve.
When you compare proposals, compare the design, the stages and the included components, not only the headline number. Ask each provider to state in writing what is included in their fee and what would be charged separately. Hospital fees, laboratory work, temporary prostheses, repairs and follow-up are all items to clarify with the specific provider; do not assume a convention.
Maintenance, repair and the years after surgery
Full-arch restorations are not maintenance-free. The supporting implants and the prosthesis need review, cleaning and occasional repair or replacement of components. The Cambridge source notes that ongoing maintenance matters, and any plan should say who will provide it and how it will be arranged if you live abroad.
Ask what the treating team recommends for review intervals and hygiene, and whether your local dentist can carry out routine maintenance. Ask what the warranty or repair policy covers, if any, and what would be charged for a repair. These are practical questions with provider-specific answers; they should be in the written plan rather than assumed.
Finally, ask what would make the team revise the plan. Changes in bone, healing, bite or hygiene can alter the design or the sequence. A plan that acknowledges this is more useful than one that presents a single fixed path with no contingencies.
If you have a full-arch proposal and want to understand it before committing, start with a free initial enquiry. Share the proposed design, the imaging you already have and your main question. The team can identify what is missing and suggest the relevant next step; the treating clinicians decide suitability and the final plan.
- Recommended review and hygiene schedule
- Who provides maintenance if you live abroad
- Repair or replacement policy for components
- What would cause the plan to be revised
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.