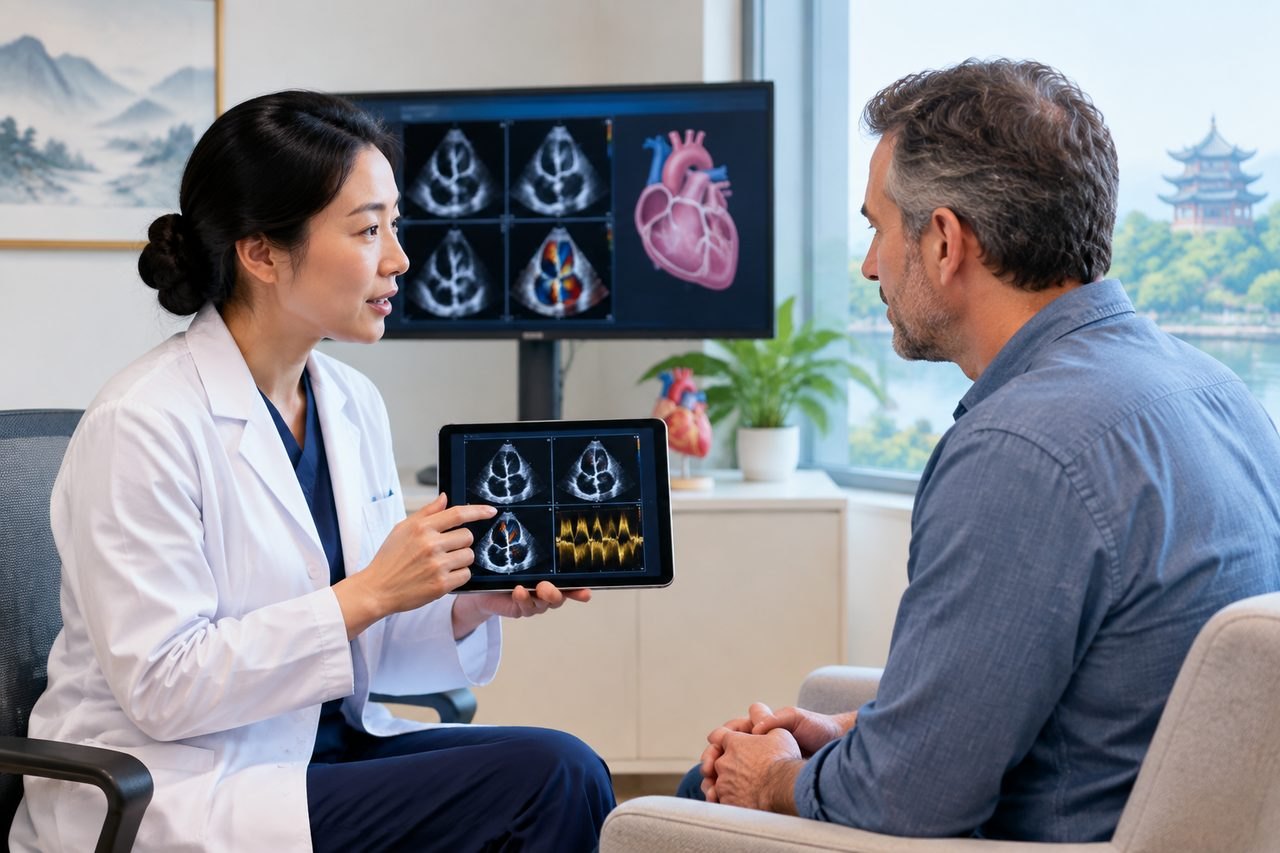
Why the Echo Report Alone Is Not Enough
A one-page echocardiogram summary often states something like 'moderate-to-severe mitral regurgitation' or 'aortic stenosis, severe.' That sentence tells you the valve is abnormal. It does not tell a surgeon whether the valve can be repaired or must be replaced. Valve repair works on the patient's existing valve tissue, reshaping or reinforcing it rather than substituting a prosthesis. Whether that is possible depends on what the tissue looks like, how the leaflets move, where the regurgitation originates, and whether the valve ring is dilated or calcified.
The written report is a radiologist's or cardiologist's interpretation. The images are the raw data. A surgeon reviewing your case remotely needs both. If you send only the report, the specialist can comment on severity and general suitability for surgical referral, but cannot give a meaningful opinion on repair versus replacement. If you send images without a report, the specialist lacks the measurements and the context of how the study was performed.
This is not a reason to delay contacting a hospital. It is a reason to request the full echo dataset from the hospital that performed the study, and to ask what format they can provide.
What to Request from Your Echocardiography Laboratory
When you contact the echocardiography department or the cardiology office that performed your study, ask for the complete study, not a reprint of the conclusion. The specific items below are the ones a valve surgeon typically reviews. If some are not available, say so rather than omitting them silently.
The report itself should include the measured values, not only the impression. Look for: left ventricular ejection fraction and chamber dimensions; left atrial size; valve area calculations if stenosis is present; mean and peak gradients across the valve; pulmonary artery pressure estimate; and a description of leaflet morphology, mobility, calcification, and annular size. For regurgitation, the report should state the mechanism if identified, the vena contracta width or effective regurgitant orifice if measured, and the direction of the jet.
The images should be the original DICOM files or exported cine loops, not screenshots. Ask for the parasternal long-axis, short-axis, apical four-chamber, apical two-chamber, and any dedicated valve views. If a transesophageal echocardiogram has been done, include it. If a stress echo was performed, include that too.
If the laboratory can provide a disc, USB drive, or secure download link, ask which format the receiving hospital in China can accept. Do not assume a format will work; ask the coordination team or the hospital's international office to confirm before you send anything.
What a Remote Review Can and Cannot Establish
A records-based review by a cardiac surgeon can clarify several things. It can confirm the severity of the valve lesion, identify the likely mechanism, note whether the left ventricle is already dilated or impaired, and flag whether the case looks like a straightforward repair candidate or a complex reconstruction. It can also identify missing information that would change the surgical plan.
It cannot confirm repairability. Repairability is determined by the actual tissue quality, the extent of calcification, the presence of infected or destroyed leaflets, and the surgeon's assessment in the operating room. A remote reviewer who says 'this looks repairable' is giving a provisional impression, not a commitment. The final decision is made by the treating surgeon after direct inspection, often with intraoperative transesophageal echocardiography.
It also cannot establish hospital acceptance, surgical scheduling, or a treatment plan. Those are decisions of the treating hospital and its clinical team. A remote opinion is a step in planning, not a substitute for in-person assessment.
Organising the Rest of the Record Without Ordering New Tests
You do not need to arrange new tests before an initial enquiry. Use what you already have. The goal is to give the reviewing clinician a clear picture of your current status and your history, not to complete a checklist.
Gather the most recent cardiology consultation note, including the physician's assessment of symptoms and functional status. Include any cardiac catheterisation report, coronary angiography, or CT angiography if performed. If you have had prior cardiac surgery, include the operative note. If you take anticoagulants or antiplatelet medications, list them with doses, but do not stop or change any medication on your own.
If you have a recent chest X-ray, ECG, or laboratory panel including renal function and blood count, include those. They help the team assess baseline status. If you do not have them, say so; the treating hospital can arrange what it needs after you arrive or during the assessment process.
Do not send passport numbers, payment details, or a complete lifetime archive in the first message. A brief summary with the key reports is enough to start. The coordination team can tell you what else is needed after the initial review.
Questions That Change the Next Step
The answers to a few specific questions determine whether you need to travel for assessment, whether you need a more detailed remote review, or whether you should focus on a different treatment route.
Ask the reviewing clinician: Based on these images, is the mechanism of regurgitation or stenosis one that is typically repairable, or does it suggest replacement? What additional imaging would you need to give a firmer opinion? Does the left ventricular function or chamber size suggest that surgery should be considered soon rather than later? Are there any features that would make a minimally invasive approach unsuitable? What is the expected role of a transesophageal echocardiogram in the preoperative assessment?
Ask the hospital or coordination team: What format do you accept for echo images? Is there a secure upload method? Does the initial review require a proxy consultation, or can it start with a records summary? What is the process for confirming whether the hospital can accept the case?
These questions are not about price or travel logistics. They are about whether the records you have are sufficient for the clinical decision you are trying to make.
What the Treating Surgeon Must Decide in Person
The final decision about valve repair belongs to the treating surgeon and the clinical team in China. They will review your records, but they will also perform their own echocardiogram, which may include a transesophageal study, and they may request additional imaging such as a cardiac CT. They will assess your symptoms, your overall health, your other medical conditions, and your preferences.
This is the point where the record-based phase ends and the in-person phase begins. A remote reviewer can tell you that the images show a posterior leaflet prolapse with a dilated annulus, or that the aortic valve is heavily calcified with a small orifice. The treating surgeon decides whether that particular valve can be reconstructed, whether the surrounding structures will support a durable repair, and whether the patient's overall condition makes surgery appropriate at this time. Those judgements require direct inspection, and they may change once the surgeon sees the valve in the operating room.
If you are considering care in China, the practical next step is to send a brief summary with your most recent echo report and a note about whether images are available. The initial enquiry is free and does not require buying a proxy consultation. The team can tell you what is missing and whether a remote review is useful in your case. The hospital decides suitability after its own assessment.
For more on the procedure itself, see the heart valve repair reference page.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.