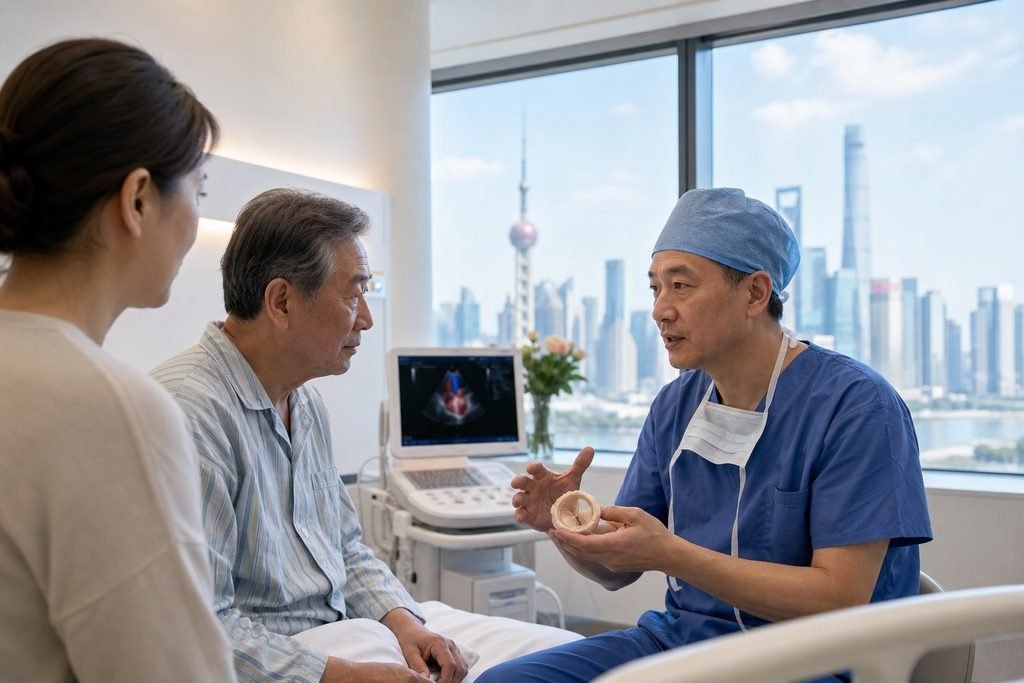
Why valve imaging decides the repair conversation
Heart valve repair works on your existing valve tissue; it is a different operation from replacing the valve with a prosthesis. That distinction is why imaging is not a formality. The surgeon needs to see the valve's structure, movement and the effect on the heart before deciding whether repair is technically possible for that particular valve.
A written report may say 'severe mitral regurgitation' or 'aortic stenosis', but it rarely contains enough detail to plan a repair. The images themselves show which leaflet or part of the valve is affected, how the surrounding structures look, and whether the tissue appears suitable for reconstruction. Two patients with the same report headline can have very different repair prospects.
This is also why a repair assessment cannot be completed from a report alone. If you send only the radiologist's or cardiologist's summary, the surgical team may need to ask for the original files before giving a meaningful opinion. That is not bureaucracy; it is the difference between commenting on a label and assessing your valve.
What the imaging actually needs to show
Echocardiography is the main imaging used to assess heart valves. A transthoracic echocardiogram (TTE) is done through the chest wall and is the standard starting point. A transoesophageal echocardiogram (TEE) passes a probe into the oesophagus and can give clearer views of certain structures, particularly the mitral valve and the left atrium.
For a repair assessment, the surgical team will want to understand the mechanism of the valve problem, not only its severity. Is a leaflet prolapsing? Is there restricted movement? Is the valve ring dilated? Are there signs that the heart has begun to enlarge or weaken in response? These are the details that influence whether repair is feasible and what type of repair might be considered.
Cardiac CT or cardiac MRI may also be requested in some situations, depending on the valve and the question being answered. Coronary angiography is often part of pre-operative assessment in adults, to check the coronary arteries before heart surgery. Which tests are needed for you is a clinical decision, not a fixed package.
When you are preparing records for an overseas enquiry, the useful items are the original DICOM files or the hospital's disc or secure link for echocardiography, plus any CT or MRI studies, and the written reports that go with them. A report without the images may be enough for a first conversation but not for a surgical opinion.
Questions that imaging answers, and questions it cannot
Imaging can help answer whether the valve looks repairable, which parts are involved, and whether the heart's chambers are coping. It cannot answer every question that matters to you. It does not tell you how long a repair will last in your case, whether you will need anticoagulation afterwards, or whether a repair is preferable to replacement for your individual situation. Those are clinical judgements that depend on the valve, your age, your other health conditions and the surgeon's assessment.
It is reasonable to ask the surgical team directly about uncertainty. You can ask what the imaging shows about repairability, what the alternatives are if repair is not possible during surgery, and what the evidence says about risks and outcomes for someone with your valve problem. A responsible clinician can discuss evidence-based estimates and their limitations without guaranteeing a personal result.
You can also ask whether a repair would be attempted with a planned fallback to replacement if the valve proves unsuitable once the surgeon sees it directly. This is a common planning question, and the answer belongs to the treating team, not to an article.
Preparing imaging records for a China hospital
Hospitals in China vary in how they accept foreign imaging. Some can review a disc or a secure download link; others may ask for specific formats or repeat certain studies after you arrive. Rather than assume a universal rule, ask the specific hospital or your coordination contact what format and what items it needs.
A practical starting set for an enquiry usually includes: the most recent echocardiogram images and report; any cardiac CT or MRI images and reports; the most recent cardiology clinic letter or summary; a list of your current medicines with doses; and a short note of your main symptoms and how they have changed. You do not need to send a complete lifelong archive at first contact.
If you have had a previous heart operation or a prior valve procedure, include those records too. Scar tissue and previous repair attempts can affect what is possible now, and the surgical team will want that history.
Keep a copy of everything you send. If you travel, bring the original discs or files with you as well as digital copies, because the receiving hospital may want to review them directly.
How imaging connects to admission and follow-up planning
Once a hospital has reviewed your imaging and accepted you for assessment, the next stage is usually an in-person evaluation in China. That visit may include repeat or additional imaging, blood tests, and review by a cardiologist and cardiac surgeon. The exact sequence and how many visits are needed depend on the hospital and your case; ask the provider to explain its own process rather than relying on a general timeline.
Follow-up imaging after surgery is part of the plan, not an afterthought. You will want to know what imaging will be done, when, and how the results will be shared with your cardiologist at home. Ask how the hospital communicates with your local team and what records you will receive before discharge.
Prescribed care after valve surgery, including medicines and activity restrictions, is decided by the treating team. If you take anticoagulants or other cardiac medicines, do not change them on your own before travel. Ask the prescribing clinician how your medicines should be managed around the trip and the operation.
If your symptoms are worsening, seek local medical assessment first. An overseas enquiry should not delay urgent care.
What to confirm before you commit to travel
Before booking anything, confirm in writing what the hospital has agreed to review, what it has quoted, and what remains to be decided in person. Ask whether the quoted scope includes the consultation, imaging, surgery, intensive care, ward stay, medicines and follow-up, or whether some items are billed separately. Ask the named provider how its written estimate is structured rather than assuming a standard.
Ask who will be your main surgical contact, how interpretation will be arranged, and what the hospital expects you to bring. Ask what happens if the valve turns out not to be repairable during surgery, and how that decision would be communicated to you or your family.
You can begin with a free initial case review through ChinaSpecialistCare. Our team checks the available diagnosis, records and your main question, identifies missing information and suggests a relevant next step. This is not a diagnosis or a promise of acceptance, and it does not replace the hospital's own assessment.
If you want a records-based opinion before travelling, a proxy consultation is available as an optional step, not a prerequisite for every appointment or operation. The hospital decides suitability, and no coordinator can guarantee a clinical outcome.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.