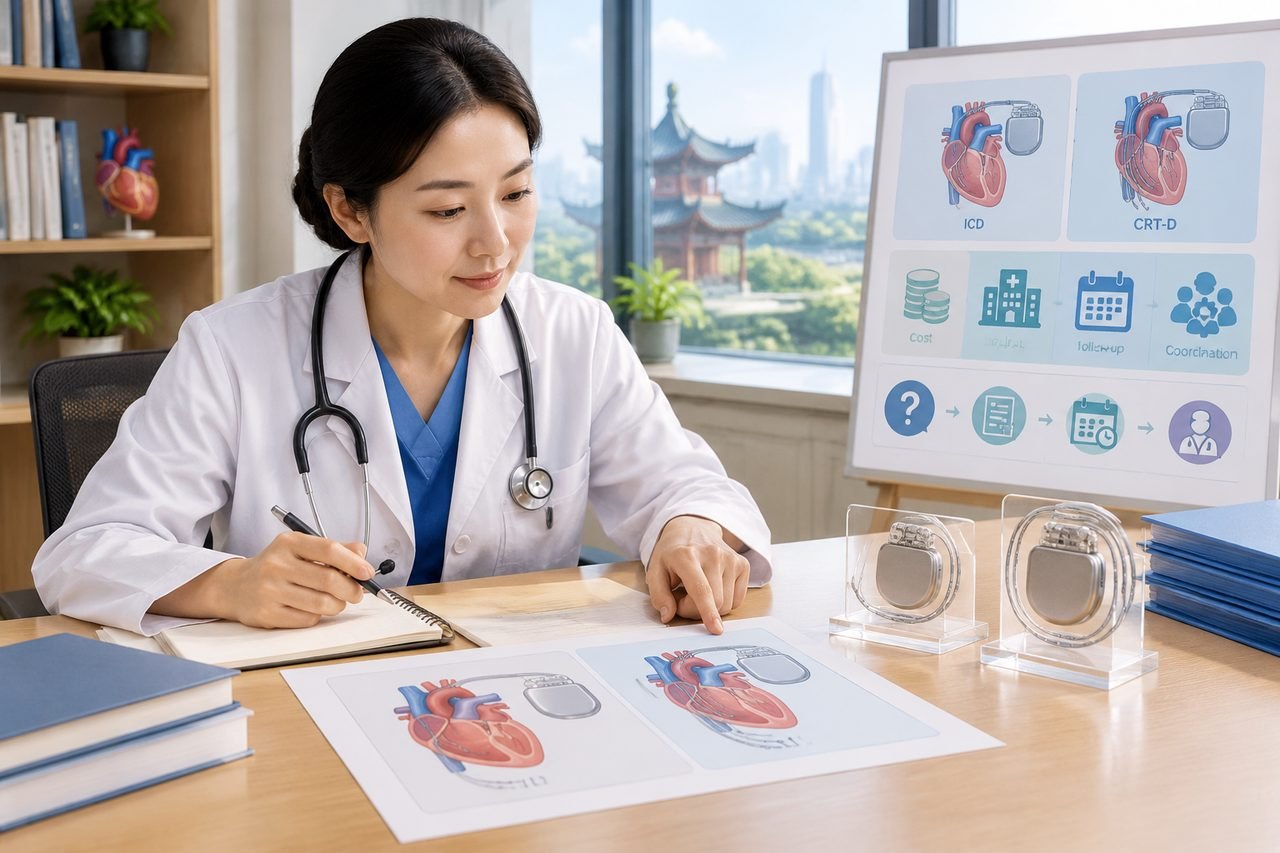
Why one ICD or CRT quote rarely answers the cost question
When an overseas patient asks what an ICD or CRT will cost in China, the honest starting point is that the answer depends on which device is being discussed. An implantable cardioverter defibrillator (ICD) is used to treat dangerous heart rhythms. A cardiac resynchronisation therapy device with defibrillation (CRT-D) also supports coordinated pumping. Those are different clinical jobs, and they are not interchangeable labels for the same product.
That clinical difference flows straight into the estimate. A hospital quote for one device configuration does not automatically describe the other. If you receive a single figure without knowing whether it refers to an ICD, a CRT pacemaker or a CRT-D, you cannot yet tell what is included. The first useful step is not to compare totals but to establish which device category the treating team is actually considering for your case.
This matters because the decision about device type belongs to the cardiology team, not to a cost comparison. Your role in the estimate conversation is to make sure the quote names the device category clearly, so that any figure you receive can be matched to the clinical plan rather than to a generic label.
The four cost layers to separate before comparing anything
A workable ICD or CRT estimate in China separates at least four layers. The first is the device itself: the specific generator and, where relevant, the leads. The second is the hospital's professional and facility charges for implantation, including the procedure, the ward and any associated hospital services. The third is follow-up: device interrogation, programming checks and any remote-monitoring arrangements the treating team uses. The fourth is coordination, which is separate from hospital charges.
These layers behave differently. Device cost depends on the specific product and configuration. Hospital charges depend on the institution and the ward route. Follow-up scope depends on how the treating team plans to monitor the device over time and whether any of that can be done locally or remotely. Coordination charges are set by the coordinating service, not by the hospital.
If a quote blends these layers into one number, ask for them to be itemised. You are not trying to negotiate the clinical plan; you are trying to see which parts of the total are device, which are hospital, which are follow-up and which are coordination. Without that split, two quotes for different devices can look comparable when they are not.
Questions whose answers change the estimate
The most useful thing you can do before requesting an estimate is to prepare a short list of questions whose answers genuinely change the number. These are not administrative formalities; each one moves the estimate in a different direction.
Ask which device category is being considered for your case and why. Ask whether the quoted figure refers to the device alone, the device plus implantation, or a broader package. Ask what follow-up is included in the quote and what would be arranged separately. Ask whether the hospital's written quote distinguishes ward type, since different ward routes can carry different charges. Ask what the coordination fee covers and what it explicitly does not cover.
Each answer changes the next step. If the device category is not yet fixed, the estimate is provisional and should be treated as such. If follow-up is not included, you need to understand how monitoring would be arranged after you leave China. If the ward route is not specified, the hospital figure is incomplete. These are the points where a vague quote becomes a usable one.
- Which device category is being considered, and what is the clinical reason?
- Does the figure cover the device alone, or device plus implantation?
- What follow-up is included, and what would be arranged separately?
- Does the hospital quote distinguish ward or accommodation route?
- What does the coordination fee cover, and what does it exclude?
What a records-based estimate can and cannot tell you
A records-based estimate is a planning tool, not a final bill. It can help you understand the likely structure of costs for your situation, and it can reveal which information is still missing. It cannot confirm hospital acceptance, final device selection or the exact charges that will apply on the day.
To make an estimate useful, the hospital needs enough clinical context to understand what is being proposed. That typically means a summary of your cardiac history, relevant imaging and rhythm documentation, current medications and the specific question your cardiologist wants answered. You do not need to send a complete archive at first contact; a brief summary is enough to start, and the team can tell you what else would help.
The estimate should also state its own limits. It should say which device category it assumes, which hospital charges it includes, what follow-up it covers and what remains to be confirmed. An estimate that does not state these things is not yet a comparison tool. Treat any figure without that context as a starting question rather than a final answer.
Follow-up scope: the part most often left out
Follow-up is where ICD and CRT cost comparisons most often become unclear. Device interrogation, programming review and any remote-monitoring arrangements are part of the ongoing care of an implanted device, and their scope varies by treating team and by device. A quote that covers implantation but says nothing about follow-up leaves a real gap in your planning.
Ask the treating team how follow-up is structured for the device being considered. Ask whether any checks can be done locally in your home country and what information the China team would need from those checks. Ask whether remote monitoring is part of the plan for this specific device, rather than assuming it is available for every configuration. These are questions for the clinical team, and the answers depend on your individual situation.
Do not assume that every CRT device includes a defibrillator, that remote monitoring is compatible with every device, or that MRI access is guaranteed after implantation. Those are device-specific and patient-specific questions. If any of them matter to your planning, raise them directly with the cardiology team and ask for the answer in writing.
How to prepare a comparison you can actually use
A useful comparison starts with a single device category and a single hospital route, then adds the other layers one at a time. Begin with the clinical plan: which device category, and why. Then ask the hospital for its written quote covering the device and implantation, with ward route stated. Then ask separately about follow-up scope. Then add the coordination fee, which is separate from hospital charges.
Keep the questions in writing and keep the answers in the same document. If a figure changes, note what changed and why. If a layer is missing, leave it blank rather than filling it with an assumption. A comparison with one honest gap is more useful than a tidy total that hides which device or which follow-up it describes.
When you are ready, you can share a brief summary of your situation through the enquiry form, email or WhatsApp. An initial enquiry is free and does not require buying a proxy consultation. The hospital decides suitability, and the treating cardiology team confirms the device plan. The relevant procedure reference on this site explains the implantation context; the cost conversation above is about how to compare estimates, not about a fixed price.
For the clinical background on what an ICD does, the British Heart Foundation's page on implantable cardioverter defibrillators is a useful starting point. It explains the device's role in treating dangerous heart rhythms, which is the clinical distinction that makes ICD and CRT-D estimates non-interchangeable.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.