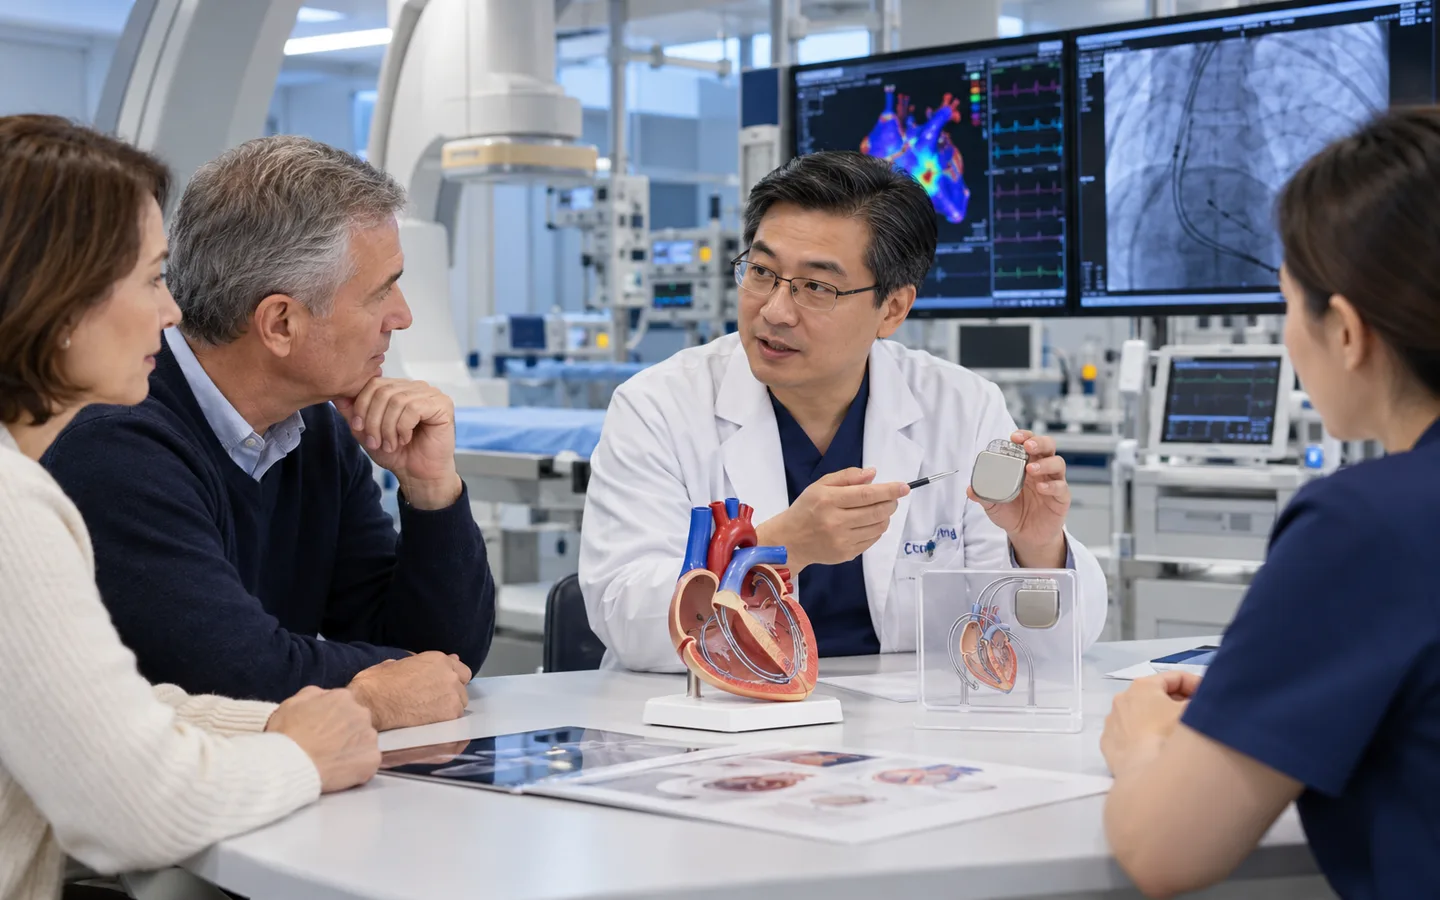
ICD and CRT devices solve different but sometimes overlapping problems
An ICD detects and treats life-threatening ventricular arrhythmias. CRT paces both ventricles to improve coordination in selected heart-failure patients with electrical delay.
Some patients need CRT with defibrillation capability; others need pacing without shocks or an ICD alone. Device choice requires more than a low ejection fraction.
Heart function can improve after medical treatment or revascularization. Implant timing should follow the applicable guideline pathway unless secondary prevention is urgent.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about implantable defibrillator or cardiac resynchronization therapy.
- Survivors of selected cardiac arrest or sustained ventricular arrhythmia.
- Persistent low ejection fraction with meaningful life expectancy despite appropriate therapy.
- Symptomatic heart failure with a qualifying conduction pattern for CRT.
- A device upgrade considered because of pacing burden or worsening function.
What the specialist team must confirm
The team reviews arrhythmia history, ejection fraction trend, ECG width and morphology, heart-failure medicines, ischemia or revascularization, scar imaging, comorbidity, infection risk, venous anatomy and goals concerning shocks and end-of-life care.
Key points for this treatment

From risk stratification to individualized device therapy
The expected benefit must exceed procedural risk and the competing risk from non-arrhythmic illness.
Device data and clinical response are interpreted together
Early follow-up checks wound, leads, sensing, pacing and programmed therapies. A shock requires device-record review rather than assumption about the rhythm.
Long-term care tracks battery, leads, arrhythmias, biventricular pacing and heart-failure response. Goals and shock settings may change with health status.

Risks, limits and realistic expectations
Risks include bleeding, infection, pneumothorax, lead failure, inappropriate shocks, failure to terminate arrhythmia, vein obstruction and need for revision or extraction. CRT does not improve every patient with heart failure.
Multiple shocks, a shock with ongoing symptoms, fainting, chest pain, severe breathlessness or device-pocket infection requires urgent local care.