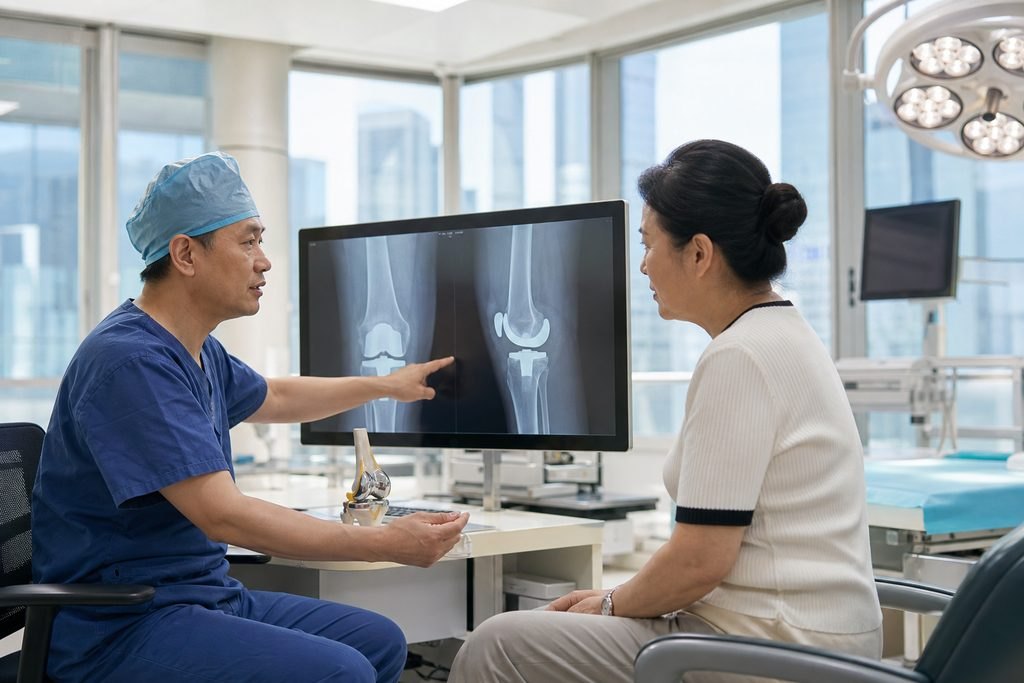
What a records-based review can and cannot settle
A records-based opinion is useful for organising what you already have: imaging reports, operation notes, injection history, therapy records and your main question. It can identify missing information and suggest which specialist or assessment route is relevant. It cannot replace the physical examination that shows how your knee actually behaves under load, how stable it feels and how your walking pattern has changed.
This distinction matters when you are deciding whether to travel. If your question is mainly about whether your diagnosis is complete or whether your records are sufficient for a specialist appointment, a records review may be enough to plan the next step. If your question is about which operation fits your knee, or whether a previous treatment has changed your options, the answer depends on findings that only appear when a clinician examines you.
For knee osteoarthritis, the treating team needs to see how the joint lines up, how much the knee bends and straightens, whether it feels stable, and how pain and function respond during the visit. Those findings shape the recommendation. A file can describe what was recorded before; it cannot show what your knee does now.
Knee alignment: why imaging alone may not answer the question
Alignment describes how the thigh bone, shin bone and kneecap relate when you stand and walk. X-rays taken while you bear weight can show the angle between the bones, but the treating doctor also needs to see how you stand, how you shift weight and whether the knee drifts inward or outward during movement. A report may mention alignment, yet the clinical meaning depends on the examination.
This is one reason a remote review cannot confirm whether a partial or total replacement is suitable. Partial knee replacement is generally considered when damage is limited to one part of the knee and the other compartments are relatively preserved. Alignment and ligament stability are part of that assessment. If alignment has changed significantly, or if more than one compartment is affected, the recommendation may differ.
Ask the treating team directly: does my alignment affect which operation you would consider, and what would you need to see in person to decide? That question is more useful than asking for a general opinion from imaging alone.
Previous injections and therapy: what the file may not show
Injection history is often recorded as a date and a drug name, but the response matters. Did the injection help, for how long, and what changed afterwards? Therapy records may show attendance, yet they may not show whether your strength, walking tolerance or pain pattern improved in a way that changes the next decision.
The treating doctor will want to know what was tried, what happened and what you can do now. If you have had several injections, the pattern of response can influence how the team thinks about ongoing treatment. If therapy helped, that may support continuing a non-surgical route; if it did not, the team may consider other options. These are clinical judgements, not conclusions you can draw from a record alone.
Before an appointment, gather a simple timeline: what treatment, when, and what changed. Bring the actual reports if you have them. If you do not have them, say so clearly rather than guessing. The treating team can then tell you what it still needs.
Partial versus total replacement: the decision that needs examination
Total knee replacement resurfaces the damaged joint surfaces with artificial components. Whether that is the right operation for you depends on the pattern and extent of joint damage, your symptoms and function, and findings from the physical examination. Partial replacement is a different operation with different selection criteria. A records review can explain the general difference, but it cannot confirm which one fits your knee.
The gap between a file and an examination is easiest to see in the questions that keep coming back. A report may state that one compartment is affected, but the surgeon also needs to know how the knee behaves when you stand, turn and climb a step. A note may record that the knee bends to a certain angle in clinic, but the surgeon needs to see whether pain, swelling or guarding changes that range on the day. Ligament stability is another finding that depends on hands-on testing rather than a written description.
This is why a records-based opinion can be genuinely useful and still leave the operation undecided. It can tell you whether the records are complete enough for a specialist to review, whether a partial or total replacement is even the right question to be asking, and what the team would need to examine before giving a view. It cannot substitute for the examination itself, and it should not be presented as if it can.
If you are seeking care in China, ask the hospital what its assessment includes and whether it requires imaging taken at that hospital or accepts recent outside imaging. Do not assume that a previous scan will be accepted without review. The hospital decides what it needs. Ask, too, whether the surgeon who reviews your file is the same person who would examine you, because that affects how much weight the remote opinion can carry.
One practical way to frame the question is to separate what is decided from what is pending. A records review can confirm that you have a diagnosis of knee osteoarthritis, that certain treatments have been tried, and that imaging exists. It cannot confirm which operation fits, whether you are a candidate for a partial replacement, or what your function will be after surgery. Those remain open until the examination.
When you write to the hospital, say plainly which of those two categories your question falls into. If you are asking whether your file is complete, a records review may answer that. If you are asking which operation to have, the honest answer is that the examination comes first. A hospital that tells you otherwise is not giving you a more useful opinion; it is giving you a less reliable one.
Questions to send before you travel
A short, specific list helps the hospital tell you what can be answered remotely and what must wait for an examination. Write your questions in plain language and include the main decision you are trying to make. For knee osteoarthritis, useful questions include:
Does my alignment affect which operation you would consider, and what would you need to see in person? How do my previous injections and therapy affect your view of my options? Based on my records, can you tell whether partial or total replacement is more likely, or does that require examination? What imaging and records should I bring, and will you accept recent imaging from my home country? What does your written estimate include, and what remains undecided until after assessment?
These are questions for the treating team, not conclusions you should draw yourself. The hospital decides suitability, and no outcome is guaranteed. If your symptoms are worsening or you have new pain, swelling or difficulty bearing weight, seek local medical care rather than waiting for an overseas appointment.
Practical preparation and the next step
Gather your records in a simple order: imaging reports and images, operation notes, injection and therapy history, a medication list and a short summary of your main question. You do not need to send a complete archive at first contact. A brief summary is enough to start. After that, the team can tell you what else is needed.
If you want help requesting a specialist appointment or arranging interpretation, ChinaSpecialistCare can assist with non-clinical coordination. An initial enquiry is free and does not require buying a proxy consultation. The hospital and its clinicians decide diagnosis, suitability and treatment. You can start with a short summary by the enquiry form, email or WhatsApp, and share records after first contact.
The practical next step is to write your three most important questions and send them with a brief summary of your knee history. Ask the hospital which questions it can answer from records and which require an in-person assessment. That reply will tell you whether a records review is enough for now or whether you need to plan a visit.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.