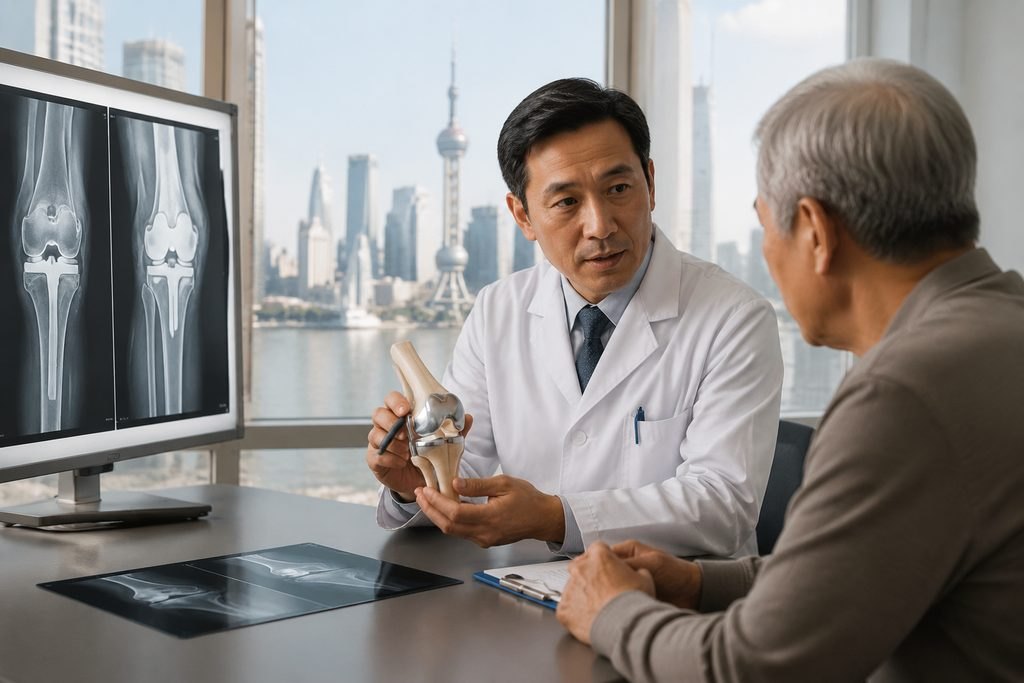
What an MDT discussion is meant to resolve
A multidisciplinary team discussion brings two or three relevant specialties together to review the same records and reach a shared view. For knee osteoarthritis, that might involve an orthopedic surgeon, a physiotherapist or rehabilitation physician, and a radiologist or rheumatologist depending on the case. The purpose is not to replace the treating surgeon's judgment. It is to make the reasoning visible before anyone commits to an operation, an injection, or a further course of conservative care.
The practical value for an overseas patient is that a single conversation can surface disagreements early. If one specialist thinks the arthritis is mainly patellofemoral and another sees tricompartmental change, that difference matters. If the alignment films suggest the mechanical axis is drifting, the choice between partial and total replacement may hinge on it. An MDT format is one way to test those questions together rather than sequentially.
What an MDT cannot do is guarantee that a particular hospital will offer this format, that a specific surgeon will attend, or that the discussion will produce a definitive plan. Those are provider-specific facts. The useful move is to ask what the named hospital actually runs, who participates, and how the conclusion is documented.
Is the diagnosis and alignment confirmed, or still assumed?
Knee osteoarthritis is a clinical and radiographic diagnosis. Symptoms and function are part of the assessment, not an afterthought. Before any discussion about surgery, the team should be able to state what the standing alignment films show, whether the arthritis is confined to one compartment or involves more, and whether the patient's main limitation is pain, stiffness, instability, or reduced walking distance.
Alignment studies matter because they change the operation being considered. A knee with arthritis limited to the medial compartment and preserved lateral joint space may be a candidate for partial replacement in some patients. A knee with involvement across compartments, significant deformity, or ligament instability points toward total replacement. The source material for total knee replacement describes resurfacing damaged joint surfaces with artificial components; it does not by itself determine which patient should receive which implant.
The MDT question to ask is concrete: which imaging has been reviewed, what does it show about alignment and compartment involvement, and does the team agree on the diagnosis? If the answer is that alignment has not been assessed, that is a gap to close before comparing surgical options. If the answer is that the diagnosis is clear, the discussion can move to the next decision.
What did previous injections and therapy actually achieve?
A history of injections and physical therapy is not a checklist item. It is evidence about how this knee responds. The MDT should establish which injections were given, when, and what changed afterward: pain relief, duration of relief, return of function, or no meaningful change. It should also establish what therapy was tried, whether it was supervised, and whether the patient completed it.
This matters because the same intervention can mean different things. A short-lived response to an injection may suggest the pain source is not what was assumed. A good response that faded may support a different conversation than no response at all. A therapy program that was never completed is not the same as one that failed. The team needs the actual sequence, not a summary that says conservative treatment was tried.
The MDT question is whether the previous treatments change the current recommendation. If they do, the team should say how. If they do not, the team should say why. Either way, the patient should leave with a clearer sense of what has already been learned about this knee.
Partial or total replacement: what decides it?
Partial and total knee replacement are different operations with different selection criteria. Partial replacement preserves the unaffected compartments and ligaments; total replacement resurfaces the joint more completely. The choice depends on the pattern of arthritis, alignment, ligament function, body weight, activity goals, and the surgeon's assessment of what will last.
The distinction is not academic. A partial replacement leaves the healthy side of the knee and the cruciate ligaments in place. That can mean a smaller operation and a knee that still feels like the patient's own, but it also means the remaining compartments must be healthy enough to carry the load. If the arthritis has already spread, or if the ligaments no longer stabilise the joint, a partial implant may not be the right answer. A total replacement addresses the whole joint surface, which is why it is considered when more than one compartment is involved.
An MDT discussion should answer whether the team agrees on the pattern of disease and whether that pattern supports one operation over the other. It should also answer what would change the recommendation: if alignment worsens, if the patient's goals change, or if a trial of non-surgical care is preferred first. These are not rhetorical questions. They are the points where a second opinion or a different specialty can add value.
The patient-facing question is whether the team can explain, in plain terms, why one option is being proposed and what the alternative would involve. If the explanation is missing, the discussion has not finished its job. The patient should also ask what the team would need to see to change its mind, and whether that information is already available or still needs to be collected.
What the MDT should document for an overseas patient
For a patient travelling to China, the output of an MDT discussion should be usable before travel and after arrival. At minimum, it should state the diagnosis, the imaging reviewed, the agreed surgical or non-surgical recommendation, the alternatives considered, and the main uncertainties. It should also state what further information is needed before a final decision.
It is reasonable to ask whether the discussion summary will be provided in English, whether it will name the specialties involved, and whether it will distinguish a provisional view from a confirmed plan. These are administrative questions, not clinical ones, and they can be asked of the hospital's international office or the coordinating team. The answers will vary by provider, so they should be confirmed in writing rather than assumed.
A related practical point is that an MDT review is not the same as hospital acceptance. A discussion can recommend surgery while the hospital still needs to complete its own admission process. The patient should ask what remains before a date can be set and what would cause the plan to change.
How to ask for an MDT discussion without assuming it exists
The honest starting point is that not every hospital runs a formal MDT for knee osteoarthritis, and those that do may reserve it for complex or cross-specialty cases. The patient's task is to ask a specific question of a specific provider: does this hospital offer a multidisciplinary discussion for this diagnosis, who participates, what records are needed, and how is the conclusion shared?
If the answer is yes, the next step is to prepare the records that make the discussion useful: recent standing knee X-rays, any alignment or weight-bearing films, MRI or CT reports if available, a list of previous injections with dates and responses, therapy notes, and a clear statement of the patient's main functional goal. These are the inputs that let the team answer the questions above rather than repeat general advice.
If the answer is no, that does not close the door on care in China. It means the decision will rest with the treating surgeon and the specialties that surgeon chooses to involve. The same questions still apply; they are simply asked in a different format. A free initial enquiry can help identify which records are missing and which provider route fits the case, without committing the patient to a proxy consultation or any particular service.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.