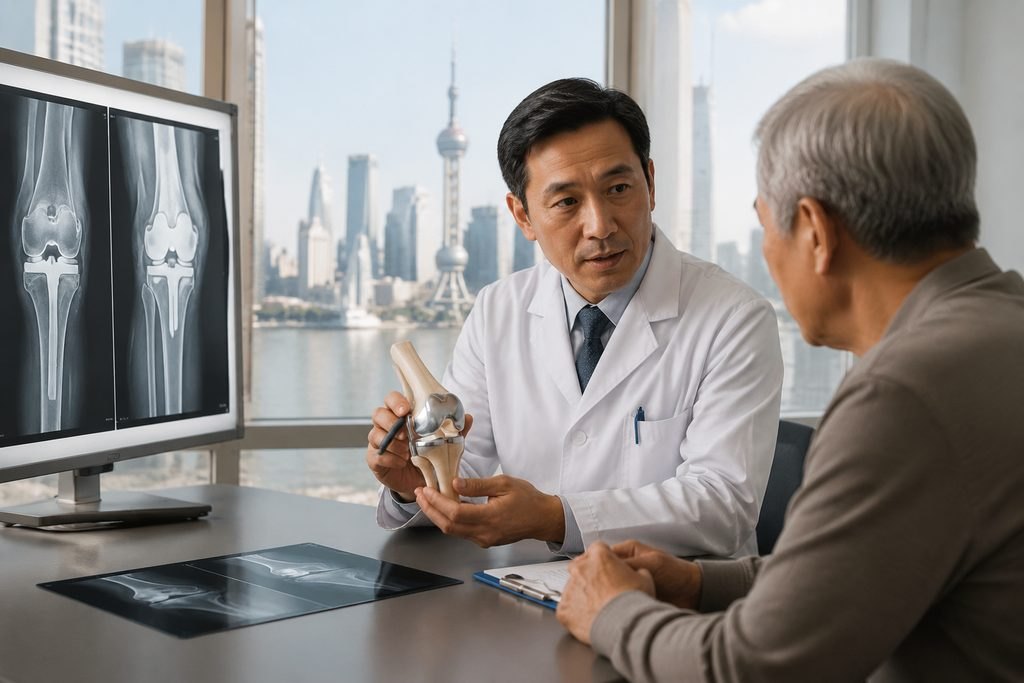
The decision that missing records can leave open
Knee osteoarthritis care is not one procedure. For some people the question is whether a partial knee replacement is technically suitable; for others it is whether total knee replacement is the more reliable option; for others it is whether injections, physiotherapy or weight management should continue first. These are different decisions, and they depend on different pieces of information.
When records are incomplete, the gap is rarely about the diagnosis itself. Most patients arrive with a report that already says osteoarthritis. The gap is usually about the detail behind that diagnosis: how the joint surfaces are worn, where the wear sits, how the knee aligns, what has already been tried, and how the knee has responded. Without that detail, a clinician reviewing your file at a distance can describe the general problem but cannot responsibly answer the specific question of which operation, if any, fits your knee.
This is why a missing-record problem is not solved by sending more of the same report. Sending three copies of the same X-ray report does not replace one alignment study. Sending a discharge summary without the operation note does not replace the detail of what was done. The useful step is to identify which question is unanswered, then ask whether the missing item can be obtained.
Knee alignment studies: why a standard X-ray report may not be enough
Alignment describes how the mechanical axis of the leg passes through the knee. It matters because osteoarthritis can wear the inner or outer compartment differently, and that pattern influences whether a partial replacement is even considered. A standard X-ray report often comments on joint space narrowing and osteophytes. It may not measure alignment in the way a surgical assessment needs.
If your records include only a radiology report and no images, the reviewing clinician may be able to read the conclusion but not verify the measurement. If your records include images but no weight-bearing or alignment views, the same limit applies. This is not a reason to repeat every scan. It is a reason to ask the treating team which specific views or measurements they need to answer the partial-versus-total question for your knee.
A practical way to phrase this in an enquiry is: 'I have X-ray reports from [date] and MRI from [date]. I do not know whether alignment was measured. Can you tell me which views or measurements your team would need to assess partial versus total replacement?' That question is more useful than sending a large file without context.
Previous injections and therapy: the history that changes the next step
Injections and non-surgical therapy are not background details. They are part of the decision. If you have had corticosteroid injections, hyaluronic acid injections, or a course of physiotherapy, the timing, the site, the response and any complication all matter. A clinician considering surgery wants to know what has already been tried and whether it helped.
Missing this history can leave two things unclear. First, whether non-surgical care has been given a fair trial. Second, whether a recent injection affects the timing or safety of a proposed operation. Guidelines and treating teams differ on how they handle injection history before surgery, so this is a question for the clinician who examines you, not a rule you can assume from a general article.
If your injection records are held by a clinic that has closed, or if you cannot remember the product used, say so plainly. A clear statement of what is unknown is more useful than an approximate guess. The treating team can then decide whether the missing detail changes their assessment or whether it can be managed another way.
Partial versus total replacement: what the records must support
Partial knee replacement and total knee replacement are different operations with different selection criteria. Total knee replacement resurfaces the damaged joint surfaces with artificial components, and assessment includes symptoms and function. Partial replacement is generally considered when the wear is confined to one compartment and the other compartments and ligaments are suitable. That is a clinical judgement, not a label that can be applied from a report alone.
If your records do not show which compartments are affected, how the ligaments behave, or how the knee aligns, the partial-versus-total question cannot be answered. A clinician may still give a provisional view based on what is available, but that view is not the same as a surgical plan. It is reasonable to ask what remains uncertain and what would change the recommendation.
This is also where a records-based opinion has a clear limit. A remote review can identify what is missing and explain the options in general terms. It cannot confirm that a partial replacement is suitable for your knee, and it cannot promise that a particular implant or approach will be used. Those decisions belong to the treating hospital after examination and imaging review.
What to send, what to ask, and what to leave for the clinician
A useful first summary does not need to be a complete archive. It needs to state your main question, your current symptoms and function, the treatments you have already tried, and the records you hold. From there, the missing items can be identified before anything is translated or sent.
When you contact a provider, ask three things. First, which records are needed to answer your specific question. Second, whether the provider can work from reports alone or needs the actual images. Third, what remains uncertain until a clinician examines you. These questions apply whether you are enquiring about care in China or anywhere else.
Keep the distinction between a coordination service and a clinical opinion clear. A coordination team can help organise records, request an appointment and explain what a hospital has asked for. It does not decide whether you need surgery, which operation is suitable, or whether you will be accepted. The hospital and its clinicians make those decisions.
- A short summary of your main question and current function.
- Dates and types of imaging you hold, and whether you have the images or only the reports.
- A list of injections, physiotherapy and other treatments, with approximate dates and responses.
- Any operation notes or discharge summaries from previous knee procedures.
- A clear note of what you cannot obtain, so the clinician knows the limit of the file.
Next step: turn the gap into a specific question
The practical next step is not to gather everything you can find. It is to turn the gap into a question a clinician can answer. Write down what you know, what you do not know, and what decision you are trying to make. Then ask a provider which records are needed for that decision and what remains uncertain without them.
An initial enquiry is free and does not require buying a proxy consultation. You can start with a brief summary by the enquiry form, email or WhatsApp, and the team can explain how to share records after first contact. If a records-based opinion is useful, it can be discussed separately, but it is not a prerequisite for every appointment. The treating hospital decides suitability, and no review can promise acceptance or a clinical outcome.
If your knee symptoms are worsening, or if you have new swelling, locking, inability to bear weight or signs of infection, seek local medical assessment rather than delaying for an overseas enquiry.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.