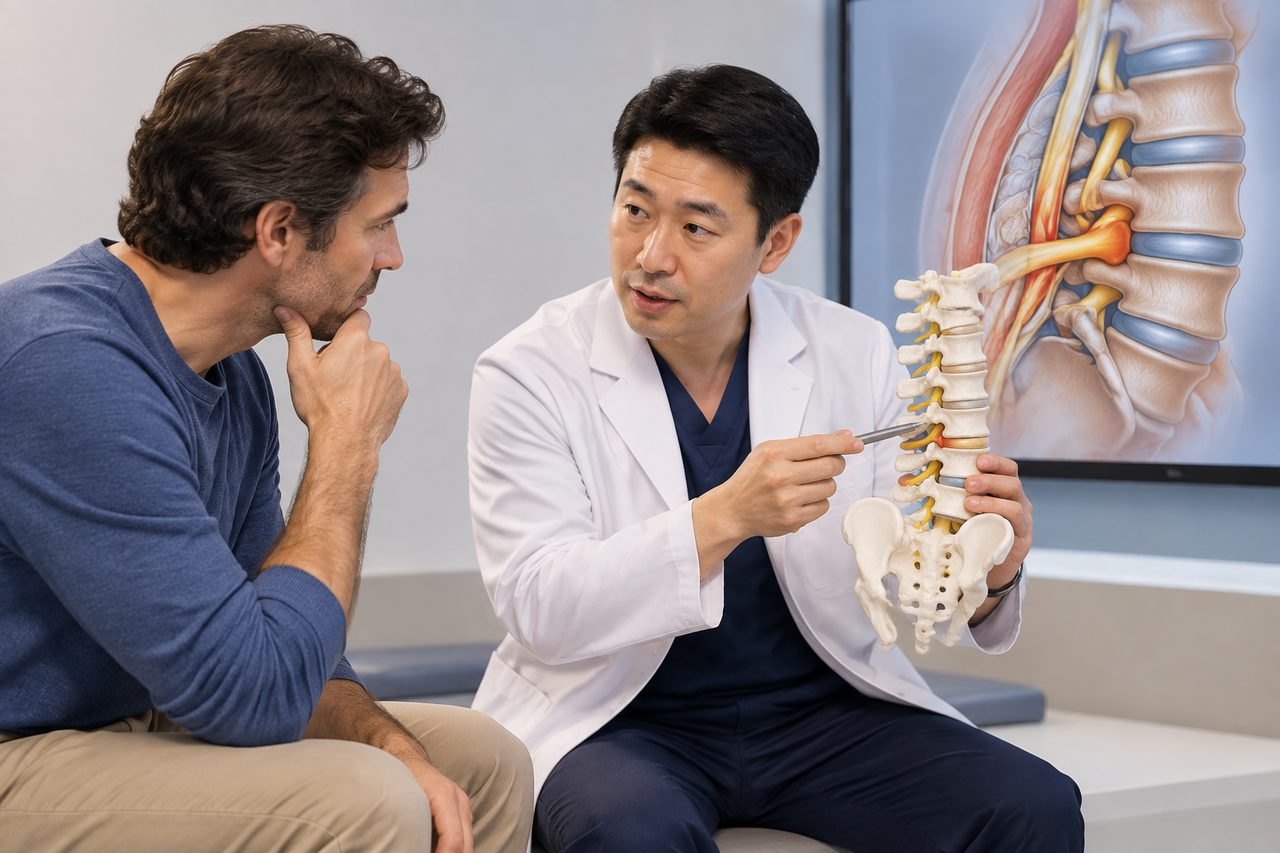
What lumbar decompression is meant to do
The core aim of lumbar decompression is to relieve pressure on nerves in the lower spine. That is the clinical purpose described by the NHS. The operation creates more room around the compressed nerve structures, and the treating team decides how that is done based on your symptoms, examination and imaging.
This matters because patients often arrive with a mixed set of expectations. They may hope that every source of back pain disappears, that the spine is 'rebuilt', or that a decompression is the same as a fusion. Those are different operations with different goals. A decompression addresses nerve compression. A fusion addresses instability or alignment in a different way. If your main problem is mechanical back pain without nerve compression, a decompression may not be the right tool, and the treating surgeon should explain why.
The practical question is not 'Is decompression a good operation?' It is 'What is this operation meant to change for me, and what will it leave unchanged?' Ask the clinical team to state the goal in plain terms: which symptoms are expected to improve, which may persist, and what the alternatives are.
- Nerve-related symptoms such as leg pain, numbness or weakness are the usual reason decompression is considered.
- Persistent back pain alone may have a different explanation and a different treatment path.
- Decompression and fusion are separate procedures; ask which one is being proposed and why.
Why the treatment goal changes the whole plan
Once the goal is clear, the rest of the planning becomes more concrete. If the aim is to relieve nerve compression, the records that matter are the ones that show that compression: recent MRI images and reports, any nerve conduction or electromyography studies, and a clear description of your symptoms and how they have changed over time. If the aim is broader, the team may need additional information before they can give a meaningful opinion.
The goal also shapes the questions you ask about timing. A patient whose symptoms are stable has time to gather records and seek a records-based opinion. A patient with new or worsening neurological symptoms — such as progressive weakness, difficulty walking, or loss of bladder or bowel control — needs prompt local assessment rather than overseas planning. That is not a reason to delay care; it is a reason to prioritise the right care first.
Finally, the goal affects how you judge any proposed plan. If a clinician cannot explain what the operation is intended to achieve, or if the stated goal does not match your main problem, that is a signal to ask more questions before committing to travel.
- Ask the team to write down the goal in one or two sentences.
- Ask which symptoms are expected to improve and which are not.
- Ask what would happen if you chose not to have surgery now.
A planning example: two patients, two different goals
Consider two hypothetical patients, both with lower back and leg symptoms. The first has clear imaging showing nerve compression at one level, leg pain that follows a nerve pattern, and no instability. The second has widespread back pain, minimal leg symptoms, and imaging that shows some narrowing but no clear nerve compression. These are not the same problem, and the same operation would not serve both.
For the first patient, the goal might be to relieve pressure on the affected nerve and improve leg symptoms. The records needed are focused: recent MRI, a clear symptom history, and any prior treatments tried. For the second patient, the goal is less clear, and the treating team may want to explore other explanations before considering surgery. That might mean a different specialist, additional assessment, or a period of non-surgical care.
This example is not medical advice. It illustrates why the treatment goal is the first question, not the last. If you cannot state your own goal in plain language, ask the clinical team to help you do so before you plan travel.
Records that help a China-based team assess the goal
A records-based opinion depends on the quality of the records. For lumbar decompression, the most useful items are usually the recent MRI images themselves, not only the written report, plus any relevant X-rays or CT scans. A clear timeline of symptoms — when they started, what makes them better or worse, and what treatments you have already tried — helps the team understand your situation.
It is also useful to include a short summary of your main question. Are you trying to find out whether decompression is appropriate at all? Whether a specific level is involved? Whether a fusion is also needed? The more specific your question, the more focused the opinion can be.
You do not need to send a complete medical archive at the first contact. A brief summary and the key imaging reports are enough to start. The team can then tell you what else is needed. Do not send passport numbers, payment details or a full medical history through an initial enquiry form.
- Recent MRI images and reports, if available.
- A short symptom timeline and treatments already tried.
- Your main question in one or two sentences.
Questions that change the next step
The answers to certain questions determine whether you plan travel, seek more records, or stay local. Ask the treating team directly: What is the goal of this operation for me? What are the alternatives? What happens if I wait? What are the risks and how are they managed? What does recovery involve, and what restrictions will I have?
Some of these answers depend on the individual hospital and surgeon. For example, the availability of a particular technique, the ward options, the language support, and the follow-up arrangements are all things to confirm with the specific provider. Do not assume that a general description of a procedure applies to every hospital in China.
If you are considering care in China, the first step is usually a free initial case review. That review checks the available diagnosis, records and your main question, identifies missing information and suggests a relevant next step. It is not a diagnosis or a promise of acceptance. The hospital decides suitability.
- What is the goal of surgery in my case?
- What are the alternatives, including non-surgical options?
- What records do you need to give a meaningful opinion?
- What would you need to confirm before I travel?
What decompression is not
Lumbar decompression is not a guarantee that all back pain will resolve. It is not a fusion, and it is not a treatment for every kind of spinal problem. It is also not a decision that can be made from imaging alone. The treating clinician needs to assess your symptoms, examination findings and goals.
New or worsening neurological symptoms — such as increasing weakness, numbness in the saddle area, or difficulty controlling bladder or bowel — require prompt local assessment. Do not delay that assessment to plan overseas care. Once the urgent question is addressed, you can return to planning if it is still appropriate.
Finally, a records-based opinion is not the same as a final decision. It can help you understand whether decompression is a reasonable option and what information is missing, but the operating surgeon and hospital make the final call after assessing you in person.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.