Why the scope of decompression is the decision to clarify
Lumbar decompression aims to relieve pressure on nerves in the lower spine, and surgery is considered according to symptoms and assessment. That short description hides the part that matters most for your decision: which levels, which side, and how much bone or tissue the surgeon plans to remove. Two patients with the same diagnosis label can be offered very different operations, and the label alone does not tell you what will actually be done.
This is why the useful conversation is about scope rather than about choosing a procedure from an article. Scope covers the intended target of the operation, the structures the surgeon expects to address, and the boundaries the surgeon intends to respect. It also covers what the surgeon does not plan to do. If you are gathering information before travelling to China, your goal is to arrive at a consultation able to ask specific questions about your own spine, not to select a technique in advance.
A related distinction is worth keeping clear. Decompression is not fusion. They are different operations with different purposes, and a discussion about relieving pressure on nerves is not the same as a discussion about stabilising the spine. If fusion has been mentioned to you, ask separately why it is being considered and how it relates to the decompression plan. Do not assume the two are interchangeable.
What your walking limitations and previous spine care tell the surgeon
The pattern of your symptoms is part of the assessment, not background colour. How far you can walk before symptoms force you to stop, whether leaning forward or sitting relieves them, and how your function has changed over time all help a clinician judge which levels are likely involved and how much the nerve compression is affecting you. When you write these details down, describe what you can and cannot do rather than using a single word such as mild or severe.
Previous spine care matters for the same reason. If you have had injections, physiotherapy, pain management, or earlier spine surgery, the treating team needs to know what was done, when, and what changed afterwards. A prior operation at the same level changes the anatomy the surgeon will encounter and can change what is technically reasonable. Bring whatever documentation you have rather than relying on memory alone.
You do not need to decide whether your history makes you a candidate. That judgement belongs to the treating clinician after assessment. Your job is to present the history accurately and to ask how it affects the proposed scope. If you have new or worsening severe neurological symptoms, such as loss of bladder or bowel control or rapidly progressing weakness, that needs prompt local assessment rather than overseas planning.
Questions that turn a general plan into a specific scope
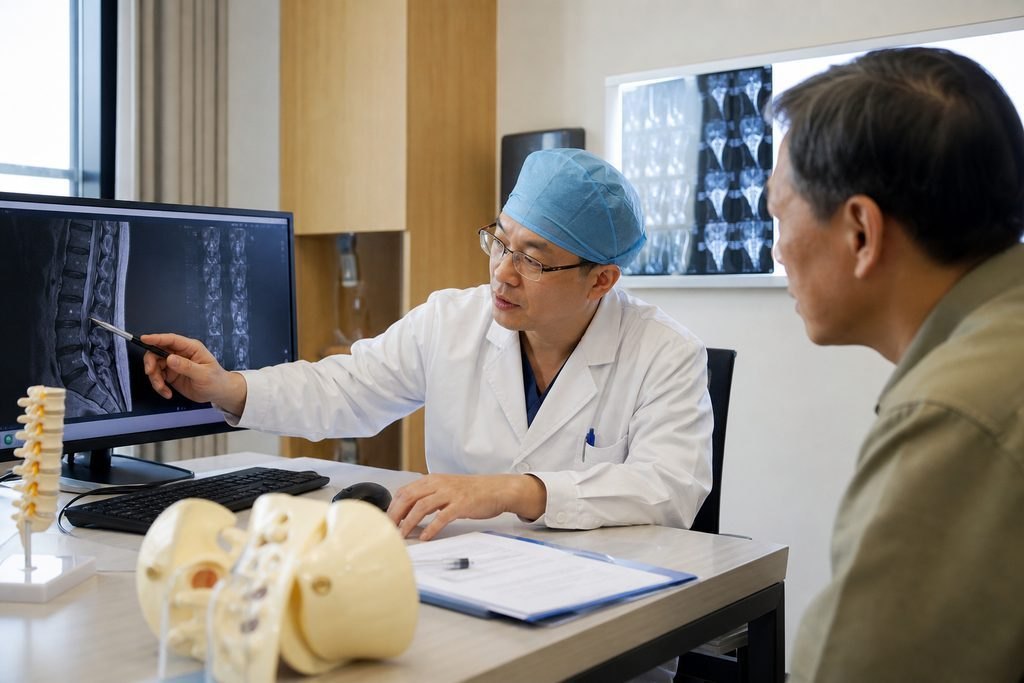
Ask the surgeon to walk you through the plan level by level. Which levels does the surgeon intend to decompress, and what is the evidence for including each one? Is the plan to address one side or both? What does the surgeon expect to find at each level, and how does that expectation connect to your imaging and your symptoms? These questions are answerable in a consultation and they convert a vague recommendation into something you can actually evaluate.
Ask what the surgeon does not plan to do. If a level is being left alone, why? If fusion is not planned, what would change that? If the surgeon is considering a minimally invasive route, what are the trade-offs compared with a more open approach in your specific case? You are not asking the surgeon to justify every textbook detail; you are asking which decisions are settled and which remain open.
Ask about uncertainty directly. A responsible clinician can discuss evidence-based expectations, including the possibility that some back pain persists after decompression and that no outcome is guaranteed. You can ask what the surgeon considers a good result for someone with your pattern of symptoms, and what would prompt a change of plan. If a question cannot be answered before further tests or an in-person examination, ask what specifically needs to be clarified and when.
Records that make the scope discussion concrete
The most useful records for this conversation are the ones that show your spine and your function over time. Recent MRI images and reports of the lumbar spine are central, because the surgeon needs to see the levels and the degree of narrowing rather than read a summary. If you have had CT or standing X-rays, include them. If you have had previous spine surgery, the operative notes and any post-operative imaging help the surgeon understand the current anatomy.
Alongside imaging, bring a short written summary of your symptoms: when they started, how they affect walking and standing, what you have tried, and what has helped or not helped. Include a list of your current medicines and relevant conditions, and note any allergies. If you have seen a neurologist or physiotherapist, their assessment notes can add useful functional detail.
You do not need to assemble a complete archive before making an initial enquiry. A brief summary of your diagnosis, main question and available records is enough to start. After first contact, you can be told how to share records securely. Ask the receiving clinician which specific items would change the scope discussion, rather than assuming every document is equally important.
How to use a records-based opinion without treating it as a decision
A records-based opinion can help you understand how a specialist interprets your imaging and history, and it can prepare you to ask better questions. It is not the same as an in-person assessment, and it does not establish final eligibility, hospital acceptance or a definitive operative plan. Treat it as a structured way to clarify the scope question before you travel, not as a substitute for the consultation where the surgeon examines you.
If you request this kind of review, be clear about what you want answered. Ask whether the reviewer can comment on the levels likely involved, the relationship between your imaging and your walking limitations, and what additional information would be needed for a firmer view. Ask the reviewer to state the limits of a records-only assessment in your case. That keeps the opinion useful without overstating what it can conclude.
An initial enquiry with ChinaSpecialistCare is free and does not require buying a proxy consultation. The team can check the available diagnosis, records and your main question, identify missing information and suggest a relevant next step. This is not a diagnosis or a promise of acceptance. If a proxy consultation or multidisciplinary review is relevant to a complex case, it can be discussed separately, and you can decide whether it is worth it for your situation.
Preparing for the consultation in China and the next step
Before you travel, confirm what the appointment actually is. Ask whether you are being scheduled for a consultation, for further imaging, or for a surgical planning discussion, and who you will see. Ask what you should bring in original or translated form and whether an interpreter will be present. These are practical questions for the named hospital or provider, and the answers can differ between institutions, so confirm them rather than assuming a standard arrangement.
During the consultation, keep the scope conversation focused. Ask the surgeon to state the planned levels, the intended approach, what is being left alone and why, and what remains uncertain. Ask what the recovery and follow-up expectations are for the plan discussed, understanding that these are individual and not guaranteed. If you feel the plan has changed from what you expected, ask what new information drove the change.
For the next step, gather a short summary of your diagnosis, your walking limitations, your previous spine care and your main question, and send it through the enquiry form, email or WhatsApp. The team can then indicate what is missing and which appointment route may fit. You can review the lumbar decompression reference for general context, but the scope decision for your spine belongs to the treating clinician after assessment.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.