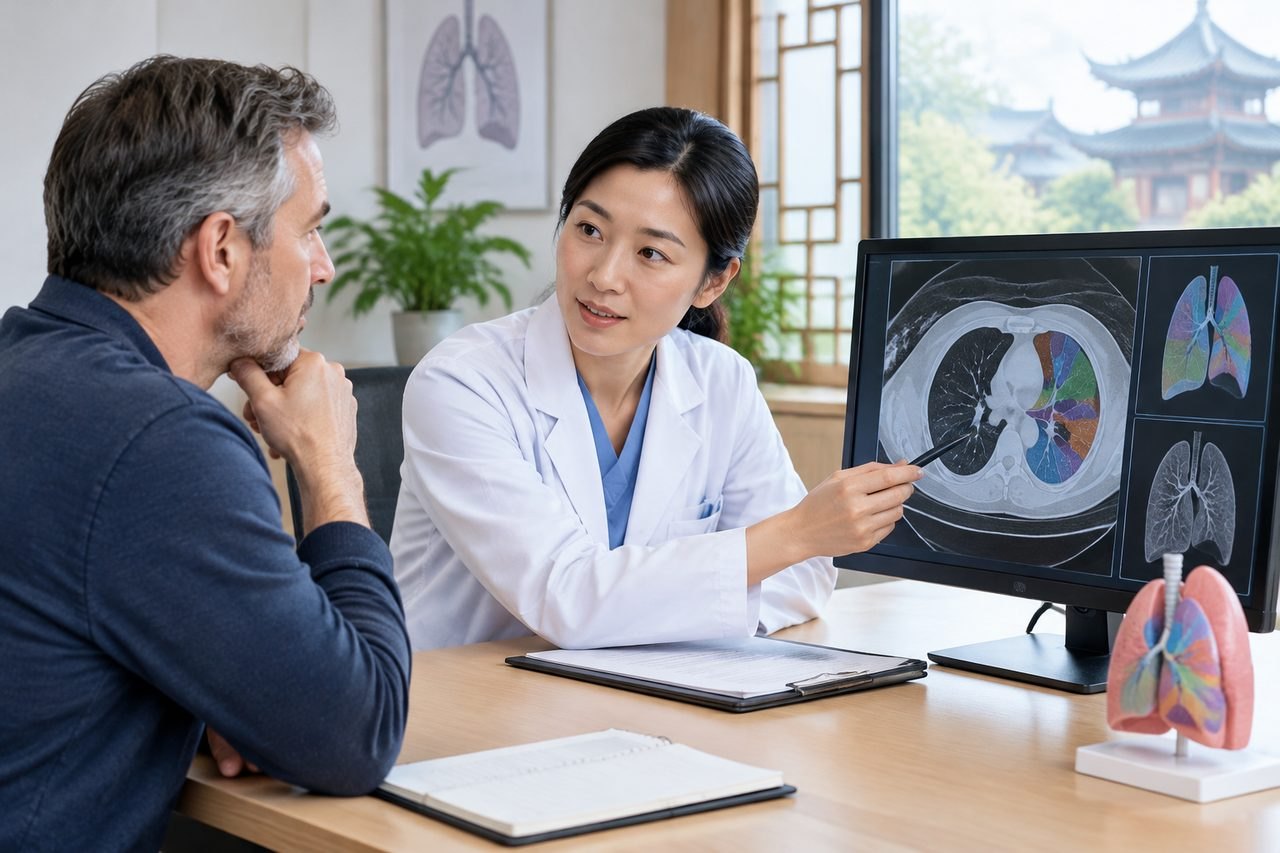
Why the position of the lesion changes the segmentectomy decision
A lung segmentectomy removes a segment rather than a whole lobe. That single sentence hides the part that matters most to an overseas patient: not every lesion sits neatly inside one segment. The lungs are divided into lobes, and each lobe is divided into bronchopulmonary segments, each with its own blood supply and airway branch. A surgeon planning a segmentectomy has to decide whether the lesion can be taken out with a clear margin while leaving the rest of the lobe working.
That is why lesion location is not background detail. It is one of the first things a thoracic team checks when deciding whether a segmentectomy is appropriate for a particular patient, or whether a larger or different operation would be safer. The suitable extent of surgery requires individual assessment, and location is central to that assessment.
For an international patient, this has a practical consequence. Sending a diagnosis label alone, such as 'lung nodule' or 'suspected early lung cancer', is not enough for anyone to comment usefully. The team needs to see where the lesion is, how it relates to the surrounding segments, and what the imaging shows about its edges. Without that, any opinion is provisional at best.
What the surgical team is actually looking at on your scans
When a thoracic surgeon reviews imaging for a possible segmentectomy, several location-related questions come up together. Is the lesion confined to one segment, or does it cross into a neighbouring segment? How close is it to the segment's bronchus and pulmonary vessels? Is there enough normal lung around it to allow a margin? Does the lesion sit near the pleural surface, or deep inside the lobe?
These are not abstract. A lesion sitting at the boundary between two segments may push the surgeon toward removing more than one segment, or toward a different operation. A lesion close to a major vessel may change how the operation is approached. A lesion deep in the lobe may be harder to reach with a limited resection than one nearer the surface.
This is also where the difference between a segmentectomy and a wedge resection becomes relevant. They are not the same operation. A wedge resection removes a non-anatomical piece of lung; a segmentectomy follows the segment's own anatomical boundaries. Whether one or the other is suitable depends on the lesion and the patient, and that judgement belongs to the treating team, not to a remote reader of a report.
If you are gathering records for a China enquiry, the imaging itself matters more than a short summary of it. Ask the hospital that performed the scan how the images can be shared in a usable format, and whether the radiology report describes the lesion's segment. If the report does not mention segment location, that is a question to raise rather than a gap to fill with guesswork.
The records that let a China team assess location properly
A useful records package for a segmentectomy enquiry is built around the imaging and the clinical context, not around a long list of unrelated documents. The chest CT images, ideally on disc or through a secure image-sharing route, are the core item. The radiology report that accompanies them helps, but it does not replace the images themselves.
Alongside the imaging, the treating team will want to understand the clinical picture: what led to the scan, whether there have been previous scans to compare, whether a biopsy has been done and what it showed, and what other significant health conditions the patient has. Lung function information, if it has been measured, is often relevant because it speaks to how much lung the patient can afford to lose.
It is reasonable to ask the receiving hospital what it needs before you send anything. Different hospitals may have different preferences for image format, report language and record translation. Rather than assume a universal checklist, ask the specific hospital or coordination team what format it can accept and whether translated reports are needed.
One boundary is worth stating plainly. A records-based review can help a specialist understand the case and discuss options, but it does not establish final eligibility for surgery. Suitability is decided after the treating team has assessed the patient, the imaging and the clinical context together. An initial enquiry is a starting point, not a commitment to operate.
Questions to ask before agreeing to a segmentectomy plan
The most useful thing an overseas patient can do is arrive at the consultation with specific questions rather than a general request for 'the best option'. The answers will tell you whether the plan is built on a clear understanding of the lesion's location.
Ask why a segmentectomy is being considered rather than a lobectomy or a wedge resection. Ask how the team has confirmed that the lesion sits within the segment being removed, and what margin they expect around it. Ask what would change the plan, for example if the lesion turns out to cross a segment boundary or if the frozen section during surgery shows something different from the biopsy.
Ask how the remaining lung will be monitored afterwards, and what surveillance imaging the team recommends. Ask what the alternatives are, including not operating immediately, and what the trade-offs are in this specific case. Ask who will make the final decision about the extent of surgery, and whether that decision might be made during the operation rather than before it.
These questions are not a challenge to the surgeon. They are how a patient understands whether the recommendation fits their situation. A team that can answer them clearly is giving you the information you need to decide whether to proceed in China or elsewhere.
How location affects the operation and the recovery conversation
Where the lesion sits also shapes what the operation involves and what the recovery conversation looks like. A segment in the outer part of a lobe may be reachable through a minimally invasive approach, while a more central lesion may need a different plan. The number of segments removed, and whether the operation stays limited, depends on the anatomy in front of the surgeon.
This is why recovery timelines cannot be promised in advance from a distance. The treating team will explain what to expect based on the actual operation performed, the patient's lung function and general health, and how the early postoperative course goes. Any fixed number of days offered before surgery is a planning estimate, not a guarantee.
For international patients, this also affects travel planning. The length of stay, the timing of follow-up imaging and when it is safe to fly are all decisions for the treating team after they have seen the patient and the operation is done. Ask the hospital how it usually structures follow-up for international patients, and what it needs from you to arrange it.
One practical point: if you are considering care in China, the relevant reference page for this operation is the lung segmentectomy procedure page, which explains the service in more detail. Use it alongside the questions above rather than instead of them.
What to confirm with the hospital before you commit
Before committing to travel and treatment, confirm the practical and clinical points that only the receiving hospital can answer. Ask what the written treatment plan includes and what remains undecided until the team sees you in person. Ask whether the plan is based on the imaging you have already sent or whether further imaging will be requested in China.
Ask how the hospital handles communication with international patients, including whether an interpreter is available for consultations and consent discussions. Ask what the hospital's own fees cover and what is arranged separately, so that you are comparing like with like. Ask what happens if the intraoperative findings change the planned extent of surgery, and how that decision would be communicated to you or your family.
These are not bureaucratic details. They are the difference between a plan you understand and a plan you are guessing at. A hospital that answers them directly is giving you a realistic picture of what care in China would involve for this specific lesion in this specific patient.
If you would like help identifying a suitable thoracic team and preparing your records for review, you can start with a brief summary through the enquiry form. An initial enquiry is free, and it does not commit you to a proxy consultation or to treatment. The hospital decides whether a segmentectomy is suitable after it has assessed your case.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.