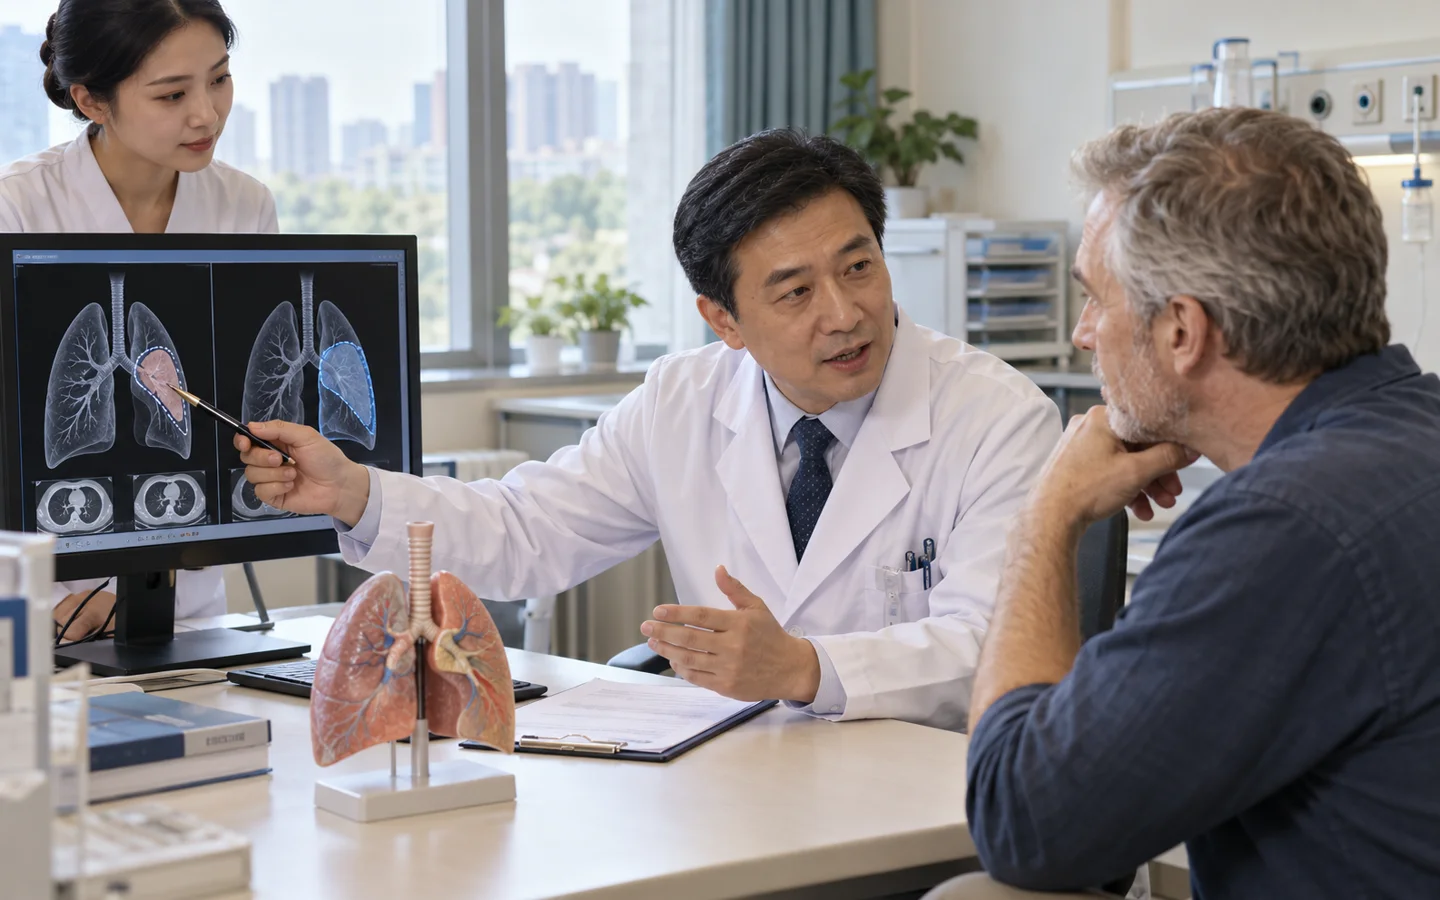
Segmentectomy removes a defined bronchovascular segment rather than a whole lobe
The surgeon divides the segmental artery, vein and bronchus and separates the targeted lung segment. It is more extensive than a wedge resection but preserves more lung than lobectomy.
For cancer, tumor size, depth, location, margin distance and lymph-node assessment determine whether segmentectomy is oncologically appropriate. Technical feasibility varies considerably between segments.
Ask how the planned margin will be measured and whether findings during surgery could require lobectomy.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about anatomical lung segmentectomy.
- Selected small peripheral early-stage lung cancer.
- A lesion requiring diagnosis and anatomical removal in a patient with limited reserve.
- Multiple lesions where lung preservation is important.
- A localized benign or metastatic lesion suited to segmental anatomy.
What the specialist team must confirm
Review includes high-resolution CT with thin slices, lesion depth and relation to segmental vessels and bronchi, PET or tissue diagnosis, nodal staging, pulmonary reserve and the possibility of adequate margins without crossing into an adjacent segment.
Key points for this treatment
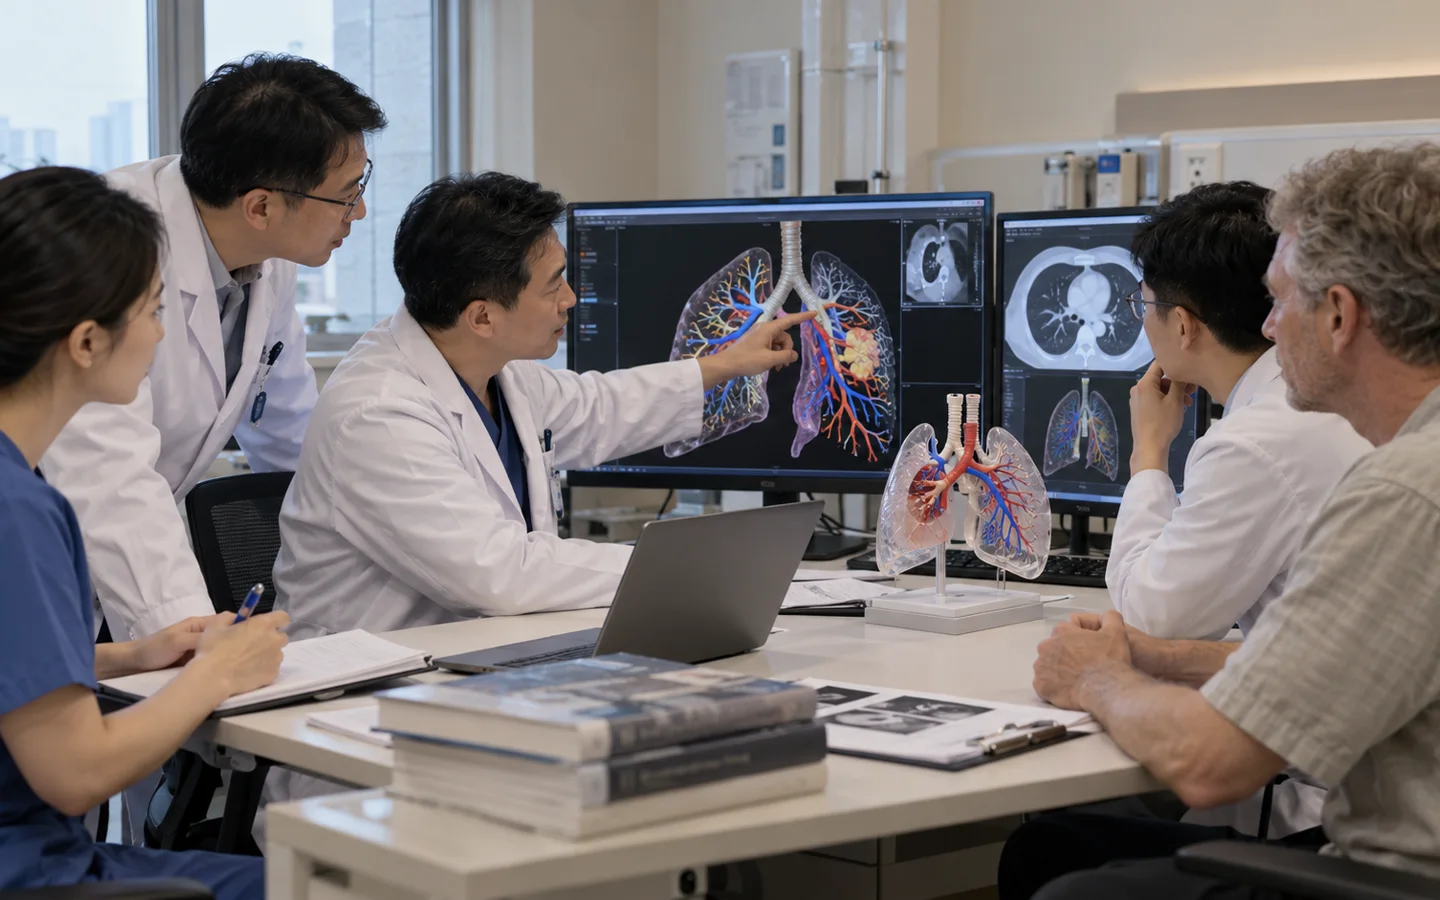
From precise localization to lung-preserving resection
A segmentectomy is chosen when it can provide the necessary margin and staging while preserving useful parenchyma.
Recovery resembles other anatomical lung resections
Drains, air leak, lung expansion, pain control and walking are monitored. Complex intersegmental planes can produce prolonged air leak despite the smaller volume removed.
Final pathology confirms margin and nodal status. Surveillance and any additional treatment follow the diagnosis rather than the incision size.

Risks, limits and realistic expectations
Risks include bleeding, air leak, pneumonia, incomplete margin, missed nodal disease, torsion of remaining lung, conversion to lobectomy or open surgery, recurrence and death.
New severe breathlessness, high fever, coughing blood, fainting or rapidly increasing chest pain requires urgent local assessment.