What Your Old Scans Already Answer
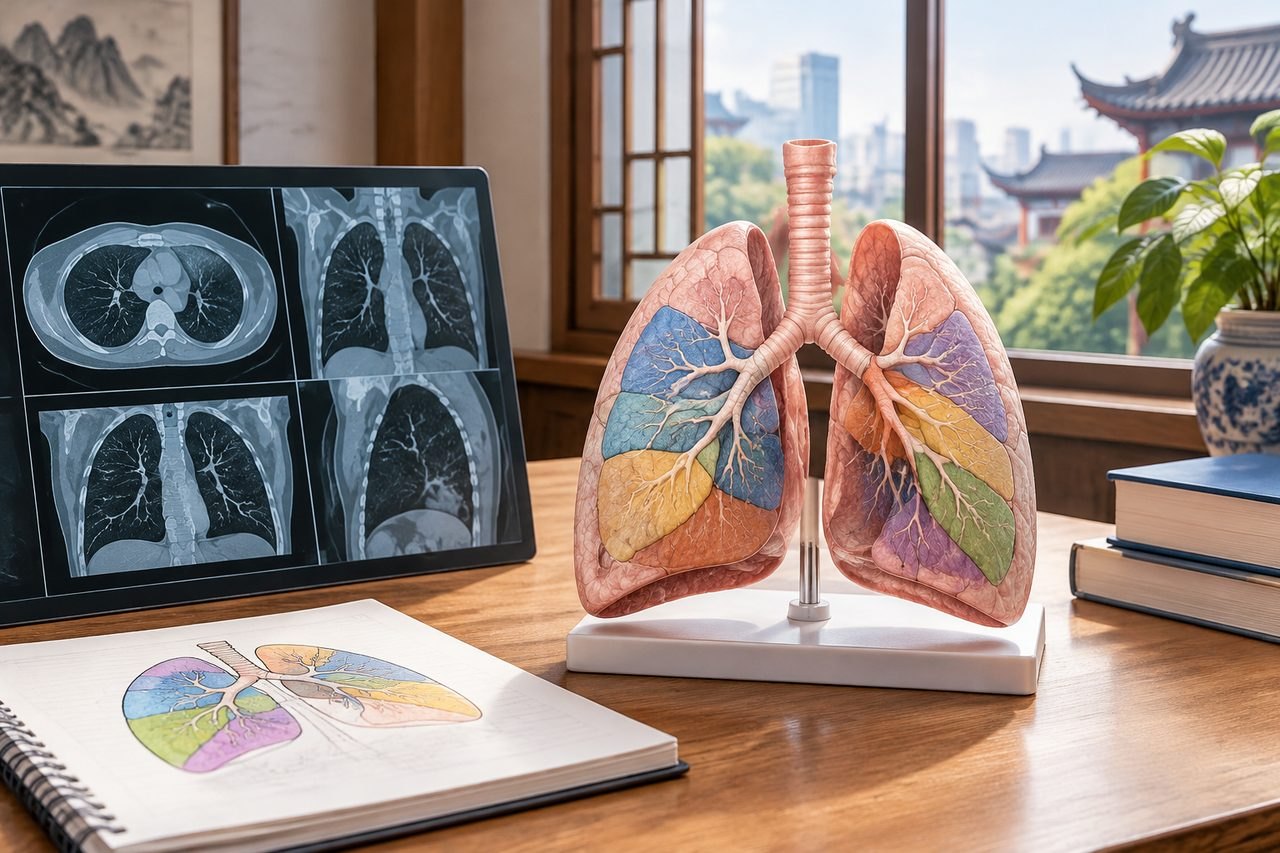
When you send earlier imaging, you are not starting from zero. Those images carry information a thoracic team can use to understand the lesion's location, its size at the time of each scan, and whether it changed between scans. That history is often the reason a segmentectomy is being discussed at all rather than a larger operation or continued observation.
A lung segmentectomy removes a segment rather than a whole lobe. That distinction matters because the segment is a smaller anatomical unit, and the suitable extent of surgery requires individual assessment. Your old imaging helps the team see which segment is involved and how close the lesion sits to nearby structures, but it does not by itself settle whether segmentectomy is appropriate for you.
It is worth being precise about what you are sending. Reports alone tell the team what someone else concluded. The actual image files let a new reader look at the same pictures and form an independent view. If you can obtain both, send both, and note the dates clearly so the sequence is not confused.
One practical point: old imaging does not become less useful because it is old. A scan from a year ago may be exactly what shows whether a finding is stable, growing, or changing in character. Do not assume the team only wants the most recent study.
What a New Assessment Is Actually For
A new assessment is not simply a repeat of what you already have. It is meant to answer the questions your existing records leave open. The most important of these is usually the surgical question: why segmentectomy, and what would confirm that the planned extent is right for this lesion in this lung.
That question has several parts. Where exactly is the lesion relative to the segment boundaries? How much functional lung would remain? Are there other findings that change the picture? These are not questions a patient can answer from a report, and they are not questions a coordinator should answer either. They belong to the treating clinical team.
A new assessment may also address what happens after surgery. Surveillance is part of the plan, not an afterthought. If the team is considering segmentectomy, you should be able to ask how follow-up imaging would be scheduled, what would be looked for, and who would be responsible for that monitoring once you return home.
This is where a records-based opinion and a formal hospital assessment differ. A remote review can look at what you send and comment on it. It cannot examine you, cannot order or interpret tests performed locally to the hospital's own standard, and cannot give final procedural clearance. Treat any remote view as a step towards a decision, not the decision itself.
Why the Word Segmentectomy Needs Unpacking
Patients sometimes use segmentectomy and wedge resection as if they were the same operation. They are not. A wedge resection removes a piece of lung without following the segment's anatomical boundaries. A segmentectomy follows those boundaries. The distinction affects how the operation is planned and what tissue is removed.
This matters for your questions. If you ask only whether you need surgery, you may not learn which operation is being proposed or why. If you ask why segmentectomy rather than a wedge resection or a lobectomy, you are asking the question that actually shapes the plan. The answer depends on the lesion, the lung, and the individual assessment the team makes.
Be cautious about drawing conclusions from size alone. A lesion's dimensions on a scan do not by themselves establish whether segmentectomy is suitable, and they do not establish that outcomes are equivalent to other operations. Those are clinical judgements, and they should come from the team assessing you, not from a general article.
Similarly, do not assume that a smaller operation automatically means preserved lung function in your case. That is a reasonable hope, but it is not a guarantee, and it is not something this article can promise. Ask the team what they expect for you specifically, and ask what uncertainty remains.
Questions That Move the Decision Forward
The most useful thing you can do before committing to travel is to ask a small number of precise questions and write down the answers. Vague reassurance is less helpful than a clear statement of what is known and what is not.
Ask why segmentectomy is being considered in your case, and what alternatives the team would weigh. Ask how the surgical scope would be confirmed, and whether any further imaging or testing is needed before that can be settled. Ask what the surveillance plan would look like afterwards, including how often and by what method.
Ask who would make the final decision about suitability, and what would happen if the assessment concluded that a different operation, or no operation, was more appropriate. A team that can answer this clearly is telling you something useful about how it works.
If you are dealing with a hospital in China, ask how the assessment would be arranged, what records it needs, and what the written plan would include. Do not assume a particular sequence of visits or a particular document set. Ask the named provider what its process actually is.
Records, Language and the Practical Side
For an overseas patient, the practical side of a new assessment is mostly about records and communication. You will want your imaging in a format the receiving team can read, your reports translated if needed, and a clear summary of your main question. A short summary at first contact is enough; you do not need to send a complete archive before anyone has looked at it.
Language arrangements are worth confirming rather than assuming. Ask whether interpretation is available for consultations, who provides it, and whether it is included in any quoted coordination service. These are questions for the specific provider, not things to infer from general expectations about care in China.
Cost is a separate matter and depends on what the assessment involves. Rather than guessing at figures, ask the hospital what its written estimate covers and what remains undecided at the point of quoting. Coordination fees, where you use them, are separate from hospital charges, and travel costs are separate again.
If your symptoms worsen or you develop new problems, that takes priority over an overseas enquiry. Seek local care rather than waiting for a remote review to be completed.
What This Assessment Cannot Tell You
It is worth being honest about limits. A new assessment, however thorough, does not guarantee an outcome. It does not promise that surgery will proceed, that a particular surgeon will operate, or that recovery will follow a set course. Those are not things anyone can promise in advance.
It also does not replace your own clinicians at home, and it does not mean you should delay necessary local care while an overseas enquiry is in progress. If your local team has advised urgent action, follow that advice.
What a well-run assessment can do is give you a clearer picture of the surgical question, the reasoning behind the proposed extent of surgery, and the follow-up plan. That is a meaningful step, and it is a reasonable thing to ask for.
If you would like to start, send a brief summary of your situation and your main question. An initial enquiry is free and does not commit you to anything. The hospital, not this service, decides whether segmentectomy is suitable for you.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.