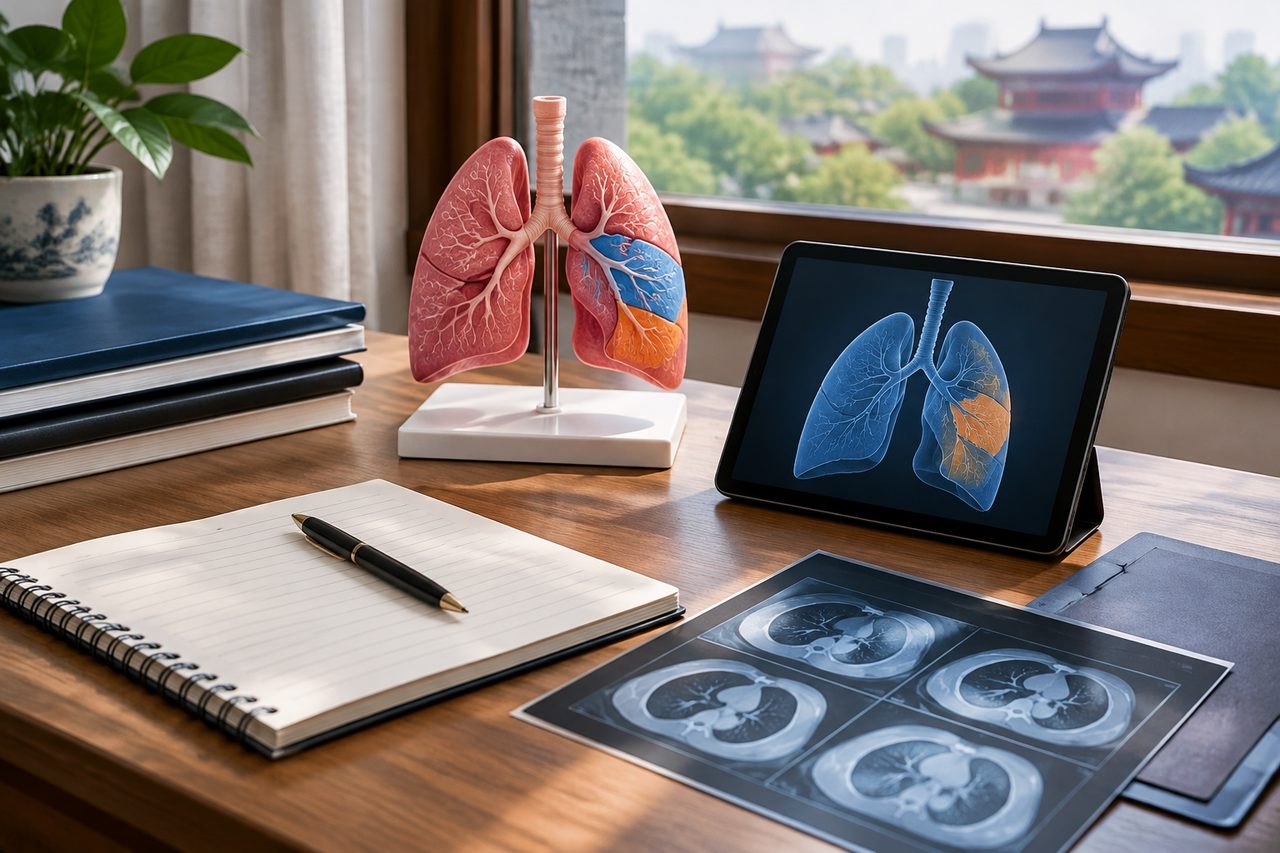
What resection scope actually means in a segmentectomy
Resection scope is the physical boundary of the tissue the surgeon intends to remove. In a segmentectomy, that boundary is a bronchopulmonary segment rather than a full lobe. The segment is a defined anatomical unit with its own blood supply and airway, which is why the operation can be described precisely rather than as a general 'smaller' resection.
This distinction matters because 'less tissue removed' is not automatically the same as 'the right operation for this lesion'. The suitable extent of surgery requires individual assessment. Two patients with apparently similar nodules can end up with different plans once the lesion's position, its relationship to nearby vessels and airways, and the remaining lung are reviewed together.
A common misunderstanding is to treat segmentectomy and wedge resection as interchangeable. They are not the same procedure. A wedge resection takes a non-anatomical piece of lung; a segmentectomy follows a named anatomical segment. If a hospital's plan uses one term while your records describe the other, clarify which operation is actually proposed before you plan anything around it.
Why the lesion's location drives the decision
Where the lesion sits is central to whether a segment can be removed cleanly. A lesion near the outer part of a segment may be approachable within that segment. A lesion close to a segmental boundary, a major vessel or a central airway raises a different question: can the intended margin be achieved without compromising structures that must be preserved?
This is the point at which scope stops being an abstract preference and becomes a surgical judgement. The team has to weigh how much lung can be safely left behind against whether the planned boundary gives an adequate margin around the lesion. Those two goals can pull in opposite directions, and the balance is specific to your anatomy.
For an overseas patient, the practical consequence is that a decision cannot be made from a report summary alone. The imaging that shows the lesion in relation to segmental anatomy is what allows a surgeon to say whether a segmentectomy is feasible, and if so, which segment or segments are involved. Ask which images the team needs to make that call, and whether your existing scans are adequate for it.
The lung assessment that sits alongside the lesion
Scope is not decided from the lesion in isolation. The team also needs to understand the lung that will remain. Lung function testing and other respiratory assessment help show what reserve you have, which informs how much tissue can reasonably be removed. This is why a plan that looks straightforward on imaging may still change after breathing tests.
If you have existing lung disease, previous lung surgery, or a history that affects breathing, say so early. It changes the calculation. It also gives the team a reason to look more carefully at whether a segment-sparing approach is appropriate for you specifically, rather than assuming it is preferable because it removes less.
Do not assume that a segmentectomy guarantees preserved lung function, and do not assume it offers the same cancer outcomes as a lobectomy in every situation. Those are clinical questions for the treating team, answered against your own staging and pathology. What you can do is make sure the assessment inputs are complete so the scope discussion is based on your actual lung, not a generic assumption.
Questions that clarify the planned margin and approach
The most useful conversation is not 'can I have a segmentectomy?' but 'what exactly is being removed, and why that boundary?' That framing gets you specific answers instead of a general reassurance. It also surfaces disagreements early, before travel arrangements are built around an assumption.
Ask which segment or segments are planned, and what margin the team intends around the lesion. Ask whether the approach would be minimally invasive or open, and whether that choice is fixed or could change during the operation. Ask what would make the team convert to a larger resection, and how that decision would be communicated.
A short checklist can help you keep the answers straight, because these points are easy to lose in a long consultation.
- Which segment or segments are planned for removal, and what margin is intended around the lesion?
- Which imaging and lung-function records were used to define that scope?
- Is the planned surgical approach fixed, or could it change intraoperatively?
- What findings would lead the team to extend the resection, and who decides?
- What is the plan for confirming the pathology of the removed tissue?
- What surveillance would follow, and who would arrange it?
Records that make a scope discussion possible from abroad
A remote scope discussion is only as good as the material it rests on. The team needs imaging that shows the lesion in relation to segmental anatomy, not just a text report describing it. Where available, the actual scan files are more useful than a summary, because the surgeon can review the anatomy directly.
Pathology records matter too. If a biopsy has already been taken, the report helps establish what is being treated. If no tissue diagnosis exists yet, that is a question to raise rather than assume, because it affects how the team frames the operation and what it expects to confirm afterwards.
Lung-function results, relevant past imaging, and a clear list of your current medications and allergies round out the picture. You do not need to send a complete archive at first contact. A brief summary of the diagnosis and your main question is enough to start, and the team can then tell you which specific documents it needs. Ask how records should be shared and whether translation is required for the documents you hold.
Confirming scope and follow-up with the treating team in China
Once you have a proposed plan, treat the stated scope as something to confirm in writing rather than something to infer. Ask which hospital department would perform the operation, who would lead the surgical discussion, and how the final scope is documented before you commit to arrangements. Hospital acceptance and surgical suitability are decisions for the treating hospital and its clinicians, not something an enquiry can settle.
Follow-up is part of the same conversation. Ask what surveillance the team would recommend after a segmentectomy, how it would be scheduled, and whether it could be coordinated with clinicians in your home country. If you intend to return home after surgery, raise that early so the team can explain what it can and cannot arrange across borders.
For the China side of the planning, the relevant reference is the lung segmentectomy procedure page, which sets out the operation itself. An initial enquiry through ChinaSpecialistCare is free and non-clinical: a short summary of your diagnosis, records and main question is enough for the team to identify what is missing and suggest the relevant next step. You do not need to purchase a proxy consultation to ask a first question, and no enquiry establishes eligibility, hospital acceptance or a treatment outcome.
The practical next step is to gather the imaging, pathology and lung-function records you already hold, write down the two or three questions above that matter most to you, and send a brief summary so the scope discussion can begin with the material a surgeon actually needs.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.