Why previous eye procedures change a macular hole assessment
A macular hole affects the central retina. The supplied NHS source notes that surgery may involve an eye gas bubble, and flying is prohibited while that bubble remains. That single fact already shows why a previous procedure history matters: if you have had recent eye surgery, or if a gas bubble is still present, the timing and safety of any new assessment or travel plan can be affected.
But the deeper reason is clinical. A macular hole is not assessed in isolation. The treating ophthalmologist needs to know what the retina looked like before, what was done, and what has changed since. Previous cataract surgery, vitrectomy, retinal detachment repair, laser treatment or intravitreal injections can all influence how the current macular hole is interpreted and what options remain.
This is why a generic first-visit guide is not enough. A first-visit guide tells you how to start from zero. Your situation is different: you are adding a new question to an existing eye history. The hospital needs the old context to answer the new question.
What to document about each previous eye procedure
For every previous eye procedure, aim to provide four things: what was done, when it was done, why it was done, and what the result was. The 'what' should be as specific as your records allow. 'Eye surgery' is less useful than 'vitrectomy for retinal detachment' or 'cataract surgery with intraocular lens implant'. If you do not know the exact name, say what you were told and include the operative report if you have it.
The 'when' matters because recent surgery and long-past surgery carry different implications. The 'why' matters because a procedure done for trauma, for example, tells a different story from one done for a degenerative condition. The 'result' is often the hardest part: did the procedure restore vision, stabilise it, or leave a residual problem? Did it create a new issue, such as a persistent macular hole, a epiretinal membrane, or a change in the lens?
If you have had more than one procedure, present them in order. A simple chronological list is easier for a clinician to follow than a narrative that jumps between dates. You do not need to write a long essay. A short table or bullet list with dates, procedure names and outcomes is often more useful.
- Date of each procedure, even if approximate.
- Name of the procedure as stated in your records.
- Reason it was performed.
- Outcome: vision change, complications, or remaining symptoms.
- Any implant, gas, silicone oil or device still present.
The retinal findings that matter most: OCT and current imaging
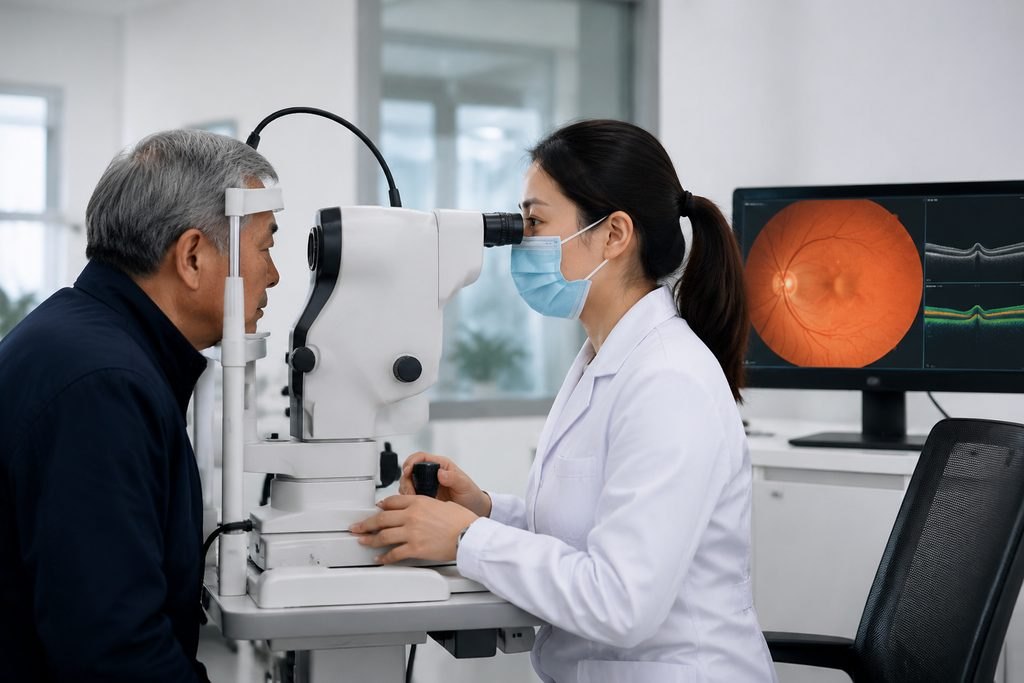
For a macular hole, the single most important recent test is usually an optical coherence tomography (OCT) scan. OCT shows the cross-sectional structure of the retina and can demonstrate whether a full-thickness macular hole is present, how large it is, and whether there are associated features such as vitreomacular traction or a epiretinal membrane.
If you have had previous eye procedures, the OCT history is valuable. A current OCT alone tells the treating team what your retina looks like now. A series of OCT scans over time can show whether the hole is new, whether it has changed, and whether a previous surgery altered the retinal architecture. If you can obtain previous OCT images or reports, include them.
Other retinal findings may also be relevant. Fundus photographs, fluorescein angiography, and visual field tests can all contribute. The key is not to send everything you have ever collected, but to send the imaging that directly relates to the macular hole and the previous procedures. If you are unsure what is relevant, ask the receiving hospital what it wants before you send a large file.
How to explain the result of a previous procedure without overstating it
Patients often describe a previous procedure as 'successful' or 'failed', but those words can mean different things. A cataract operation may be considered successful because the lens was removed, even if vision did not improve as much as hoped. A retinal detachment repair may be considered successful because the retina is attached, even if a macular hole later developed.
A more useful approach is to describe what you were told and what you experience. For example: 'I was told the retina was reattached. My vision is still blurry in the centre. A recent scan shows a macular hole.' This gives the clinician both the clinical fact and your functional experience without forcing a judgement.
If you do not know whether a previous procedure is relevant to the macular hole, say so. The treating ophthalmologist can decide. Your job is to provide the information, not to interpret it. This is especially important if you have had surgery in another country and the records are in a different language. A clear summary in English, alongside the original records, helps the team understand your history.
Post-procedure care questions to raise before travel
If you are considering macular hole surgery in China, the post-procedure plan is part of the decision, not an afterthought. The NHS source states that flying is prohibited while an eye gas bubble remains. That means your travel plans may need to change depending on what the surgeon uses. You should ask the treating team directly about this, because the answer depends on the specific procedure and the specific gas or agent used.
You should also ask about positioning. Some macular hole surgeries require the patient to maintain a certain head position after surgery. The duration and exact position are clinical decisions. Do not assume a fixed number of days based on what you have read online. Ask the hospital what it recommends for your case and how that interacts with your travel and accommodation plans.
Other practical questions include: What follow-up appointments will I need, and can any of them be done locally? What symptoms should prompt me to seek urgent care? What restrictions apply to lifting, bending or flying? These are not administrative details. They affect your safety and your ability to return home.
What the hospital needs to decide suitability, and your next step
The hospital, not the patient or a coordinator, decides whether macular hole surgery is suitable. That decision depends on the current retinal findings, the previous procedure history, your general health, and the treating surgeon's assessment. A records-based review can help clarify whether your case is worth travelling for, but it does not guarantee acceptance or a particular outcome.
When you contact a hospital or a coordination service, start with a brief summary: your main question, the date of your most recent eye assessment, and the key previous procedures. You do not need to send a complete archive at first contact. After the initial enquiry, the team can tell you what additional records or imaging it needs.
For care in China, you can begin with a free initial case review. This is not a diagnosis or a promise of acceptance. It is a way to check whether your records are sufficient and what the relevant next step might be. If you already have a confirmed macular hole and a history of previous eye procedures, say that clearly. The more precisely you describe the sequence, the more useful the response will be.
You can also read more about macular surgery in China to understand the general service context before you decide whether to proceed with an enquiry.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.