What the two teams actually need from each other
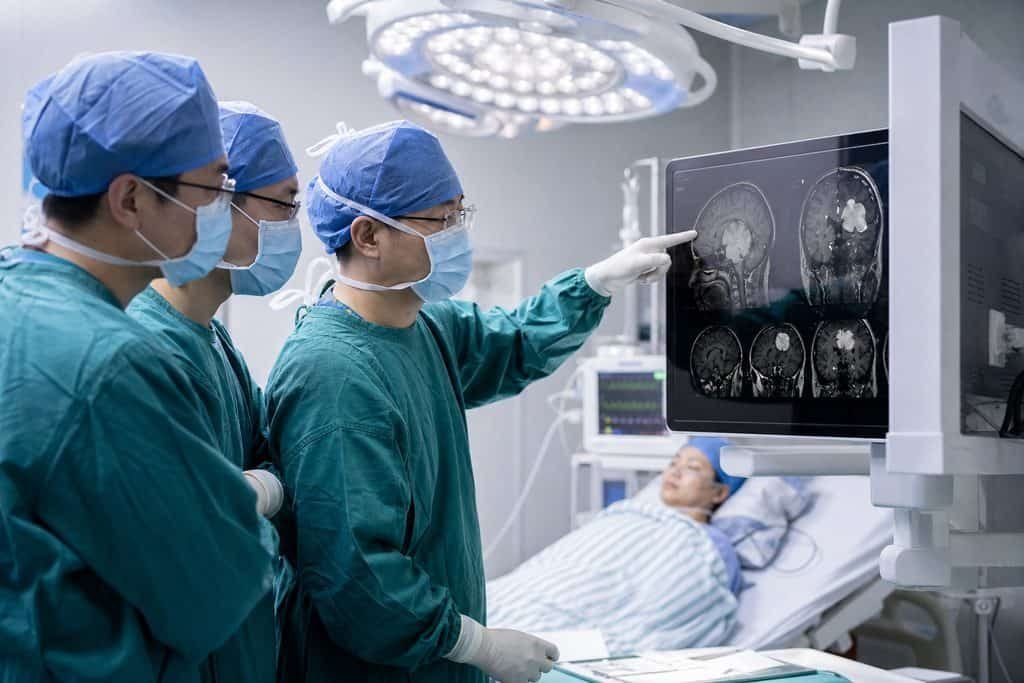
A meningioma is not managed from a written summary alone. Management depends on its location, symptoms and clinical assessment, and surgery is not the only possible management approach. That means the Chinese neurosurgery team will want to compare the actual images, not just the radiologist's report, because tumour location and growth history are read from the scans themselves. Your home team, in turn, needs to know what the Chinese team is proposing and why, so it can comment on whether that fits the history it has followed.
The exchange is therefore not a single document. It is a set of source records plus a set of questions. The source records let the Chinese team form its own view. The questions let your home team respond to that view rather than to a general description of meningioma surgery.
It helps to think about what each side can and cannot do from a distance. Your home team has the clinical history, the examinations it has performed and its own reading of the scans. The Chinese team has neurosurgical expertise and, once the files arrive, the same images. Neither side can examine the patient for the other. That is why the exchange has to be specific: vague summaries leave both teams guessing, while dated images and clear questions let each side work from the same material.
A frequent failure in this kind of exchange is not a lack of goodwill. It is that each side sends what is easiest to send rather than what the other side needs. A radiology report without the images, a discharge summary without the operative note, or a list of medicines without doses can all look like a complete file while leaving the key questions unanswered. Deciding in advance what to send, and asking the receiving team to confirm what it still needs, closes that gap before it becomes a delay.
There is also a sequencing question. The Chinese team cannot form a useful view until it has the images and the history, and your home team cannot comment meaningfully until it knows what the Chinese team is proposing. Trying to run both at once tends to produce two half-answers. A cleaner order is: collect the records, send them with a short cover note, ask the Chinese team for a written view, then pass that view to your home team for comment.
Finally, keep the purpose in view. The aim is not to have two teams agree for its own sake, but to give you a clear picture of what is being considered, what the alternatives are, and what remains uncertain. A records exchange that produces a specific written opinion, with the reasoning and the open questions set out, has done its job even if the two teams do not reach the same conclusion.
Which prior scans and treatments to ask about first
Before anything is sent, ask both teams which prior scans and treatments they want to compare. This is a question, not a fixed list, because the answer depends on what has already been done and what the Chinese team needs to judge growth over time.
For imaging, the useful items are usually the original scan files rather than only the reports, and the dates of each scan so that growth history can be assessed. Ask whether the Chinese team wants the earliest available scan, the most recent one, or both. Ask whether it needs the radiology reports as well, and in what language.
For treatment history, ask whether the team wants records of previous surgery, radiotherapy, or any other treatment, together with pathology reports if a tissue sample was taken. Ask whether it needs the operative notes or only the discharge summary. Ask whether it wants current medicines listed, and whether it needs the names and doses as written by the prescriber.
For symptoms, ask what the team wants described: headaches, vision changes, seizures, weakness, or other neurological symptoms, and how far back the description should go. A short timeline of when symptoms started and how they changed is often more useful than a long narrative.
How the Chinese team's view should be framed back to your home team
When the Chinese neurosurgery team reviews the records, its reply should be specific enough for your home team to respond to. Ask for the tumour location as the Chinese team sees it, the growth history it has inferred from the scans, and whether it is considering surgery, observation, or further assessment. Ask what additional information it still needs before it can give a firmer view.
This matters because a records-based opinion is not the same as a final treatment decision. The Chinese team may say that surgery is one option, that observation is reasonable, or that more imaging or a specialist examination is needed. Your home team can then comment on whether that matches what it has seen and what it would recommend locally.
Ask the Chinese team to put its reasoning in writing, including the alternatives it considered. That gives your home team something concrete to agree with, question, or correct. It also reduces the risk that a brief reply is read as a commitment to operate.
Who sends what, and in which direction
A common failure is that each side waits for the other. Decide early who will collect the imaging files, who will translate the reports if needed, and who will send them. If your home team is sending records to China, ask it to include a short cover note listing what is enclosed and what is missing. If the Chinese team is sending a reply back, ask for it in a form your home team can read, and ask whether an English version is available.
Ask both sides who the named contact is. A named contact on each side makes it possible to follow up a missing file or an unanswered question without starting over. Ask whether the Chinese team will communicate through you, through your home team, or both, and whether it prefers email or another channel.
Keep a simple log of what was sent, to whom, and on what date. This is not bureaucracy; it is how you notice that a scan was never received or that a question was answered only in general terms.
Questions to put to both teams before any decision
The point of the exchange is to reach a shared understanding, not to collect documents. Put the same core questions to both teams and compare the answers.
Ask the Chinese team: based on the records, is surgery being considered, and what would make surgery the preferred option rather than observation? What are the alternatives, and what are the main risks and uncertainties in your case? What further records or tests would change your view?
Ask your home team: does the Chinese team's reading of the scans match yours? If surgery were done in China, what would you want to know about the plan, the follow-up, and the records you would need afterwards? Would you recommend any further assessment before travel?
Ask both: who will be responsible for follow-up after any treatment, and how will records be shared back? A clear answer to that question prevents a gap later.
What a records exchange does not establish
Sending records and receiving a reply does not confirm that surgery will go ahead, that a particular hospital will accept the case, or that travel is appropriate. The hospital decides suitability after its own assessment, and a records-based opinion is one step in that process, not the final decision. No outcome can be guaranteed.
If symptoms are worsening, or if there is new weakness, vision change, confusion, or a seizure, that needs urgent local assessment rather than an overseas enquiry. Do not delay necessary local care while records are being exchanged.
If you want help with the practical side, ChinaSpecialistCare can assist with collecting and forwarding records, interpretation, and requesting a specialist appointment at a Chinese neurosurgery service. This is non-clinical coordination; the treating hospital and licensed clinicians decide suitability, and an initial enquiry is free. You can start with a short summary and ask what records are needed next.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.