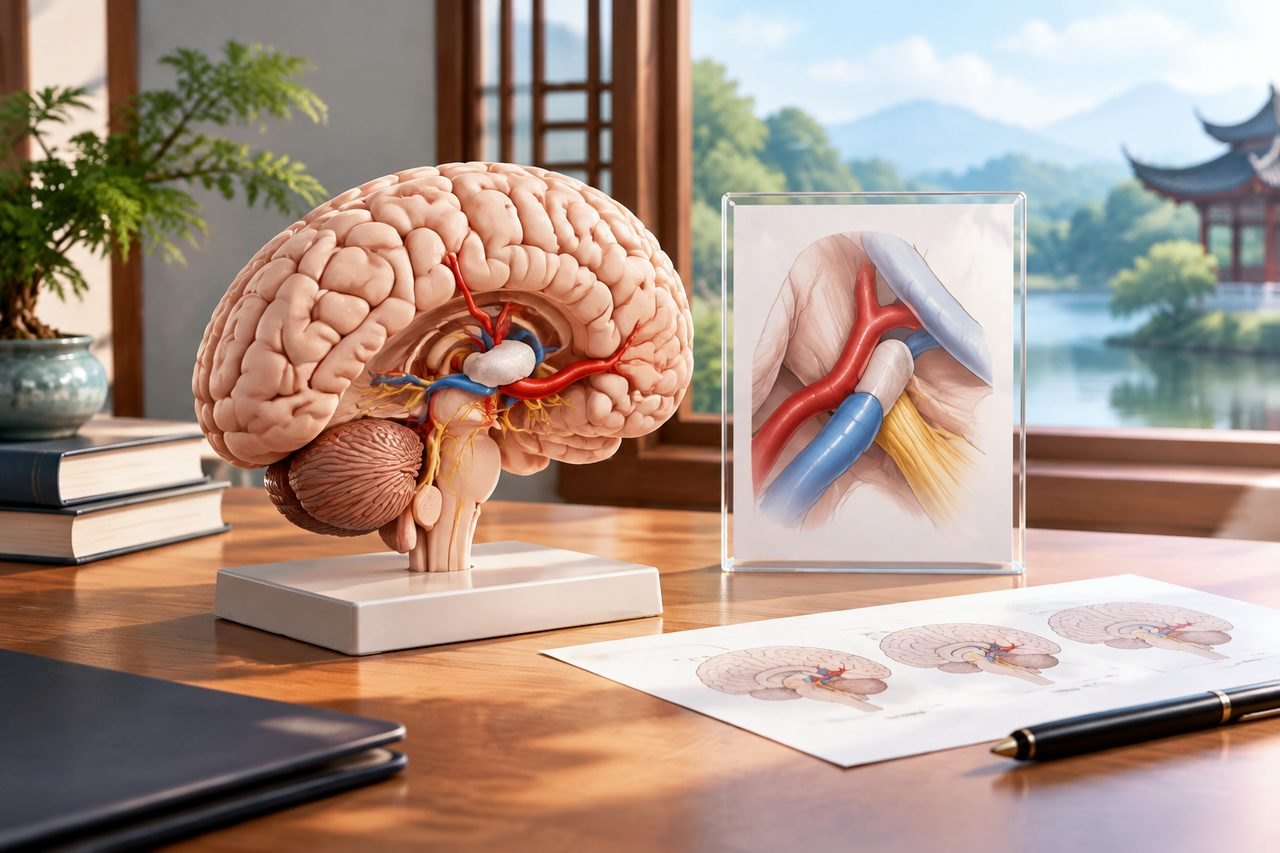
What microvascular decompression is designed to change
The operation targets a specific mechanical problem: a blood vessel pressing on the trigeminal nerve. In selected patients, moving that vessel away can reduce the pain signals the nerve produces. The NHS describes microvascular decompression as a treatment option for trigeminal neuralgia that can relieve this pressure in selected patients.
That wording matters. The treatment is not designed to remove every kind of facial pain, and it does not repair nerve damage that has another cause. If your pain comes from a different diagnosis, or if imaging does not show a vessel in a position that fits your symptoms, the operation may not be the right tool. The team, not the patient, makes that judgement after reviewing the full picture.
A useful way to think about it: the operation addresses one proposed mechanism. It does not automatically address medication side effects, dental or sinus sources of pain, or pain that persists after the nerve has already changed. Ask the surgeon to state, in plain terms, which problem they believe the operation will change and which problems will remain.
Why the diagnosis must be confirmed before surgery is discussed
Trigeminal neuralgia is a clinical diagnosis supported by imaging, not a diagnosis made by a scan alone. A vessel seen near the nerve on MRI does not by itself prove that the vessel is causing the pain. Many people have vascular contact without trigeminal neuralgia, and some people with classic symptoms have imaging that is less clear.
This is why the first question for any team is not 'can you operate?' but 'how have you confirmed the diagnosis in my case?' A careful answer will refer to your pain history, its pattern and triggers, your neurological examination, your response to previous treatments and the imaging findings together. If any of those pieces are missing, the team should say so rather than proceed on a single scan.
For an overseas patient, this step is also where records matter most. A short summary of when the pain started, which side of the face is affected, what triggers it, which medicines have been tried and at what doses, and what previous procedures or injections you have had gives the team something concrete to work with. You do not need to send a complete archive at first contact. A focused summary plus the key imaging report is enough for an initial view of whether a specialist review is worth arranging.
How a team compares microvascular decompression with other options
Microvascular decompression is one option among several for trigeminal neuralgia. Medicines, other surgical procedures and less invasive treatments may also be considered, and the balance depends on your age, general health, the pattern of your pain, previous treatments and what the imaging shows. The operation is not automatically the first or best choice for every patient, and a team that presents it that way has skipped a step.
A useful conversation with the treating team covers three comparisons. First, what is expected from continuing or adjusting medication in your situation, and what monitoring that requires. Second, what the alternatives to microvascular decompression would involve, including their own risks and what they can and cannot achieve. Third, why the team favours one route over another for you specifically, rather than in general.
You are not asking the team to guarantee an outcome. You are asking them to explain their reasoning so you can weigh it. If the answer is only 'this is what we do', that is a signal to ask for the comparison in writing or to seek a records-based opinion before committing to travel.
The comparison also has a practical side. Some alternatives are repeatable or adjustable; an operation is not. Some carry their own risks that matter more for one patient than another. Ask the team to set out what each route would mean for you over the next months, not only what happens on the day of a procedure.
A second opinion does not have to mean a second hospital. It can mean asking the same team to explain the reasoning behind its recommendation in a form you can read at home, and then deciding whether you find it convincing. If the reasoning is thin, that is useful information before you book flights.
If you are comparing hospitals in China, ask each one the same three questions in the same words. Comparable answers are far more useful than brochures, and they let you judge whether a team has actually engaged with your records or is simply describing its usual practice.
What the operation cannot promise
No surgeon can promise that microvascular decompression will leave you pain-free, and no responsible team will offer that. The operation can relieve pressure on the nerve in selected patients, but pain may persist, may return later, or may require further treatment. There are also surgical risks, including risks to hearing, facial sensation and balance, which the treating team must explain in relation to your anatomy.
It is equally important not to treat the operation as a solution to problems it was never meant to solve. It does not replace the need to investigate other causes of facial pain. It does not remove the need for follow-up. It does not mean you can stop prescribed medication on your own; any change to medicines is a decision for the clinician managing that treatment.
If you are considering care in China, the honest framing is this: the hospital decides whether you are a suitable candidate, and that decision depends on records and examination that cannot be completed from a distance. An initial enquiry or a records-based opinion can clarify whether a review is worthwhile, but it does not establish that surgery will be offered or performed.
Individual differences that change the plan
Two patients with the same diagnosis can receive different recommendations. Age and general health affect surgical risk. The duration and pattern of pain affect how the nerve has been affected. Previous treatments, including injections or other operations, change what the team is working with. Imaging findings vary in how clearly they show a vessel in a position that fits the symptoms.
Because of this, general information about microvascular decompression is a starting point, not a plan. The questions that matter are specific to you: how does the team confirm the diagnosis in your case, what alternatives do they consider reasonable, what does the postoperative review involve, and what would make them advise against surgery? Ask for answers that refer to your records rather than to the procedure in general.
For international patients, it also helps to ask how the team handles communication and follow-up across borders. Who will explain the plan and in what language? What records will they need before a decision? What happens if the review shows that another route is more appropriate? These are practical questions, and clear answers make the decision easier.
Planning postoperative review and the next step
Postoperative review is part of the treatment, not an afterthought. Before you travel, ask how the team plans to assess your pain after surgery, what follow-up appointments are expected, how those appointments would work if you return home, and who to contact if symptoms change. The answers depend on the hospital and your situation, so treat any general schedule as something to confirm in writing rather than assume.
You should also ask what the written plan and estimate include, what remains undecided until after examination, and which costs are paid to the hospital rather than to a coordination service. ChinaSpecialistCare can help you organise records, request a specialist appointment and coordinate practical arrangements, but the treating hospital and its clinicians decide suitability, treatment and follow-up.
A sensible next step is to send a short summary of your diagnosis, previous treatment and imaging reports, along with your main question. An initial case review is free and does not commit you to a proxy consultation or to travelling. If you want a records-based specialist opinion before deciding, that can be discussed separately. Start with the summary and the question you most need answered.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.