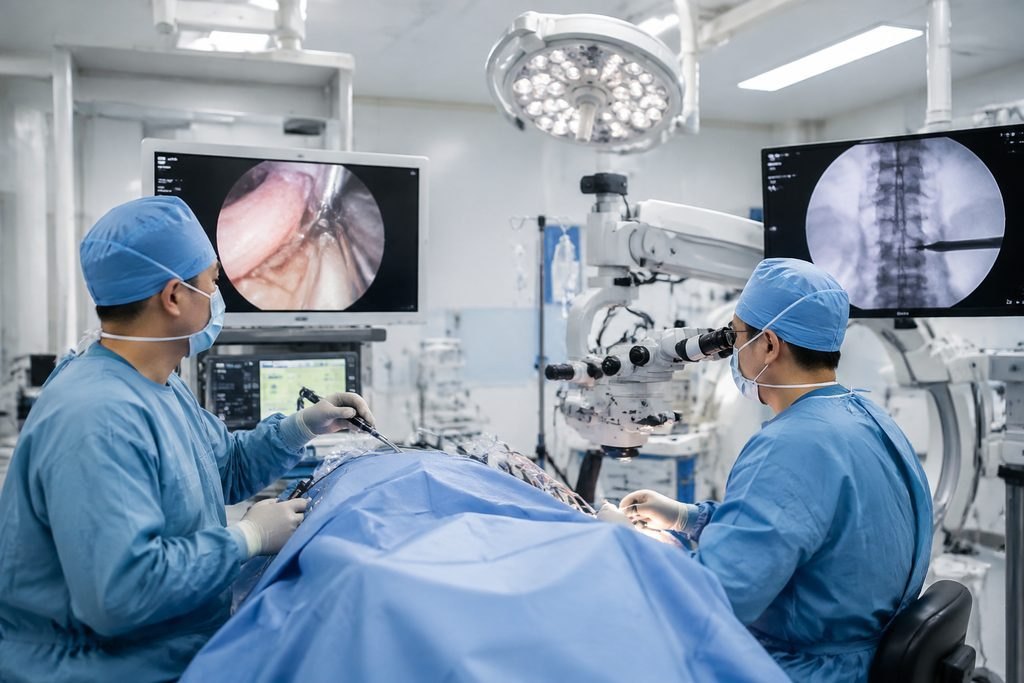
Why the first in-person discussion matters more than the technique label
Minimally invasive describes an approach, not a single operation. The same label can cover different spinal procedures, including decompression or fusion. That means agreeing to "minimally invasive spine surgery" without confirming the actual operation and levels leaves the most important decisions unresolved.
For an overseas patient, the first in-person meeting is the point where imaging, symptoms and prior treatment are reviewed together. It is also the point where you can ask whether the proposed approach is appropriate for your specific problem, what alternatives exist, and what the surgeon expects to achieve. A productive discussion produces a named operation, named levels, a records list and a follow-up plan. It does not need to produce a final decision on the spot.
The technique label also tells you nothing about who the operation is for. A minimally invasive approach may be considered for one spinal problem and not another, and the same label can describe procedures with very different goals. Before you travel, it helps to know whether the question you are bringing is about the approach itself or about the underlying diagnosis and its treatment options. Those are different conversations, and the second one is usually the one that decides the plan.
If your symptoms are worsening, seek local urgent care rather than waiting for an overseas appointment. An enquiry or planned consultation should not delay necessary assessment.
A first in-person discussion is a working meeting, not a ceremony. You are there to test whether the proposed plan matches your problem, to hear what remains uncertain, and to leave with a short list of what happens next. If the meeting produces only a technique name and a price range, the most useful questions are still unanswered.
That is why the preparation described below is built around decisions rather than around collecting general information. Each question is meant to close a specific gap: which operation, which levels, which records, which rehabilitation, which review, and which parts of the plan are still open.
The three questions that should anchor the conversation
First, ask the surgeon to state the exact proposed operation in plain terms. Is this a decompression, a fusion, or another procedure? What structure is being addressed, and what is the goal? If the answer stays at the level of "minimally invasive spine surgery," ask for the specific procedure name and what it involves.
Second, ask which spinal levels are involved. The level or levels matter because they determine the approach, the structures at risk and the rehabilitation implications. If imaging has been reviewed, ask the surgeon to point to the relevant levels and explain how they connect to your symptoms.
Third, ask why this approach is being considered for you. Minimally invasive techniques can be used for different operations, but the source material does not establish a universal recovery advantage, same-day discharge or that a small incision makes surgery minor. Ask what the expected benefits and limitations are in your case, and what the alternatives would involve.
Write these three questions down before the visit. A short written list keeps the discussion focused and gives you a record of what was said.
What records to bring and what to ask the surgeon to review
Bring the imaging you already have, including the actual images or discs where possible, not only the written reports. Reports summarize; the surgeon may need to see the images to assess levels and plan an approach. Bring any prior operative notes, discharge summaries and relevant consultation letters.
Ask the surgeon which records are essential for the decision and which are helpful but not critical. If something is missing, ask whether it changes the plan or whether the discussion can proceed with what you have. Do not assume you must delay clinical assessment until a file is complete; instead, ask what the treating team needs and what can be clarified later.
If your records are in another language, ask whether a translated summary is needed and who can provide it. If you need interpretation during the visit, confirm the arrangement in advance. A coordinator can help with practical interpretation and appointment logistics, but the clinical assessment and suitability decision belong to the treating surgeon and hospital.
Rehabilitation, review and the questions patients often forget
Ask what rehabilitation will involve after the proposed operation. Will you need physiotherapy, and if so, what kind and for how long? Ask whether the surgeon has specific restrictions or precautions, and whether these differ from what a local physiotherapist might recommend. The receiving physiotherapist or clinician can assess you independently; the goal is to understand the plan, not to assume only one team can manage your recovery.
Ask how and when the surgical team wants to review you after the operation. If you plan to return home, ask what follow-up can be done locally and what information the surgeon would want sent back. Confirm who is responsible for arranging that review and what records should be shared.
Ask what the surgeon considers a good outcome for your case, and what would prompt a change in plan. Ask about the risks and uncertainties that matter for your situation. You can ask a clinician about evidence-based risk estimates and what they mean for you; no estimate guarantees an individual result.
Finally, ask what you should do if symptoms change before the planned procedure. Get a clear contact route and a clear threshold for seeking urgent care.
Confirming the practical and financial scope before you commit
Ask the hospital or provider for a written estimate or quote that states what is included, what is excluded and what remains undecided. Do not rely on a verbal range. If the quote does not specify whether imaging, ward type, implants, medicines or follow-up visits are included, ask for that in writing.
Ask whether the surgeon you are meeting is the person who would perform the operation, and whether the plan could change after further review. Hospital acceptance and surgical suitability are decisions for the treating hospital and licensed clinicians, not for a coordination service.
If you are considering a records-based opinion before travelling, understand its scope. A remote review can help clarify whether an in-person discussion is worthwhile, but it does not establish final eligibility, hospital acceptance or a guaranteed treatment plan. A proxy consultation is optional and not a prerequisite for every appointment.
Keep provider charges, coordination fees and travel costs separate in your planning. Ask each party what their fee covers and when payment is due.
How to prepare a one-page question sheet for the visit
A one-page sheet keeps the discussion on track and gives you something to write answers on. Structure it around the decisions you need to make, not around general curiosity.
At the top, write your main symptoms and what you want to change. Below that, list the exact operation and levels you understand are proposed. Then add your questions about records, rehabilitation, review and risks. Leave space for the surgeon's answers and for anything that remains unclear.
After the visit, review your notes while the discussion is fresh. If an answer was vague, write down the follow-up question and send it through the hospital's contact route. If you need help arranging an appointment, interpretation or a records review, ChinaSpecialistCare can assist with non-clinical coordination; the clinical decisions remain with the treating team.
A free initial enquiry is enough to start. Share a brief summary of your situation and your main question, and the team can explain what information would help and what the next practical step would be.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.