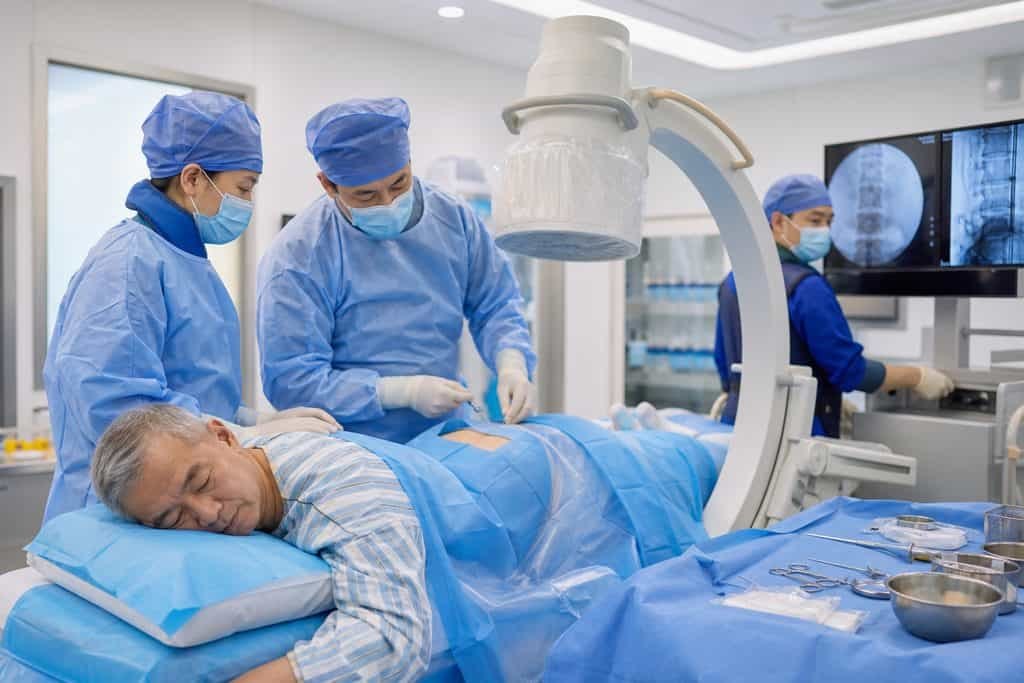
Start with the exact operation, not the technique label
"Minimally invasive" tells you how a surgeon may reach the spine. It does not tell you what will be done once there. The same approach can be used for a decompression, where pressure on a nerve is relieved, or for a fusion, where two or more vertebrae are stabilised. Those are different operations with different goals, different risks and different recovery demands.
This matters because a conversation about "minimally invasive surgery" can sound reassuring while leaving the important decisions unspoken. A small access route does not make an operation minor. The underlying procedure still carries the risks of that procedure, and those risks need to be discussed in their own right.
Before you compare hospitals or ask about travel, ask for the proposed operation in plain terms: the name of the procedure, the spinal level or levels involved, and whether the plan is decompression, fusion, or something else. If the answer is vague, that is the first thing to clarify, not the last.
Questions that separate a real risk discussion from a sales answer
A useful risk conversation is specific to you, your imaging and your symptoms. General statements such as "minimally invasive is safer" do not answer the question. You are entitled to ask what the treating surgeon sees as the main risks in your case, how those risks compare with the alternative options, and what would happen if the planned approach cannot be completed as intended.
It also helps to ask about conversion. Sometimes a surgeon begins with a minimally invasive approach and needs to change to a larger open procedure during the operation. Ask whether that is a possibility in your case, why it might happen, and how it would be handled. This is not a sign of a bad plan; it is part of understanding the plan honestly.
Ask, too, about the evidence behind the recommendation. You can request that the surgeon explain the expected benefit, the uncertainty around it, and what is known about outcomes for people with a problem like yours. A clinician can discuss evidence-based risk and benefit estimates without guaranteeing your individual result. If you want numbers, ask for them and ask what they are based on.
Finally, ask who will perform the operation and what happens after discharge. The name of the surgeon, the team involved and the follow-up arrangement are reasonable questions. You do not need to accept a plan simply because it is described as minimally invasive.
- What is the exact name of the proposed operation, and which spinal levels are involved?
- What are the main risks for me specifically, and how do they compare with the alternatives?
- Could the approach change to open surgery during the operation, and why?
- What is the expected benefit, and what is uncertain about it?
- Who will perform the operation, and how will follow-up be arranged?
Alternatives: what else could be considered, and why
Alternatives are not only other operations. They include non-surgical management, a different type of operation, a different spinal level, or waiting with monitoring if that is clinically reasonable. Ask the surgeon to walk through the realistic options for your situation and to explain why the proposed plan is preferred over each one.
If a surgeon recommends minimally invasive decompression, ask how that compares with a conventional open decompression in your case. If fusion is proposed, ask whether decompression alone could be sufficient, and what the trade-offs would be. These are legitimate questions, and a surgeon should be able to answer them without defensiveness.
It is also fair to ask what would happen if you chose not to have surgery now. Sometimes the answer is that symptoms are likely to persist or worsen; sometimes it is that a period of non-surgical treatment is reasonable first. Either way, the answer helps you understand the decision you are actually making.
You may want a second opinion before committing. A records-based review can give you another clinician's perspective on the same imaging and history. It does not replace an in-person assessment, and it does not guarantee acceptance or a particular outcome, but it can help you ask better questions.
What the surgeon needs from you to answer properly
A surgeon cannot give you a meaningful risk and alternatives discussion without your actual records. At minimum, that usually means your recent MRI or CT images and reports, any X-rays, your symptom history, and a note of treatments you have already tried. If you have had previous spine surgery, the operative notes are important.
When you send records for an overseas enquiry, a brief summary is enough to start. You do not need to send a complete medical archive or payment details in a first message. The clinical team can tell you what else it needs once it understands your main question.
Ask the hospital or coordinator what format it prefers for imaging, whether reports need translation, and whether the surgeon wants to see the images themselves or only the written report. These practical details affect how quickly a real clinical discussion can happen.
If some records are missing, say so rather than waiting until everything is perfect. The clinician can tell you whether the missing item changes the assessment or whether the available information is sufficient for a preliminary view.
Recovery, rehabilitation and follow-up: ask before you travel
Recovery after spine surgery depends on the operation, the levels involved, your general health and your home circumstances. There is no universal recovery advantage simply because an approach is minimally invasive, and a small incision does not mean the operation is minor. Ask what your expected recovery would involve in practical terms: activity restrictions, wound care, pain management and when you could travel home.
Rehabilitation is part of the plan, not an afterthought. Ask whether physiotherapy is recommended, when it would start, and what it would involve. The receiving physiotherapist or clinician will make their own assessment, so ask how the plan would be handed over to a therapist in your home country.
Follow-up matters too. Ask how many reviews are expected, whether they can be done remotely or with a local clinician, and what would prompt an earlier return. If you are considering surgery in China as an overseas patient, clarify how the hospital would communicate with your local doctor and what records you would take home.
Do not assume a fixed timeline for returning to work, flying or driving. Those are clinical decisions based on your recovery, and the treating team should tell you what to expect and what to confirm before you travel.
Planning the enquiry without committing to a procedure
An initial enquiry is free and does not require you to buy a proxy consultation. You can start with a short summary of your diagnosis, your main question and your available records. The team can then suggest the relevant next step, which might be a specialist appointment, a records-based opinion, or simply clarification of what is missing.
If you want a surgeon in China to review your case, a specialist appointment can be arranged with timing and visit preparation. Hospital consultation fees are separate from any coordination service. A proxy consultation, where a doctor takes your records to a specialist while you remain at home, is optional and not a prerequisite for every appointment or operation.
For a complex or cross-specialty spine problem, a multidisciplinary review involving more than one specialty may be suggested. The scope and fee would be agreed first. None of these steps promises hospital acceptance, a particular surgeon or a clinical outcome; the treating hospital decides suitability.
Keep your questions written down before any consultation. Ask for the exact proposed operation and levels, the main risks in your case, the realistic alternatives, and the rehabilitation and follow-up plan. If an answer is unclear, ask again. A good clinical discussion should leave you better informed, not pressured.
When you are ready, you can share a brief summary through the enquiry form, email or WhatsApp. The team will explain how to send records after first contact. Do not send passport numbers, card details or a complete medical archive in that first message.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.