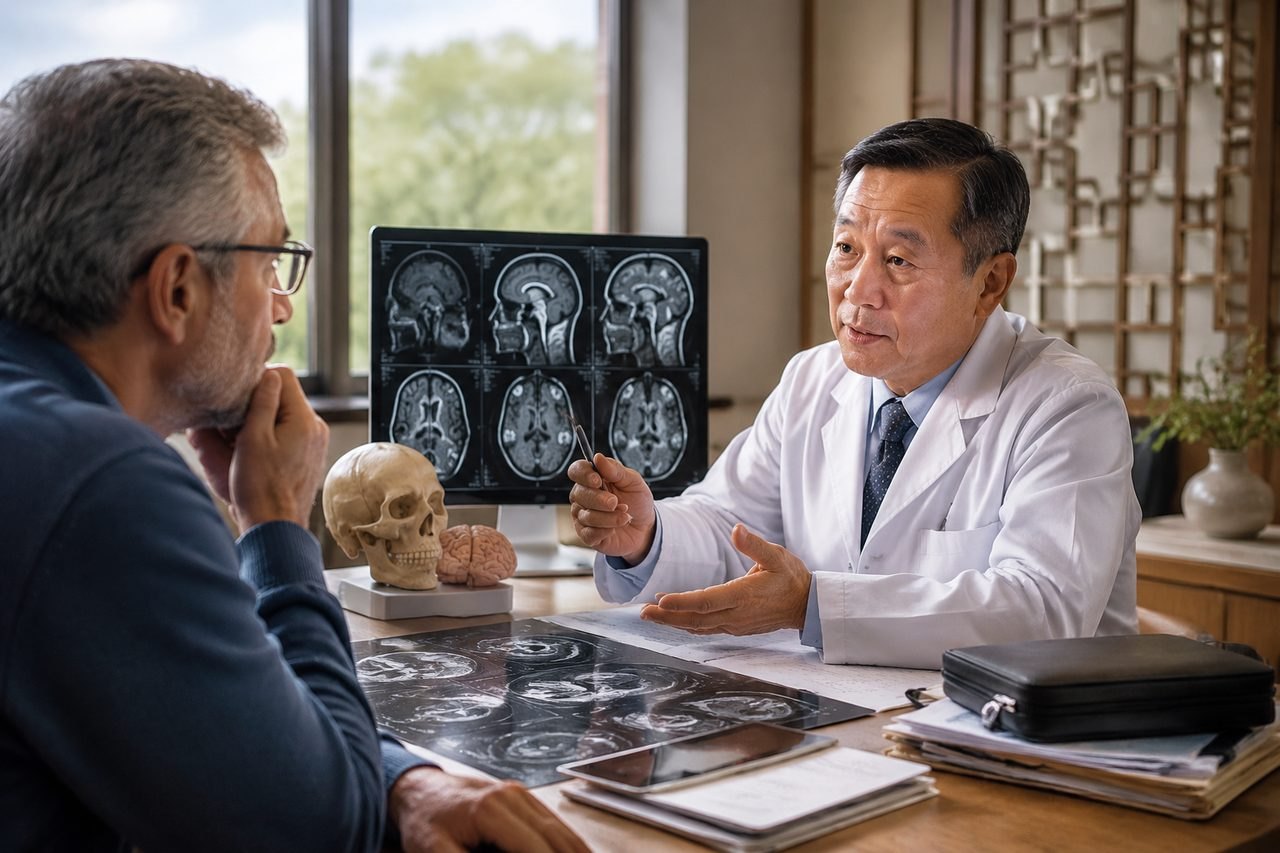
Why the diagnosis question comes before the MVD question
Microvascular decompression is a procedure that can relieve pressure from blood vessels on the trigeminal nerve in selected patients. That single sentence contains two limits that matter for your planning. First, it is for selected patients, not everyone with facial pain. Second, it addresses pressure on the trigeminal nerve, so the pain must be coming from that nerve.
Facial pain has many possible sources. Trigeminal neuralgia is a specific diagnosis with characteristic features, and it is not the same as dental pain, temporomandibular joint pain, sinus-related pain, or post-herpetic neuralgia. If the underlying cause is different, an operation on the trigeminal nerve does not fit the problem, no matter how well the surgery is performed.
This is why an overseas patient considering MVD in China should treat the diagnosis as the first decision, not a formality. The hospital decides suitability, and that decision depends on what the records actually show. Your job before travel is to make sure the records give a neurosurgical team enough to work with.
What a vascular contact on MRI does and does not prove
Many patients arrive at the MVD question because an MRI report mentions a blood vessel near the trigeminal nerve. That finding is relevant, but it is not the same as a diagnosis. A radiologist describing anatomy is not the same as a clinician deciding whether that anatomy explains your pain.
Vascular contact near the trigeminal nerve can be seen in people whose pain has another explanation, and the severity of contact on an image does not by itself tell the surgeon whether decompression will help you. The treating neurosurgeon has to match the imaging to your history: the character of the pain, where it starts, what triggers it, how long episodes last, and how it has responded to medication. That clinical picture is what turns an imaging finding into a working diagnosis.
So when you ask a Chinese hospital about MVD, the useful question is not "do you see a vessel on my MRI?" but "does my clinical history plus imaging fit trigeminal neuralgia, and is MVD a reasonable option for me?" Those are different questions, and only the second one leads to a surgical plan.
The records that let a neurosurgeon answer your question
A records-based review is only as good as the records. For a facial-pain question, the most useful file is not the largest one; it is the one that documents the diagnosis and the treatment history clearly.
Ask the receiving clinician which of your existing documents they want to see. In practice, a neurosurgical team assessing possible trigeminal neuralgia will typically want to understand the pain history, the neurological examination findings, what medications have been tried and how the pain responded, and the actual imaging rather than only the written report. If you have had dental, ENT, or TMJ assessments that ruled out other causes, those notes help too, because they show what has already been considered.
The imaging point deserves emphasis. A radiology report is a summary; the surgeon may want the original images to review the anatomy directly. Ask whether the hospital can accept your images in their original format and whether they need them uploaded before an appointment or brought in person. Confirm this with the specific hospital rather than assuming a format or a deadline.
You do not need to send a complete medical archive at first contact. A short summary of the pain problem, the working diagnosis, and your main question is enough to start. More detailed records follow once the relevant clinician has asked for them.
- A written summary of when the pain started, where it is, what triggers it, and how it has changed.
- Neurological examination notes, if you have them.
- A list of medications tried, doses, and whether they helped, with the prescribing clinician's notes where available.
- The original MRI images, not only the report, if the hospital requests them.
- Any assessments that considered or excluded other causes of facial pain.
Questions that change the next step
Not every question is equally useful. The ones below are designed so that the answer tells you whether to prepare for travel, gather more records, or reconsider the whole route.
Ask whether the team agrees that trigeminal neuralgia is the working diagnosis, and on what basis. Ask whether MVD is a reasonable option for your case, and what alternatives they would consider. Ask what additional information or testing they would need before they could give a surgical opinion. Ask who would make the final suitability decision and what that process looks like. Ask what the hospital's written plan and quote would include, and what remains undecided until after an in-person assessment.
The answers to these questions are not a formality. A team that says it needs more information is giving you a useful answer. A team that offers a surgical date before reviewing your history and imaging has not yet answered the diagnosis question, and that is the question you started with.
A planning example: two patients, two different next steps
Consider two people who both describe severe facial pain and both have an MRI mentioning a vessel near the trigeminal nerve. This is a planning illustration, not medical advice.
The first has a pain history that fits trigeminal neuralgia, has tried medication with a documented response, and has original imaging available. For this person, the next step is a neurosurgical records review focused on suitability for MVD, and the practical questions shift to appointment preparation, what the hospital needs before a decision, and how a treatment plan would be structured if MVD is offered.
The second has pain that is constant rather than episodic, began after a dental procedure, and has features that do not match trigeminal neuralgia. For this person, the next step is not an MVD consultation at all. It is clarifying the diagnosis, which may mean a neurology or pain assessment first. Pursuing MVD before the diagnosis is settled would be premature, even if the MRI report mentions a vessel.
The difference between these two paths is not the hospital and not the surgeon. It is the clinical picture and the records that document it. That is why the diagnosis question has to be answered before the travel question.
What China-based coordination can and cannot do for this decision
ChinaSpecialistCare provides information and non-clinical coordination. We can help you identify a relevant neurosurgical route, prepare a records summary, and arrange an appointment or a records-based opinion. We do not diagnose, and we cannot confirm acceptance in advance. The hospital and its clinicians decide suitability, and that decision follows their own review.
If you want a records-based opinion before travelling, a proxy consultation is one option, but it is optional and not a prerequisite for every appointment. A free initial case review can check whether your available records and main question are clear enough to route to the right specialist. That review is not a diagnosis and does not promise acceptance.
For the facial-pain diagnosis question specifically, the most useful thing you can do before contacting anyone is to write down your pain history in plain language and gather the records that document it. That summary is what a neurosurgical team needs in order to tell you whether MVD is even the right question for your case.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.