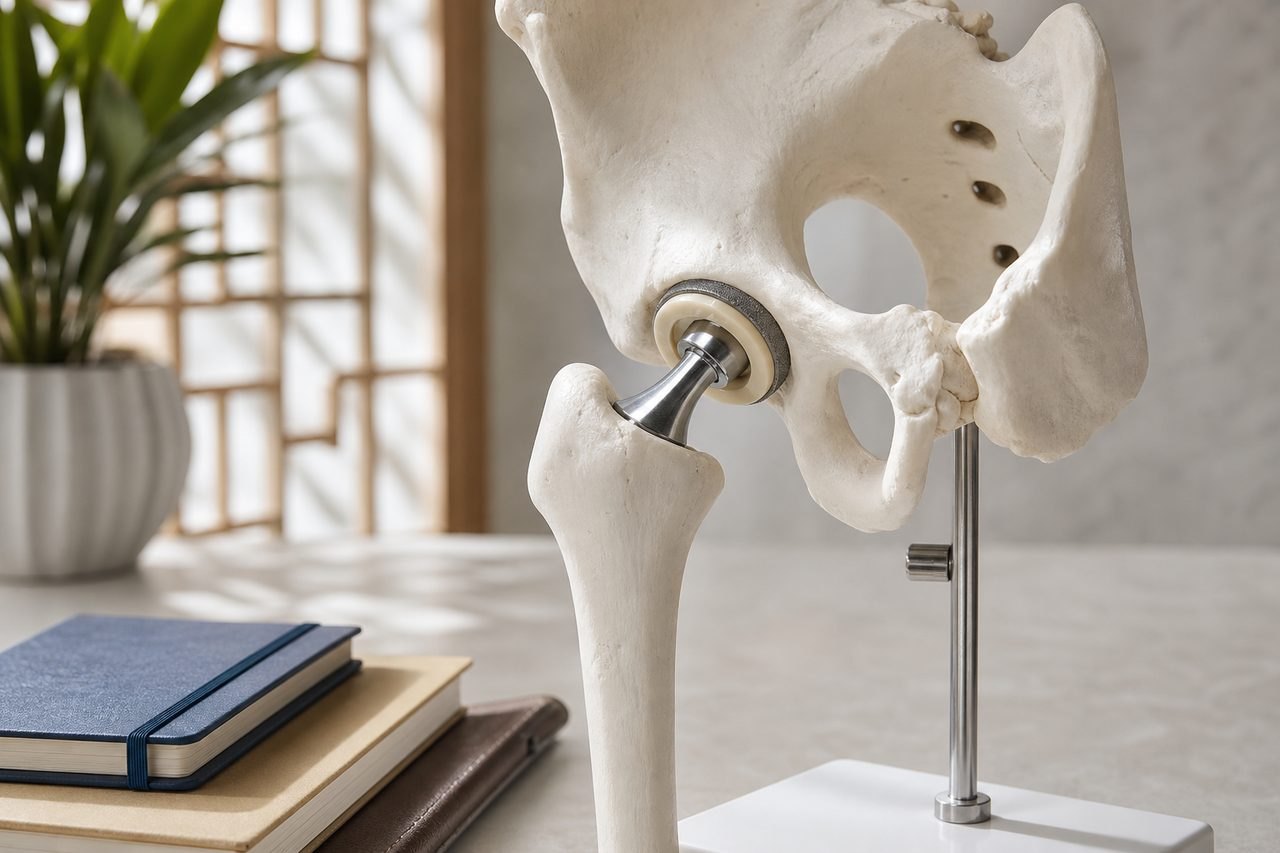
Why a verbal handover is not enough after partial hip replacement
Partial hip replacement replaces the femoral head, unlike total replacement of both joint surfaces. After surgery, the patient often leaves the hospital with instructions given in person, in a language they may not fully follow, and with no single document that a home clinician can act on. That gap matters because follow-up after hip surgery involves several separate decisions: wound review, imaging, mobility progress, and who to contact if something changes. If those decisions live only in a discharge conversation, the patient becomes the messenger for clinical information they are not qualified to interpret.
A written follow-up plan is not a substitute for the treating team's judgement. It is an administrative record that makes the clinical plan portable. It should state what is planned, who is responsible, and what has not yet been decided. That last point is often missing. A plan that lists appointments but not the unresolved questions leaves the next clinician guessing.
For an overseas patient, the plan also has to survive a change of country. A Chinese hospital's internal record system may not be readable by a clinician at home. The written plan should therefore be something the patient can carry, translate if needed, and hand over without needing to explain the context from memory.
What the written plan should actually contain
The plan should be specific enough that a clinician who has never met the patient can understand what happened and what comes next. Ask for it in writing before discharge, and ask for a copy in a language your home clinician can read, or a certified translation if the hospital can arrange one.
At minimum, the document should identify the procedure performed, the date, and the treating team. It should state the discharge diagnosis and any restrictions the treating team has set. It should list the follow-up actions already scheduled and the actions still to be arranged. It should name a contact person or department for clinical questions, and a separate route for administrative questions such as records requests.
The plan should also state what is not included. If the hospital has not arranged physiotherapy after discharge, say so. If imaging is planned but not yet booked, say so. If the patient is expected to arrange a local review, say so. A plan that implies more continuity than exists is worse than a plan that admits its limits.
- Procedure name and date, and the treating team's identity.
- Discharge diagnosis and any activity or weight-bearing restrictions the treating team has set.
- Follow-up actions already booked, with dates and locations if confirmed.
- Follow-up actions still to be arranged, and who is expected to arrange them.
- Clinical contact route and administrative contact route, kept separate.
- A list of records that will be released to the patient, and in what format.
Records that need to travel with the patient
The written plan is only useful if the underlying records travel with it. Ask the hospital what it will release and in what format. Common items include the discharge summary, operation note, implant details, and imaging reports. Whether images themselves are released on disc, by link, or not at all is a hospital-specific question, so ask rather than assume.
Implant details deserve particular attention. If a partial hip replacement has been performed, the home clinician may need to know the implant type and manufacturer for future decisions. Ask the hospital to include this in the written record, and ask whether the patient will receive a copy of the implant card or sticker.
If the hospital cannot release a document before discharge, ask when it will be ready and how it will be sent. Do not assume it will be emailed automatically. Confirm the method, the recipient, and what happens if the patient has already left China.
Who is responsible for what after discharge
A follow-up plan fails when responsibility is unclear. The Chinese treating team may consider its role finished at discharge. The home clinician may consider the patient's care to have been handed over. The patient may believe both are still involved. Writing down who is responsible for each task prevents that gap.
Ask the hospital to state, in the plan, which tasks it will continue to manage and which it will not. For example, if the hospital will review imaging remotely, that should be written down with the contact route. If it will not, the plan should say that follow-up imaging will be arranged locally. If the patient is expected to send records back to China for review, the plan should say who receives them and what response to expect.
The home clinician's role should also be recorded. If the patient has a local doctor or physiotherapist, ask whether the Chinese team is willing to communicate with them directly, and if so, through what channel. Do not assume this will happen. Ask for it in writing, and confirm whether the home clinician agrees to the arrangement.
Contact routes and what to do when something changes
The plan should give a clear contact route for clinical questions and a separate route for administrative ones. Clinical questions should go to a named department or clinician, not to a general enquiry address. Administrative questions about records, bills, or appointments can go elsewhere. Mixing the two delays both.
Ask what the expected response process is. Do not ask for a guaranteed response time, because that depends on the hospital. Instead, ask how the hospital handles messages, who reviews them, and what the patient should do if there is no reply. If the patient is no longer in China, ask whether the same route still works and whether language support is available.
The plan should also state what the patient should do if symptoms change after discharge. This is a clinical question, and the answer belongs to the treating team. Ask them to write down the specific circumstances in which the patient should seek urgent local care rather than wait for a reply from China. Do not rely on a general instruction to contact the hospital if worried.
Confirming the plan before you leave China
Before discharge, read the written plan and check that it answers the questions above. If something is missing, ask for it to be added. If the hospital cannot provide a particular item, ask them to state that in writing instead of leaving it blank. A plan that records its own gaps is more useful than one that implies completeness it does not have.
If you are planning care in China and want to understand what a written follow-up plan can cover for partial hip replacement, you can start with a free initial enquiry. Our team can review the available records and your main question, identify missing information, and suggest the relevant next step. This is not a diagnosis or a promise of acceptance, and it does not replace the treating hospital's own plan.
For patients who are still deciding whether to travel, the practical next step is to ask the hospital, before admission, what written follow-up documentation it provides and how it handles records after discharge. That answer should shape the decision as much as the surgical plan itself.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.