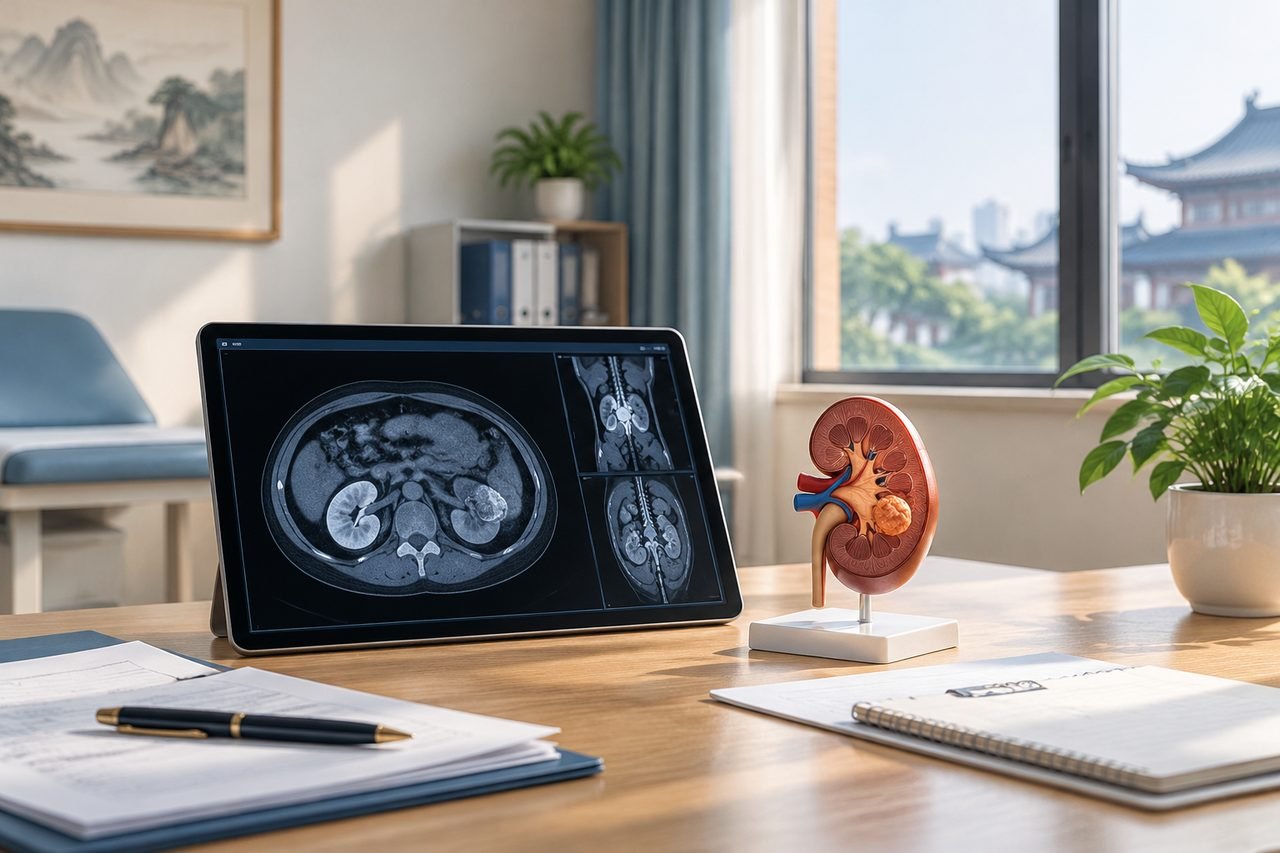
What partial nephrectomy is meant to achieve
Partial nephrectomy is a kidney operation that removes the affected part of the kidney. The purpose is usually twofold: to treat a lesion that needs removal and to leave as much healthy kidney tissue as safely possible. That second goal is why the operation is often discussed when a patient has a single kidney, reduced kidney function, or a lesion that can be removed without taking the whole organ.
The operation is not a single fixed procedure. The surgical approach depends on where the lesion sits, how deep it reaches, how close it is to the collecting system or major blood vessels, and what the remaining kidney function looks like. A lesion in an awkward position may be removable only with greater risk to the kidney, or not partially removable at all. That is a clinical judgement, not a preference the patient can select in advance.
It also matters what the lesion actually is. Imaging can show a mass and suggest its likely nature, but imaging alone does not confirm a cancer diagnosis. The final answer usually comes from pathology after tissue is removed. So the operation can address a lesion that the team judges needs surgery; it cannot, by itself, tell you before surgery exactly what that lesion is.
What the operation cannot promise
Partial nephrectomy cannot guarantee that all abnormal tissue is removed with clear margins. The surgeon works to remove the lesion with a margin of normal tissue where possible, but the pathology report after surgery is what confirms whether the removal was complete. If the margin is positive or the lesion turns out to be more aggressive than expected, further discussion, monitoring or additional treatment may be needed. That is a possibility to discuss with the treating team, not a prediction for any individual.
It cannot guarantee that kidney function will stay the same. Removing part of a kidney reduces the amount of working kidney tissue, and the remaining kidney may or may not compensate fully. How much function remains depends on the function before surgery, the amount of tissue removed, and other health factors. The team should explain what they expect for your situation and what monitoring will follow.
It cannot guarantee that partial removal is technically feasible. Some lesions are better treated by removing the whole kidney, by ablation, or by another approach. The decision depends on the lesion and the kidney assessment, and it is made by the treating clinicians, not by the patient choosing a procedure name.
It also cannot replace the need for follow-up. Even after a successful partial nephrectomy, imaging and kidney-function checks are typically part of ongoing care. The schedule is set by the treating team based on the pathology and your overall health.
Why the lesion and kidney assessment decide the plan
The two questions that shape the recommendation are: what is the lesion, and what will happen to kidney function if part of the kidney is removed? Imaging such as CT or MRI is used to look at the size, position and depth of the lesion, and its relationship to the kidney's blood supply and urine-collecting system. Blood tests estimate how well the kidneys are working. Together, these help the team judge whether partial removal is reasonable, what approach to use, and what risks to discuss.
This is why sending only a diagnosis line is rarely enough for a useful opinion. The team needs the actual images, the radiology report, recent kidney-function blood tests, and any biopsy or pathology results if a sample has already been taken. If you have had previous kidney surgery or have other conditions affecting kidney function, that history matters too.
Different clinicians may weigh the same information differently. One may judge that partial removal is feasible with acceptable risk; another may consider the risk to kidney function too high and recommend a different approach. That is normal in kidney surgery, and it is one reason a records-based review is a discussion of options rather than a final decision.
Questions to ask the treating team before you commit
The most useful preparation is a short list of questions that force specific answers rather than general reassurance. Ask what the imaging shows about the lesion's position and depth, and what that means for the chance of preserving the kidney. Ask what your current kidney function is and how much function the team expects to remain after surgery. Ask what the proposed approach is and why it was chosen over the alternatives.
Ask what the plan is if the pathology after surgery shows something different from what was expected. Ask what follow-up imaging and blood tests will be needed, and who will arrange them. Ask what symptoms or changes should prompt you to seek care sooner. These are the questions that turn a procedure name into a plan you can actually evaluate.
It also helps to ask what the team needs from you before they can give a firm recommendation. If a test is missing, ask whether it can be done locally and sent, or whether it needs to be repeated. Do not assume that a partial nephrectomy is available to you simply because it is a recognised operation; the treating hospital decides suitability after reviewing your records.
- What does the imaging show about the lesion's size, position and depth?
- What is my current kidney function, and what is expected after surgery?
- Which surgical approach is proposed, and why?
- What are the alternatives if partial removal is not suitable?
- What follow-up will be needed, and who arranges it?
How a records-based review fits into the decision
For an overseas patient, the practical first step is usually a records-based review rather than immediate travel. A review can clarify whether the records are complete enough for a useful opinion, what the main clinical questions are, and which type of specialist or hospital is relevant. It does not confirm that surgery will go ahead, and it does not replace the treating hospital's own assessment.
A records-based opinion can be arranged while you remain at home. The scope should be agreed in advance: which records are reviewed, which questions are answered, and what the output will be. A written opinion that addresses the lesion, kidney function and the feasibility of partial removal is more useful than a general statement that surgery is possible.
If the review suggests that partial nephrectomy may be suitable, the next stage is a direct assessment by the treating hospital. That assessment, not the remote review, is what establishes whether the operation is appropriate for you. If the review suggests that partial removal is unlikely to be feasible or safe, that is also useful information, because it may point you toward a different discussion.
For patients who want to understand the procedure itself before deciding, the ChinaSpecialistCare partial nephrectomy reference page explains the operation in more detail. It is a reference, not a promise of suitability or access.
Practical preparation and the limits of an overseas enquiry
If you decide to enquire about care in China, start with a brief summary: your main question, the diagnosis or suspected diagnosis, and the key records you already have. Do not send passport numbers, card details or a complete medical archive at first contact. After the initial reply, you can be told which specific records are needed and how to share them securely.
Keep your local care in place while you explore options. If your symptoms worsen, or if you develop new pain, fever, blood in the urine or reduced urine output, seek local medical assessment rather than waiting for an overseas reply. An overseas enquiry is not a substitute for timely local care.
Be cautious about any statement that guarantees kidney preservation, cancer control or a particular outcome. No responsible clinical team can promise those things before reviewing your imaging, kidney function and pathology. What a team can do is explain its assessment, the proposed approach, the alternatives and the uncertainties in your case.
The initial enquiry through ChinaSpecialistCare is free and non-clinical. It checks whether your records are sufficient to identify the relevant next step and which questions still need answers. A proxy consultation or multidisciplinary review is optional and is not required before a hospital appointment. The treating hospital decides suitability, and any estimate of hospital fees should come from that hospital in writing, with its included and excluded scope stated.
A useful next step is to gather your most recent kidney imaging, the radiology report, kidney-function blood tests and any pathology results, then send a short summary with your main question. That gives the team enough to tell you what is missing and whether a records-based review or a direct hospital assessment is the appropriate next move.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.