
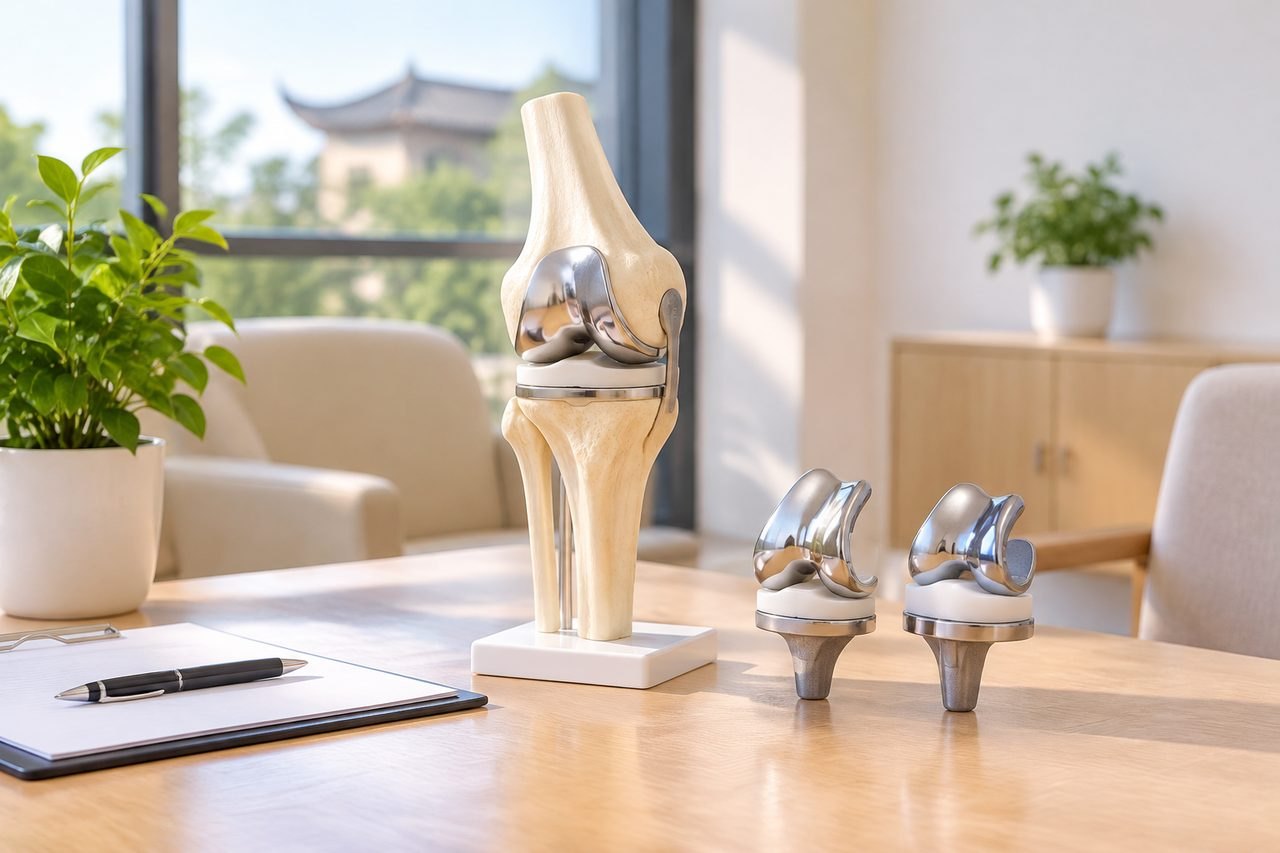
What actually differs between the two techniques
In a manual total knee replacement, the surgeon uses preoperative imaging, templates and instruments to guide the bone cuts and balance the soft tissues around the new joint. In a robotic-assisted knee replacement, a robotic system supports the surgeon, typically using a patient-specific plan derived from imaging and, depending on the system, intraoperative data. The surgeon still makes the decisions and performs the operation; the robot is a tool, not an independent operator.
That distinction matters because marketing can make robotic surgery sound like a different treatment. It is not a different implant or a different disease. The operation remains a knee replacement. What changes is the planning and execution method, and with it the equipment, the surgical team's training and experience with that system, and the resources involved.
The evidence comparing robotic-assisted and manual knee replacement continues to develop. Some studies report differences in alignment accuracy or early measures, while others find similar results at longer follow-up. Rather than treating any single study as decisive, ask the surgeon what the evidence shows for patients like you and how it shapes their recommendation. A responsible clinician can discuss evidence-based risks and expected outcomes without guaranteeing your individual result.
The questions to settle before choosing a technique
The most useful preparation is a short list of questions that force clarity. Start with your own knee: what is the diagnosis, how severe is the arthritis, and is the deformity or alignment problem one that makes planning more demanding? Partial knee replacement, revision surgery and cases with significant deformity are different conversations from a straightforward total knee replacement.
Then move to the technique. Ask whether robotic assistance is expected to change anything meaningful for your knee specifically, or whether it is offered as an option with similar expected results. Ask about the surgeon's own experience with both manual and robotic-assisted knee replacement, and whether the same team would perform either. Experience with a system is a fair question; a named surgeon or a guaranteed outcome is not something an enquiry can promise.
Finally, ask what happens if the robotic plan cannot be used on the day, for example because of equipment, technical or clinical reasons. A clear answer tells you whether the team has a fallback plan and how it would be discussed with you beforehand. Consent conversations should happen before sedation, when you can ask questions and understand the alternatives.
Records that help a surgeon answer properly
A surgeon cannot judge suitability from a description alone. Useful records typically include recent knee X-rays, and where available a standing long-leg alignment view, plus any MRI or CT that has already been done. Your clinic letters, operation notes from previous knee surgery, and a list of medicines and allergies help too. If you have had a previous replacement, the prior implant details and any revision history are relevant.
These are items to ask the receiving clinician about, not a universal checklist that every patient must complete before contact. If something is missing, the team can tell you what would actually change their assessment. Do not arrange new scans on your own initiative before a clinician has said they are needed; unnecessary imaging adds cost and delay without improving the decision.
For an international patient, also prepare a clear summary of your main question. Are you trying to decide between techniques, seeking a second opinion on a recommendation you already have, or exploring whether surgery in China is realistic for you? The answer shapes what records matter most and which specialist should review them.
What the choice means for planning care in China
If you are considering knee replacement in China, the hospital and surgical team decide whether robotic-assisted surgery is appropriate and available for your case. Availability of a robotic system at a particular hospital, the team's familiarity with it and the scheduling involved are questions to confirm directly with the provider. An enquiry or records review does not establish hospital acceptance or guarantee that a specific technique will be used.
Cost is a separate question, and it is worth separating hospital charges from any coordination service you use. Published reference figures for knee replacement are indicative ranges for the named procedure, not fixed or guaranteed quotes, and they do not tell you whether robotic assistance changes the price at a given hospital. The final price requires an individual assessment and written confirmation of the treatment plan and fee scope, including what the quote covers. Ask each hospital how it prices the proposed operation and what the written plan includes.
It is reasonable to ask each hospital how it describes the proposed operation, what the written plan includes, and which charges are paid to the hospital versus any coordination service. Avoid assuming that a quoted figure covers everything or that a robotic option is priced the same as a manual one; ask for the actual written scope rather than relying on general impressions.
Risks, recovery and what no technique removes
Knee replacement carries risks regardless of technique: infection, blood clots, stiffness, implant-related problems and the need for rehabilitation. Robotic assistance does not remove these risks, and it introduces its own technical and equipment considerations. Ask the surgeon to explain the risks that apply to you, what would be done to reduce them, and what warning signs should prompt urgent contact after surgery.
Recovery depends on your general health, the condition of the knee, the rehabilitation plan and your home circumstances. No article can give you a reliable personal timeline, and no technique guarantees a faster or better recovery for an individual. Ask the treating team and physiotherapist what milestones to expect and how follow-up would be arranged, including whether remote review is possible once you return home.
The physiotherapist or receiving clinician makes their own assessment of your rehabilitation needs; it is not the case that only the original surgical team can assess you. Plan practical arrangements, such as where you will stay during early recovery and who can help you, as questions to settle with the provider rather than fixed rules.
A practical next step
Write down your diagnosis, your main question and the records you already hold. Then ask the hospital team the technique questions above and request a written plan and fee scope for your case. If you would like help identifying a suitable orthopedic specialist or organising an appointment, ChinaSpecialistCare's free initial case review checks the available information and suggests a relevant next step; it is not a diagnosis or a promise of acceptance. A proxy consultation is optional and not a prerequisite for an appointment or operation.
Sources & scope of this guide
References and official service information relevant to this guide.
- Related treatment reference
- American Academy of Orthopaedic Surgeons: Knee Replacement
- National Institute for Health and Care Excellence: Joint replacement (primary): hip, knee and shoulder
- National Health Service: Knee replacement
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.