Why a Shoulder Arthritis Recommendation Can Change
A changed recommendation is not automatically a contradiction. It can reflect new information, a different interpretation of the same information, or a different goal. Your task is to find out which of those applies before you commit to travel or treatment.
Shoulder arthritis care is not one decision. The joint surfaces, the rotator cuff tendons, previous surgery and the bone shape all influence what a surgeon considers reasonable. A recommendation may shift because the new clinician sees a different pattern of joint damage, because an older scan is compared with newer imaging, or because the first plan was made before a tendon problem was fully assessed.
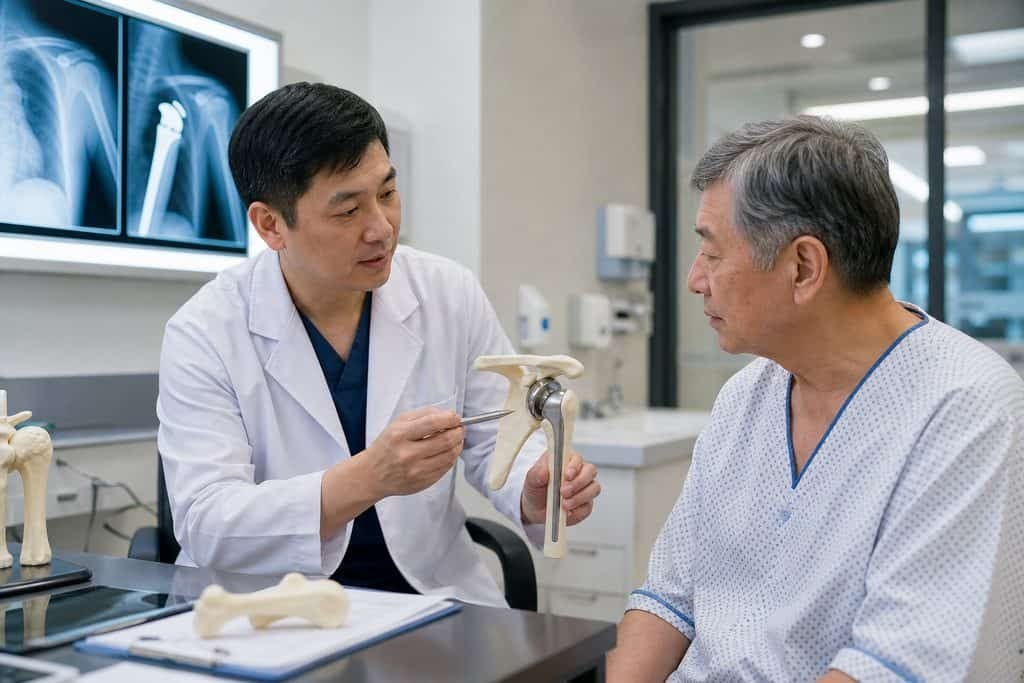
The design question matters here. Shoulder replacement uses artificial components, and conventional and reverse designs differ. The choice depends on the shoulder condition, not on preference alone. If one clinician proposed a conventional design and another proposed a reverse design, that difference usually points to a disagreement about the state of the rotator cuff or the surrounding anatomy. Ask both teams to explain what they saw that led to their design choice.
A recommendation can also change because the goal changed. Pain relief, restoring overhead reach, returning to a specific sport, and avoiding a second operation are different targets. A plan that suits one goal may not suit another. Write down your own main goal in one sentence before you ask anyone to compare plans.
Compare the Diagnosis, Not Just the Procedure Name
Two recommendations can sound identical and still rest on different diagnoses. Ask each team to write the diagnosis in plain terms: which joint is affected, how advanced the arthritis is believed to be, and whether the rotator cuff is considered intact, torn, or already repaired.
This is where shoulder and tendon findings do most of the work. Glenohumeral arthritis, cuff tear arthropathy, and arthritis after a previous fracture are not interchangeable labels, and they do not lead to the same operation. If the two recommendations use different diagnostic labels, that is the first thing to clarify.
Ask what evidence supports each label. Relevant items may include plain X-rays, a CT scan, an MRI, ultrasound of the cuff, and the operative note from any earlier shoulder surgery. You do not need to decide which test is correct. You need to know which records each clinician actually reviewed.
A useful question is: "Which specific finding in my records changed your recommendation compared with the earlier plan?" A clear answer names a finding. A vague answer may mean the earlier records were not available or were not reviewed in detail.
Previous Shoulder Surgery and Implant History
If you have already had shoulder surgery, that history can change the recommendation more than the arthritis itself. Previous rotator cuff repair, instability surgery, fracture fixation, or an existing shoulder replacement all alter the anatomy and the options.
Gather the original operative report, the implant sticker or card if a device was used, and the most recent imaging. If an implant is already in place, the manufacturer and model matter to the team assessing whether revision is possible and what components could be used.
Do not assume that a prior operation rules out further treatment, and do not assume it makes further treatment straightforward. Both are clinical judgements. Ask the receiving surgeon directly: "Does my previous surgery change which design or approach you would consider, and why?"
If you cannot obtain the old operative note, say so early. The new team can then tell you what it can and cannot conclude without it, rather than discovering the gap after you arrive.
What a Records-Based Opinion Can and Cannot Settle
A records-based review can compare diagnoses, identify missing documents, and explain why two plans differ. It can also give you a clearer set of questions for the surgeon you eventually see.
It cannot confirm final suitability for an operation, and it cannot replace an in-person examination. Shoulder function, strength, stiffness and pain behaviour are assessed partly by examining you. A remote opinion is a step in planning, not a final clearance.
This distinction matters when a recommendation has changed. You may be tempted to treat the second opinion as the correct one. A more reliable approach is to ask what each opinion is based on, what remains uncertain, and what would need to be checked in person.
If the case is complex, involving both joint and tendon problems or a previous failed operation, a review that includes more than one relevant specialty may be useful. The scope and fee for that kind of review are agreed before it starts.
Questions to Ask Before You Plan Care in China
Bring a short, written list. The goal is not to challenge the clinician but to make the comparison explicit.
Ask which diagnosis the new plan is based on, and which records support it. Ask whether the rotator cuff status changes the recommended implant design, and whether a conventional or reverse design is being considered and why. Ask what happens if the in-person examination differs from the records-based view.
Ask about alternatives, including non-surgical options, and about the risks the surgeon considers most relevant in your case. You are entitled to ask about evidence-based risk estimates and the uncertainty around them. No estimate guarantees your individual result.
Ask what the written plan and quote include, what remains undecided, and what would change the plan. Ask how follow-up and rehabilitation would be arranged, and who would supervise it. Rehabilitation after shoulder surgery is specific to the shoulder; it is not a hip or knee protocol.
Finally, ask what you should do if your symptoms worsen before any planned trip. Worsening pain, new weakness, or a sudden loss of movement needs local assessment rather than waiting for an overseas appointment.
Practical Preparation and a Sensible Next Step
Prepare a compact record set rather than a complete archive. Useful items typically include the most recent clinic letters, imaging reports and the actual images if available, the operative note from any previous shoulder surgery, and a one-page summary of your symptoms, treatments tried and main goal.
You can start with a short summary through the enquiry form, email or WhatsApp. An initial case review is free and checks the available diagnosis, records and your main question, identifies missing information, and suggests a relevant next step. It is not a diagnosis and does not promise acceptance.
If you want a records-based opinion before travelling, a proxy consultation is available and optional. It is not a prerequisite for every appointment or operation. Specialist matching and appointment coordination can also be requested, with hospital consultation fees paid separately to the hospital.
The treating hospital and its clinicians decide suitability, the implant design, and the treatment plan. ChinaSpecialistCare provides information and non-clinical coordination; it does not prescribe, decide eligibility, or guarantee availability or outcomes.
A practical next step is to write your one-sentence goal and your list of changed-recommendation questions, then send a brief summary for the free initial review. From there, you can decide whether a records-based opinion or a specialist appointment request is worth pursuing.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.