Why an MDT Is a Question to Confirm, Not a Guaranteed Format
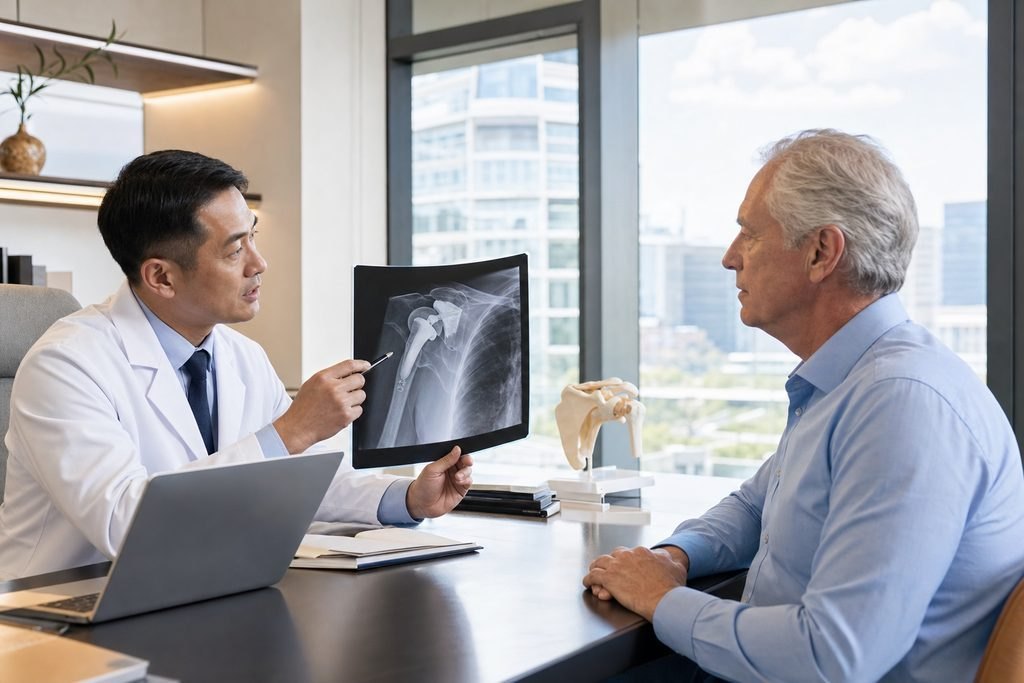
Shoulder arthritis that has not responded to non-surgical care can raise several overlapping questions: how much the joint surface is worn, whether the rotator cuff tendons are intact, what a previous shoulder operation changed, and which implant design would suit the remaining bone and soft tissue. These questions can cross orthopedic surgery, musculoskeletal radiology and rehabilitation. A hospital may handle them through one senior surgeon, a combined clinic, or a formal multidisciplinary team meeting. The format is a local arrangement, not a universal service.
For an overseas patient, the practical risk is planning travel around an assumed meeting that the hospital does not routinely run for this condition. Ask directly whether the hospital holds a combined discussion for shoulder arthritis, who would attend, whether you can receive a written summary, and whether the discussion happens before or after you arrive. If no combined format exists, ask how the treating surgeon would obtain input from radiology or physiotherapy when needed. A clear answer here prevents a wasted trip.
A records-based review arranged before travel is different from a hospital MDT. A remote review can clarify what your imaging shows and what questions remain, but it does not replace the treating hospital's own assessment or acceptance decision. The hospital decides suitability.
The Shoulder Findings an MDT Must Interpret Together
Shoulder arthritis is not only about the ball-and-socket cartilage. The rotator cuff tendons, the deltoid, and the condition of the glenoid bone all influence what can be done. A discussion that only reviews the joint space and ignores tendon integrity may reach a different conclusion than one that reads the imaging together. Ask whether the discussion will include a radiologist or a surgeon experienced in shoulder soft tissue, and whether the tendon findings are considered stable enough to support a particular design.
The distinction matters because conventional and reverse shoulder replacement designs differ, and the choice depends on the shoulder condition. A conventional design generally relies on an intact or repairable rotator cuff. A reverse design changes the mechanics and is used when the cuff is not functioning well. If the MDT cannot state which tendons are torn, degenerated or repairable, the implant decision rests on incomplete information. Ask what specific imaging or examination finding would change the recommendation, and whether that finding is already documented.
You do not need to interpret the scans yourself. Your role is to ensure the records you send are complete enough for the discussion to answer this question. If a report is missing or unclear, the hospital may request repeat imaging in China, which affects timing and cost. Ask in advance which existing images are acceptable and whether they need to be uploaded in a particular format.
How Previous Shoulder Surgery Changes the Discussion
A previous shoulder operation, whether for instability, rotator cuff repair, fracture or infection, changes the bone stock, scar tissue and tendon status. An MDT reviewing your case should state what the earlier surgery did, what remains, and whether revision or primary replacement is more appropriate. This is not a question you can answer from an old discharge summary alone; the operative note and any subsequent imaging are central.
Ask the hospital whether the discussion will include a surgeon who handles revision shoulder cases, and whether the team needs the original operative report rather than a summary. If the previous surgery was in another country, the report may be in a different language. Ask whether a translated summary is acceptable or whether the original document is required. This is an administrative question with clinical consequences: an incomplete history can lead to a plan that does not account for altered anatomy.
The MDT should also address what is not known. If the prior procedure details are unavailable, the discussion may need to proceed with stated assumptions and a plan to verify during surgery. Ask how those assumptions would be documented and who would decide if the intraoperative findings change the plan. Consent discussions should cover this possibility before any sedation or surgery.
Implant Design: What the Discussion Should Decide and What It Cannot
The choice between a conventional and a reverse shoulder replacement is a clinical decision that depends on the shoulder condition. An MDT discussion can weigh the tendon findings, bone quality, prior surgery and your functional goals. It cannot guarantee a specific outcome, and it should not promise a particular implant brand unless that brand is confirmed available at the hospital. Ask which designs the hospital uses, whether the proposed design is available for your anatomy, and what would happen if the planned implant does not fit.
The discussion should also clarify who makes the final intraoperative decision. Even a well-planned MDT may need to adjust based on what the surgeon finds. Ask whether the plan includes alternatives and how those alternatives would be explained to you. If you have a preference based on information from your home country, state it clearly and ask how it fits the team's assessment. The treating clinicians decide suitability.
Do not expect the MDT to provide a personal implant recommendation before examining you. A records-based discussion can narrow the options and identify what needs confirmation, but final selection belongs to the operating surgeon with your consent. Ask what specific information from your examination or imaging would confirm the proposed design.
Questions to Put in Writing Before You Travel
A written list helps you compare answers and avoids relying on memory during a consultation. Send the questions through the hospital's international office or your coordination contact, and ask for written responses where possible. The following checklist covers the decision points that an MDT discussion should address for shoulder arthritis. Use it as a template, not as a script that every hospital must follow.
If the hospital cannot answer a question before you arrive, ask whether it will be answered during the first appointment and whether that appointment can be scheduled before you commit to travel. For complex cases, a remote records review may help clarify whether a trip is worthwhile, but it does not guarantee acceptance or a specific treatment plan. The hospital decides suitability after its own assessment.
- Does the hospital hold a combined discussion for shoulder arthritis, and who attends?
- Will the discussion review rotator cuff tendon findings alongside the joint surface?
- How will a previous shoulder operation be accounted for, and which records are needed?
- Which replacement designs are available, and what would change the recommendation?
- Who makes the final intraoperative decision, and how are alternatives documented?
- Can you receive a written summary of the discussion before consent or travel?
- What costs are included in the hospital's written estimate, and what remains undecided?
What to Prepare and How to Take the Next Step
Prepare a short summary of your shoulder history, including when symptoms began, what treatments you have tried, and what a previous operation did if applicable. Include recent imaging reports and the operative note if you have one. Do not send passport numbers, card details or a complete medical archive at first contact. A brief summary is enough for an initial enquiry.
Ask the hospital or your coordination contact to confirm the MDT format, the records needed, and the expected sequence of appointments. If you are considering care in China, an initial enquiry is free and can help identify missing information before you commit to travel. A proxy consultation is optional and not a prerequisite for every appointment. The hospital decides whether to accept your case and what treatment to recommend.
Keep local care in place while you plan. If your shoulder pain worsens, or you develop new weakness, numbness or fever, seek assessment where you are rather than waiting for an overseas appointment. An overseas enquiry should not delay necessary local care.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.