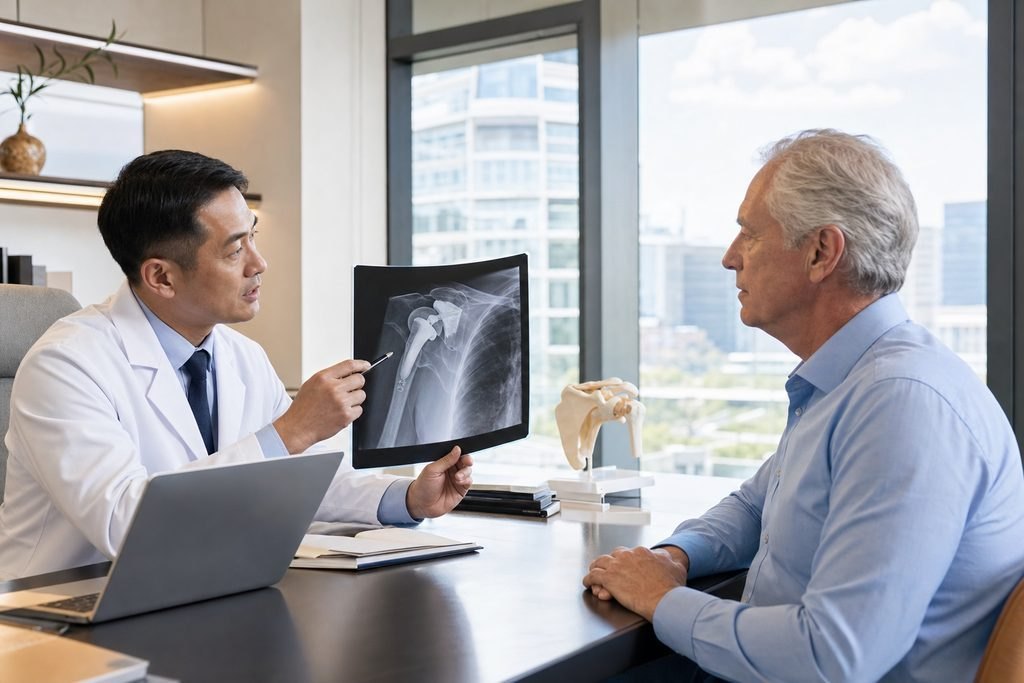
Why the Report Wording Matters More Than the Diagnosis Label
A report that says only 'shoulder arthritis' leaves the most important planning questions unanswered. Glenohumeral arthritis affects the ball-and-socket joint itself. Rotator cuff arthropathy involves both the joint surfaces and a tendon deficiency that changes which implant design may be appropriate. Those are different problems, even when both cause pain and stiffness.
For an overseas patient considering care in China, the report is the starting point for a records-based opinion. It is not a treatment plan. The treating hospital decides suitability after reviewing the actual images and examining the patient. What the report can do is tell a specialist whether the case is straightforward, whether key information is missing, and whether a remote opinion is likely to add value before travel.
Ask for the report in a form that names the specific structures assessed. 'Degenerative changes' is less useful than a statement about joint space, humeral head position, glenoid wear and the condition of the rotator cuff tendons. If the report uses a grading system, ask what that grade refers to and whether it applies to the joint, the tendon or both.
Shoulder and Tendon Findings: What Each Part Changes
The tendon findings often decide the direction of the whole plan. A shoulder with an intact, functional rotator cuff and preserved bone stock raises different questions from one with a large, chronic cuff tear and altered joint mechanics. The report should state which tendons were assessed, what was found, and whether the finding is acute, chronic or degenerative.
The joint findings matter separately. Glenoid bone loss, humeral head erosion and any deformity affect how a specialist thinks about reconstruction. If the report mentions cysts, sclerosis or loose bodies, ask whether those findings change the surgical options or only describe the arthritis.
Imaging modality also matters. An X-ray can show joint space narrowing and bone changes. Ultrasound or MRI can show tendon and soft tissue detail. A report based only on X-ray may not answer tendon questions at all. Before sending records to China, check which modality produced each finding, because a specialist reading a plain film report cannot confirm tendon status from it.
One practical step: ask the reporting clinician to separate joint findings from tendon findings in writing. This makes it easier for a receiving specialist to see what is established and what still needs imaging review.
Previous Shoulder Surgery Changes the Questions
If you have had shoulder surgery before, the report should say what was done and when. A prior rotator cuff repair, a stabilization procedure, a fracture fixation or an earlier replacement all change the anatomy a surgeon will encounter. The report should also note whether hardware is present and whether it is intact.
Previous surgery can affect both the choice of implant design and the complexity of the procedure. It may also mean that old operative notes are more useful than the current imaging report alone. Ask for the original operation record, the implant details if any, and the most recent follow-up note.
This is not a reason to assume a particular approach is or is not possible. It is a reason to make sure the records sent for review include the surgical history, so the receiving specialist can ask focused questions rather than work from an incomplete picture.
Conventional and Reverse Designs: What the Report Should Support
Shoulder replacement uses artificial components. Conventional and reverse designs differ, and the choice depends on the shoulder condition. The report does not need to recommend a design, but it should contain the findings a specialist would use to discuss one.
For a conventional design, the relevant questions centre on the joint surfaces and whether the rotator cuff can still function. For a reverse design, the tendon and bone situation is central. If the report does not address the rotator cuff, the receiving specialist may need to review the images directly or request additional imaging before giving a meaningful opinion.
The report should also state what it does not cover. A note that the rotator cuff was not assessed, or that the images were limited, is more useful than silence. It tells the receiving team where the gaps are, rather than leaving them to assume the tendon findings are complete.
If the report mentions glenoid wear, humeral head position or bone loss, ask whether those findings are described in enough detail to support a discussion about component fixation. This is a question for the reporting clinician, not a conclusion you need to draw yourself.
Ask the treating team in China what they need to see before discussing design options. Do not expect a remote report review to finalize the implant choice. That decision belongs to the operating surgeon after examining you and reviewing the full imaging set.
A second practical point: if you have imaging from more than one time point, include the dates. A report from two years ago and a current one may show different degrees of joint change, and the receiving specialist will want to know which findings are current.
Finally, keep the design question open in your own mind. The report can support a conversation about conventional versus reverse options, but it cannot settle which design is right for you. That conversation belongs with the surgeon who will examine the shoulder directly.
What a Records-Based Opinion Can and Cannot Establish
A records-based opinion can identify whether the diagnosis is clear, whether the tendon findings are adequate, and what additional information the hospital would want. It can help you decide whether travelling to China for assessment is worth pursuing. It cannot confirm hospital acceptance, final surgical suitability or a specific implant plan.
If you are considering this route, start with a brief summary rather than a complete archive. The initial enquiry is free and non-clinical. It checks the available diagnosis, records and your main question, identifies missing information and suggests the relevant next step. A proxy consultation with a hospital specialist is optional and not a prerequisite for every appointment.
Be clear about what you want from the review. 'Is this case suitable for shoulder replacement in China?' is a different question from 'What is missing from my records?' The first requires clinical assessment. The second can often be answered from the documents you already have.
Preparing the Report for a China Enquiry
Before sending anything, check that the report is legible, dated and attributed to a named imaging centre. Include the imaging itself if it is available in digital form, not only the written report. A specialist who can see the images is less dependent on the report's wording.
Prepare a short list of your own questions. For example: which tendons were assessed and what was found; whether previous surgery is documented; whether the report supports a discussion about conventional versus reverse design; and what the treating hospital would still need to confirm. These questions help the receiving team respond usefully rather than generally.
Keep the first contact brief. A summary of the diagnosis, the main symptom and the specific question is enough to begin. More detailed records can follow once the relevant next step is clear.
For shoulder arthritis care in China, the practical next step is to request a free initial case review with a short summary of your diagnosis and your main question. The team will identify what is missing and suggest how to proceed. The hospital decides suitability after its own assessment.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.