Why a TAVR estimate is a range, not a price
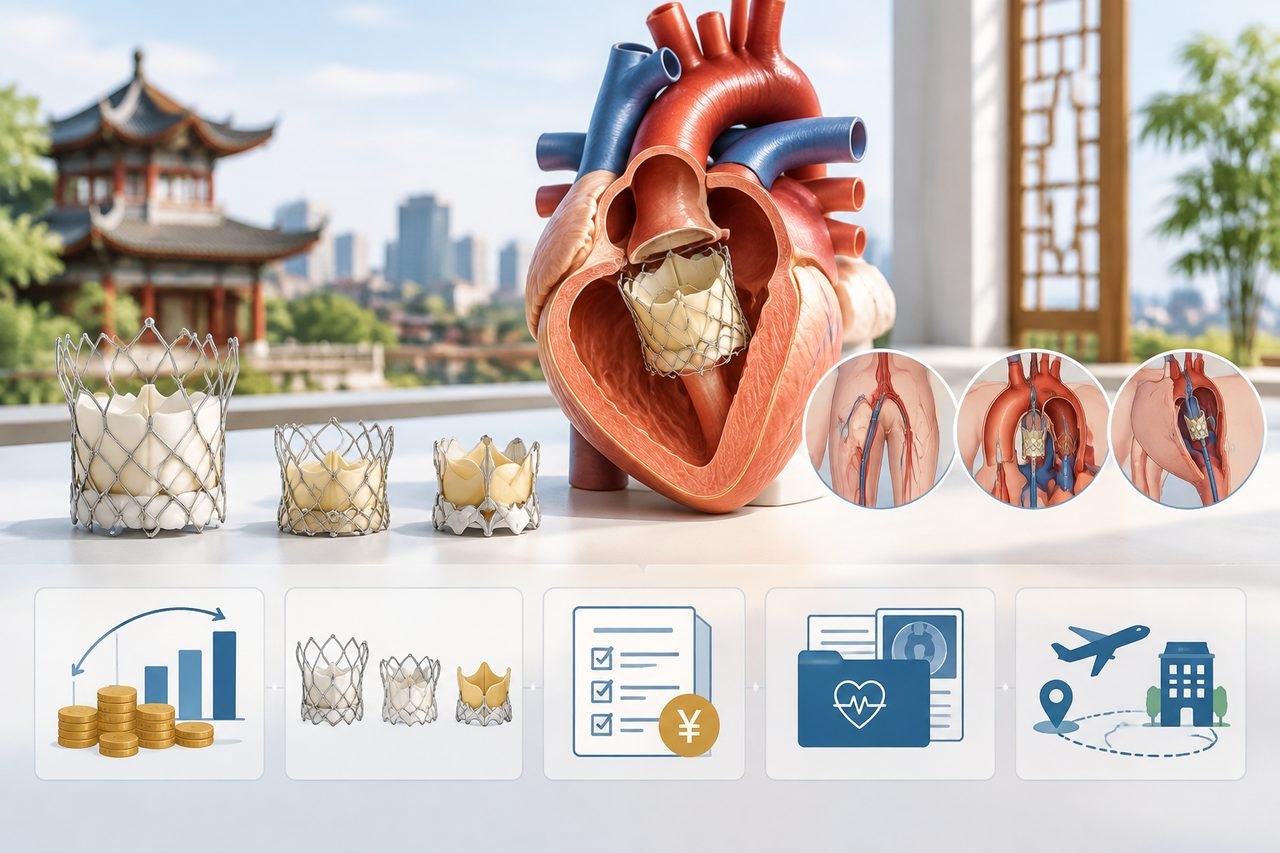
TAVI, also called TAVR, replaces the aortic valve using a catheter-based procedure. That single sentence hides a lot of variation. A transcatheter aortic valve is a manufactured device with a model, a size and a country of origin. The catheter route may be through the femoral artery, through the chest wall, or through another vessel. The procedure may be done under general anaesthesia or with lighter sedation. Each of those choices carries its own device and hospital charges.
This is why a hospital cannot give you a meaningful figure from a diagnosis alone. Two patients with the same echocardiogram report can receive different valves, different access routes and different ward stays. The estimate follows the plan, and the plan follows the heart team's review of your records.
When you request a TAVR estimate from a hospital in China, you are really asking for a case-specific quotation. The useful question is not 'what does TAVR cost in China?' but 'what does this plan cost for this patient at this hospital?' Those are different questions, and only the second one has a number attached.
The valve question: which device, and who chooses it
The valve is often the largest single line in a TAVR estimate, but the choice is clinical, not commercial. The heart team weighs your aortic annulus size, the anatomy of your access vessels, your kidney function, your previous cardiac surgery if any, and the risk of coronary obstruction. Different valves have different profiles, delivery systems and sizing ranges. A valve that suits one patient may be unsuitable for another.
This means you should ask which valve the team plans to use and why. You do not need to select the device yourself. You do need to know whether the quoted figure assumes a specific model, because a change of valve after the estimate is issued will change the price.
Ask also whether the quoted valve is available at that hospital at the time of your proposed admission. Device stock is a hospital logistics matter, and it is reasonable to confirm it in writing rather than assume it. If the team says the valve choice will be finalised after a CT and a heart team meeting, then the estimate you receive before that meeting is provisional, and you should treat it as such.
A related question: does the estimate cover one valve, or does it allow for a second device if the first cannot be implanted? You are not asking the team to predict complications. You are asking how the quote is structured, which is a fair administrative question.
What the hospital estimate should itemise
A written TAVR estimate from a Chinese hospital is most useful when it separates categories rather than giving one lump sum. Ask for the device, the procedure and catheter laboratory charges, anaesthesia, intensive care or monitored bed days, the ward room, medicines and consumables, imaging, and any laboratory work. Ask whether the figure is a package or an itemised projection.
Then ask what happens if the actual stay is longer than the estimate assumes. A quote built on a set number of ward days is not the same as a quote that covers the whole admission. You do not need to accept either model, but you should know which one you are looking at before you compare hospitals.
Ask whether the estimate includes the pre-procedure workup: the CT, the echocardiogram, the coronary assessment, the blood tests and the consultations that the heart team needs before it can decide on TAVR at all. Some hospitals quote the procedure alone; others quote a pathway. The two figures are not comparable until you know which is which.
Finally, ask who issues the estimate and whether it is signed or stamped. A verbal range from a coordinator is not the same as a hospital document you can plan around.
Records the heart team needs before it can price your case
A TAVR estimate cannot be firm without the records that drive the plan. The most important is usually a recent echocardiogram with the aortic valve measurements and the degree of stenosis or regurgitation. A gated CT of the aorta and the access vessels is normally central to planning, because it determines whether a transfemoral approach is feasible and what valve sizes are possible. Coronary angiography or a CT coronary assessment is often needed to check for significant coronary disease that might need treatment first.
Beyond imaging, the team will want to know your kidney function, your lung function if there is respiratory disease, your previous cardiac operations, your current medicines, and your functional status. A recent chest X-ray, an ECG and blood results are commonly part of the file. If you have had a previous valve procedure, the operative note matters.
You do not need to send everything at once. A short summary with the key reports is enough for a first review, and the hospital can tell you what is missing. Ask which documents are essential for a firm estimate and which can wait until you arrive. That answer tells you how close you are to a real number.
If some records are unavailable, say so. The team can tell you whether it can proceed with what you have or whether a repeat study in China would be needed. Do not assume that missing records block care, and do not assume they are irrelevant.
Hospital fees, coordination fees and travel costs are separate
The hospital's TAVR estimate covers hospital charges: the device, the procedure, the beds, the medicines and the investigations the hospital performs. It does not cover your flights, your accommodation, your meals, your visa costs or your travel insurance. Those are your own travel expenses, and they sit outside the medical quote.
If you use a coordination service, its fees are separate again. ChinaSpecialistCare charges for non-clinical coordination such as specialist matching, appointment registration, interpretation and practical support, and those fees are agreed with you directly. The hospital's charges are paid to the hospital. Do not expect one organisation to absorb the other's costs, and do not expect a coordination fee to appear on a hospital invoice.
This separation matters when you compare options. A lower hospital quote with higher travel and coordination costs may not be cheaper overall. Write the three columns down separately: hospital, coordination, travel. Then compare.
Ask the hospital whether its estimate is in renminbi or another currency, and what exchange rate assumption, if any, it uses. Ask when payment is due and in what form. These are administrative questions the hospital's international office can answer.
Questions that change the next step
The answers you receive should tell you whether you are ready to plan travel or whether you are still in the assessment stage. If the heart team says it needs a CT before it can choose a valve, your next step is to arrange that imaging, not to book flights. If the team says the records are sufficient and the estimate is firm, your next step is to review the quote, the proposed dates and the payment terms.
Ask the team directly: is this estimate conditional on further tests, and if so, which ones? Is the quoted valve the one you expect to implant? Does the figure cover the whole admission or a set number of days? What would change the estimate upward? Those four answers will tell you more than any single number.
Ask also about the ward. A standard ward and an international or private ward carry different room charges, and the estimate should state which one it assumes. You are entitled to know the difference before you decide.
If you are still gathering information, an initial enquiry with a brief summary of your diagnosis and your main question is free and does not commit you to anything. The hospital, not the coordination service, decides whether TAVR is suitable for you. You can start by sharing a short summary and asking what the heart team needs next.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.