Why an article cannot recommend TAVR or TAVI for you
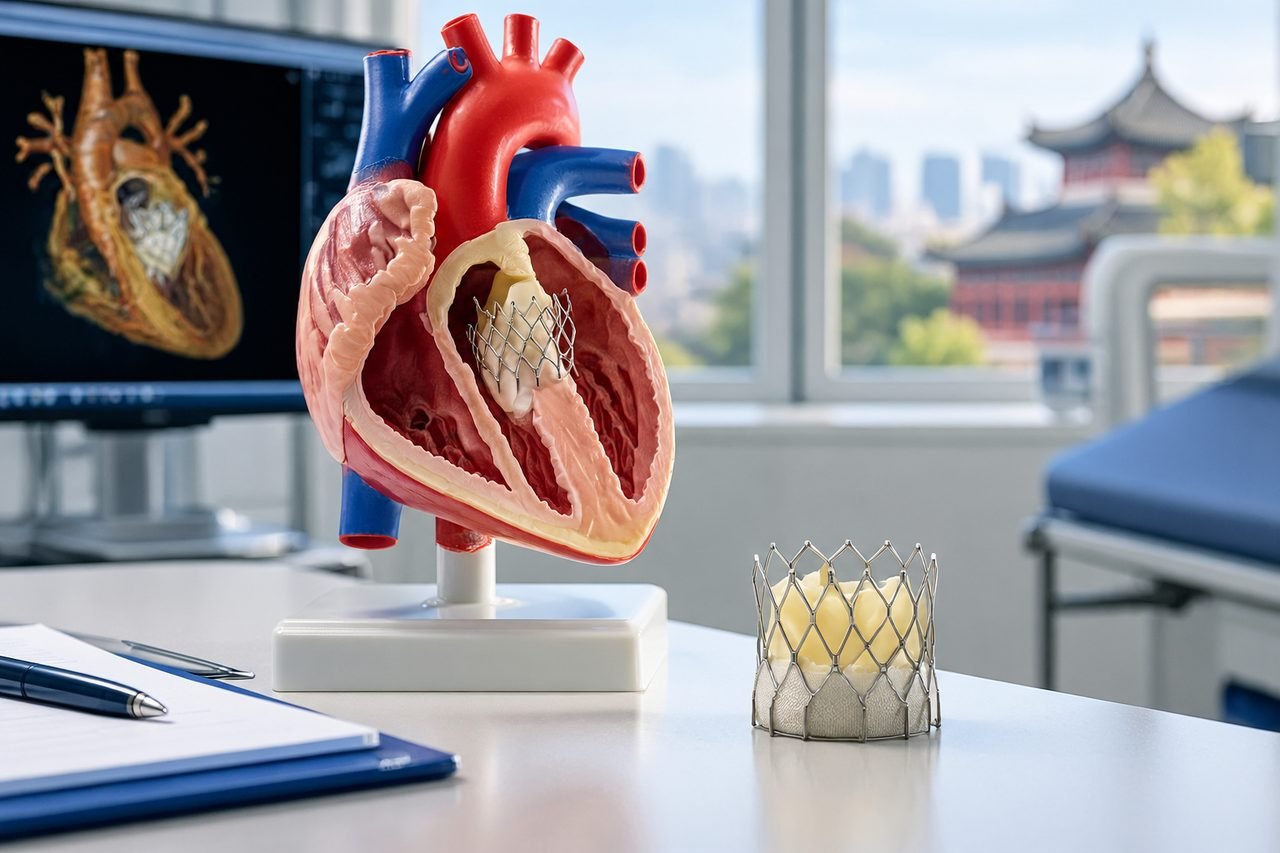
TAVI, also called TAVR, replaces the aortic valve using a catheter-based procedure. That single sentence describes the treatment category, not your treatment. Whether a catheter-based approach is reasonable for a particular person depends on valve anatomy, the rest of the heart, other medical conditions, prior heart surgery, access vessels and the goals of care. Those are clinical judgements made from images and records, not from a diagnosis label alone.
This matters because international patients often arrive at a decision in the wrong order. They first ask which hospital in China does TAVR or TAVI, then ask about cost, then ask whether they are suitable. A heart team works in the opposite direction. It reviews the evidence, decides whether a catheter-based valve procedure is appropriate at all, and only then discusses device and logistics. If you reverse that order, you may spend money on travel and coordination for a procedure the receiving clinicians would not recommend.
A guide can help you ask better questions. It cannot examine your echocardiogram, measure your aortic valve area, assess your coronary anatomy or judge your frailty. Any article that tells you that you are a candidate, or that a particular device is best for you, is going beyond what written information can support.
So the useful question is not "should I have TAVR or TAVI?" It is "what do I need to ask, and what do I need to send, so that a heart team can tell me whether this is appropriate for me and what the alternatives are?"
What the heart team actually reviews before proposing a valve procedure
When clinicians assess a person for a catheter-based aortic valve procedure, they are not looking at one number. They are combining several streams of information. The valve itself matters: how narrow it is, how many leaflets it has, how much calcium is present, and whether the anatomy favours a catheter-delivered device. The surrounding structures matter too, including the aortic root and the access routes through which a catheter would be passed.
The rest of the heart matters. Coronary artery disease, previous bypass surgery, the function of the left ventricle and the presence of other valve disease can all change the balance between a catheter-based procedure and surgical aortic valve replacement. So can the person's general condition: kidney function, lung disease, frailty, cognitive state and the ability to recover from either approach.
This is why the assessment is usually described as a heart team decision rather than a single specialist's opinion. Cardiology, cardiac surgery, imaging and anaesthesia each contribute a different view. The point of the team is not to make the process slower; it is to reduce the chance that a technically feasible procedure is performed on someone for whom a different plan would be better.
For an overseas patient, the practical consequence is that the quality of the review depends heavily on the quality of the records you send. A brief summary is enough for an initial enquiry, but a clinical opinion needs the actual images and reports, not a description of them.
The records that make a risk-and-alternatives discussion possible
You do not need to assemble a complete archive before making first contact. A short summary of the diagnosis, the main question and the current treatment is enough to start. If the case moves forward, however, the heart team will need specific documents. The most important is usually the echocardiogram, ideally with the images themselves rather than only the written report, because valve measurements and anatomy are read from the images.
Other useful items include the most recent cardiac catheterisation or coronary CT report, any previous cardiac surgical records, current medication list with doses, recent blood tests including kidney function, and a clear note of symptoms and how they have changed. If a CT scan of the heart and vessels has already been performed for procedural planning, that is directly relevant. If it has not, the receiving team will decide whether it is needed; you should not arrange it yourself in advance.
Language is a practical issue. Reports in English are easier for many international departments, but the underlying images are what matter most. If your records are in another language, ask whether the hospital requires a certified translation or whether an interpreter can support the review. This is a question for the specific hospital, not a general rule.
A useful habit is to keep one folder, physical or digital, with the images and the reports together, and a one-page summary on top. When you ask about risks and alternatives, you can then ask a focused question: "Based on these images, what did the team conclude about my valve anatomy, and what alternatives did it consider?"
How to ask about risks without asking for a personal recommendation
Patients often phrase risk questions in a way that invites a reassuring answer rather than an informative one. "Is this safe?" is difficult to answer usefully. "What are the main risks the team is concerned about in my case, and how do they compare with the alternatives?" is a better question, because it asks the clinicians to reason about your situation rather than recite general statistics.
It is reasonable to ask about the risks that matter for this procedure category. These can include stroke, bleeding, damage to blood vessels at the access site, problems with the new valve, kidney injury, infection and the possibility that a planned catheter procedure cannot be completed and another approach is needed. You can ask how the team plans to reduce each of these risks in your case, and what would happen if one occurred.
You can also ask about uncertainty. Clinicians can discuss evidence-based estimates of risk and benefit for people with features similar to yours, while being clear that no estimate guarantees an individual result. Asking "what is the range of outcomes you would expect, and what would change your recommendation?" is a legitimate and useful question. It is different from asking for a promise.
Finally, ask about the alternative. For aortic valve disease, the main alternative to a catheter-based procedure is usually surgical aortic valve replacement, but there may also be situations where the team recommends medical management, further testing, or a period of observation. Ask why the proposed plan was chosen over each alternative, and what would have to be different about your case for the recommendation to change.
Device choice, admission and follow-up: questions to confirm with the provider
The device used in a catheter-based aortic valve procedure is a clinical decision, not a patient preference in the way a hotel room is. Different devices have different profiles, delivery systems and evidence bases, and the heart team selects based on anatomy and clinical factors. You can still ask which device is proposed and why, whether more than one option is available at that hospital, and what the team would do if the first choice proved unsuitable during the procedure.
Admission and follow-up arrangements are also provider-specific. Rather than assuming a standard pathway, ask the hospital directly: how many days of admission are typically planned for a case like mine, what monitoring is required afterwards, when would the first follow-up review happen, and what imaging or tests would be repeated. These are questions to confirm with the named provider, because answers vary with the individual case and the hospital's own practice.
If you are considering care in China, it is reasonable to ask how the hospital handles international patients: whether an international department is involved, what language support is available, how records are transferred, and who is responsible for coordinating the different specialists. You can also ask whether the hospital requires any documents or approvals before it will confirm acceptance. The hospital decides suitability and acceptance; a coordination service cannot promise either.
One administrative example may help. If you want a records-based opinion before travelling, you can ask a coordination service to arrange a review with a relevant specialist while you remain at home. That review is an opinion based on the records provided; it does not replace the hospital's own assessment and does not confirm that a procedure will go ahead.
What to do next, and what not to expect
Start by writing down your main question in one or two sentences, and gather the key reports and images you already have. Then make an initial enquiry. An initial enquiry is free and does not require buying a proxy consultation; it is a way to check what information is missing and what the relevant next step might be. You can share a brief summary first and send records after first contact.
When you speak with a hospital or a coordination team, keep the conversation focused on the decision you are actually making. Ask how the heart team reviews valve imaging, which device is proposed and why, what alternatives were considered, and what admission and later heart reviews would involve for your case. Ask what the written estimate includes and excludes, and ask the named provider how its own quote and scheduling work rather than relying on general assumptions.
Do not treat any reply as a guarantee of treatment, a promise of a particular outcome, or a substitute for the hospital's own clinical assessment. If your symptoms worsen, seek local medical care rather than waiting for an overseas enquiry to progress. A remote review can inform a decision; it cannot replace urgent assessment.
The realistic goal is not to obtain a personal recommendation from an article. It is to arrive at a conversation with the right records and the right questions, so that the clinicians who can examine your case are able to give you a clear view of the risks, the alternatives and the uncertainties.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.