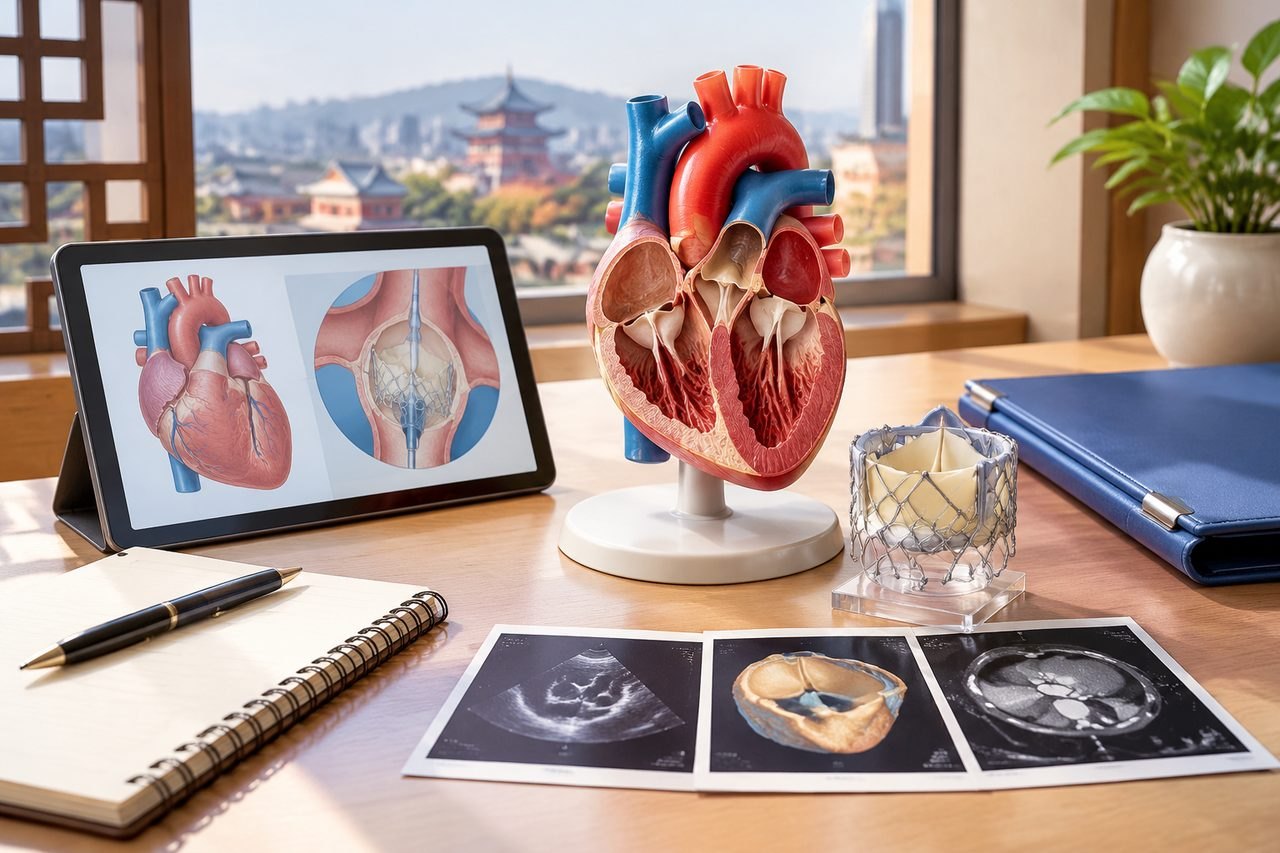
What TAVR and TAVI actually treat
TAVI, also called TAVR, replaces the aortic valve using a catheter-based procedure. The aortic valve sits between the left ventricle and the aorta, and when it narrows it can restrict blood flow out of the heart. The procedure is designed to address that narrowed valve by implanting a replacement valve, usually without opening the chest.
That focus matters when you are deciding whether to travel. TAVR and TAVI are not a general treatment for all heart disease. They do not replace a blocked coronary artery, repair a leaky mitral valve, or correct an irregular heart rhythm. If your main problem is something other than a narrowed aortic valve, the heart team may recommend a different treatment entirely.
The procedure also does not remove the underlying condition that caused the valve to narrow. It replaces the valve, but the rest of your heart and blood vessels still need ongoing medical care. That is one reason follow-up matters after the procedure, not just the implant itself.
Why valve anatomy and imaging decide the plan
The heart team reviews valve imaging before deciding whether TAVR or TAVI is suitable. The size and shape of your aortic valve, the condition of the surrounding structures, and the access routes for the catheter all affect whether the procedure is technically possible and which device might be considered.
This is not a decision that can be made from a diagnosis alone. Two patients with the same label, such as aortic stenosis, can have very different valve anatomy. One may be a candidate for a catheter-based procedure; another may need open-heart surgery, or may need further tests before any recommendation is made.
If you are seeking care in China, ask how the heart team reviews your valve imaging. Specifically, ask which imaging studies they need, whether they want the original images or a report, and whether they will repeat any imaging in China. The answers will tell you what to prepare and how the team is approaching your case.
What the treatment cannot address
The clearest way to understand the limits is to separate the valve from everything else in the chest. TAVR and TAVI act on the aortic valve. They do not open a blocked coronary artery, repair a leaking mitral or tricuspid valve, close a hole between the heart's chambers, or correct an irregular heart rhythm. If your breathlessness, chest tightness or fatigue is driven mainly by one of those other problems, replacing the aortic valve will not fix it, and the heart team may steer you toward a different procedure or a different combination of treatments.
Symptoms are the part patients can misread. Shortness of breath, chest pain, ankle swelling and fatigue can each come from several causes at once, including coronary artery disease, heart failure, lung disease, anaemia or a rhythm problem. A narrowed aortic valve can contribute to all of them, which is why improvement after the procedure is possible but not automatic. If a second condition is also active, it may still limit you after the valve is replaced. That is a reason to ask the team which of your symptoms they expect the valve procedure to change, and which they expect to persist or need separate care.
The procedure also does not remove the underlying process that narrowed the valve in the first place, and it does not guarantee a specific result for any one person. The heart team can discuss evidence-based risks and expected benefits for your case, including the uncertainty around them. Ask your clinician what the realistic range of outcomes looks like for someone with your anatomy and your other conditions, and what would count as a good result for you. A single promised figure is not the same as an honest range.
Medication, lifestyle management and ongoing heart reviews continue after the implant. The valve is replaced; the rest of your cardiovascular care is not. If you assume the procedure covers everything and stop other treatment on your own, you may put yourself at risk. Any change to medication belongs with the clinician who prescribed it, not with a travel plan or a coordination service.
One more limit is easy to overlook: a catheter-based procedure is not automatically the right choice for every narrowed valve. Open-heart surgery may offer a more durable option for some patients, particularly those who are younger or who have anatomy that suits a surgical approach. The heart team weighs both routes rather than defaulting to the less invasive one. If you are told that TAVR or TAVI is the only option without that comparison being explained, it is reasonable to ask why surgery was set aside for your case.
How the heart team decides suitability
The heart team decides whether TAVR or TAVI is appropriate for you. That team typically includes cardiologists, cardiac surgeons, imaging specialists, and sometimes anaesthetists. They review your records, your valve imaging, your other medical conditions, and your goals of care.
No article can tell you whether you are a candidate. Suitability depends on factors that only the treating team can assess, including the anatomy of your valve, your other heart conditions, your kidney function, your lung function, and your overall health. The team also considers whether open-heart surgery would be a safer or more durable option for you.
If you contact a hospital in China, ask how their heart team reviews cases. Ask whether they use a formal multidisciplinary meeting, who attends, and how they communicate the decision to you. You can also ask whether they offer TAVR and TAVI as part of their valve programme, and what devices they currently use. These are reasonable questions, and the answers help you understand the route ahead.
What to prepare before seeking a review
A useful review starts with a clear summary of your main question and the records that support it. You do not need to send a complete medical archive at first contact. A brief summary of your diagnosis, your current symptoms, and your main concern is enough to begin.
For a valve review, the most useful records often include recent echocardiogram reports and images, cardiac catheterisation reports if you have had one, a list of your current medications, and any recent blood tests or chest imaging. If you have had a previous heart operation, include the operative note or a summary.
Ask the receiving team what format they prefer for imaging. Some teams want DICOM files on a disc or secure transfer; others may accept a report first and request images later. Confirm this before you send anything, so your records are usable when they arrive.
Also ask how the team will communicate with you. Will they provide a written opinion, a video call, or an in-person appointment? Who will explain the findings, and in what language? These practical details affect how quickly you can make a decision.
Questions to ask about admission and later heart reviews
If the heart team considers TAVR or TAVI suitable, you will need to understand what the admission involves and what follow-up looks like. Ask how the team plans the procedure, what tests they require before admission, and how they will monitor you afterwards.
Ask specifically about later heart reviews. How often will you need follow-up? Who will coordinate those reviews, and can they be done locally or do they need to be at the same hospital? What symptoms should prompt you to seek urgent care? These questions help you plan beyond the procedure itself.
You should also ask what the written estimate or treatment plan includes. Ask the named provider how its quote is structured, what is included, what is excluded, and what remains undecided until after the heart team review. Do not assume that one hospital's billing approach applies to another.
Finally, ask about the boundaries of a remote review. A records-based opinion can help the team understand your case, but it does not establish final eligibility or hospital acceptance. The heart team in China will make its own assessment when it has the records and imaging it needs.
A brief next step: if you want to explore care in China, start with a free initial enquiry. Share a short summary of your diagnosis and your main question. The team can then tell you what records are missing and what the relevant next step is. You do not need to buy a proxy consultation to begin.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.